

Elbow & Forearm Conditions, Limitation of Motion & Bone Impairment
An elbow or forearm that will not fully bend, straighten or rotate, weak and painful when you lift, carry or turn your palm.
The elbow is a deceptively complex joint, and the VA rates it on four separate motions plus the condition of the two forearm bones. Under 38 CFR §4.71a, Diagnostic Codes 5205–5213, your rating is built from measured flexion and extension, from ankylosis if the joint has fused, and from nonunion, malunion, or flail-joint impairment of the ulna and radius. Forearm rotation, supination and pronation, the motion you use to turn a key, a doorknob, or a screwdriver, is rated on its own scale under Code 5213 and can be compensable entirely on its own. The rating turns on two things veterans routinely lose points on. The first is measured motion with pain considered: under §4.40 and §4.45, and under *DeLuca* and *Mitchell*, the examiner must record where pain begins and estimate the additional loss during a flare-up, an exam that only reports the end of the arc is inadequate. The second is the dominant-hand rule under §4.69: the identical limitation pays more on your dominant arm, so the examiner recording your handedness correctly is worth real money. Above all, do not let an elbow or forearm condition be folded into your shoulder claim. It has its own diagnostic codes, and it deserves its own rating.
The Diagnostic Codes
Conditions Rated In Elbow & Forearm Conditions
These are the codes the VA will actually stamp on a decision in this group. The code you are granted under decides which formula is used, and that decides your percentage. Elbow & Forearm (DC 5205–5213) is highlighted below.

Before Anything Gets Rated
What The VA Is Actually Looking For, And What Service Connection Really Means
Before the VA ever opens the rating schedule, it asks one question: is this disability the government’s responsibility? That is what “service connection” means. It is not a diagnosis, it is not sympathy, and it is not a reward for having served. It is a legal finding that a current, diagnosed disability is linked to something that happened to you in uniform. Percentages come later. If service connection is not established, there is nothing to rate and the claim is denied, no matter how bad the elbow & forearm (dc 5205–5213) is.

For Elbow & Forearm (DC 5205–5213) Specifically
To win service connection for an elbow or forearm condition under DC 5205–5213, the VA needs three things locked down in the record: a current diagnosis naming the specific pathology (post-traumatic arthritis, malunion of the radial head, cubital tunnel syndrome, ankylosis, not just 'elbow pain'), an in-service event or injury that caused or aggravated it (a fall, a direct blow, a fracture, repetitive heavy lifting, or a documented MOS with repetitive upper-extremity loading), and a nexus opinion linking the two. Most elbow and forearm claims are won direct service connection on a documented in-service fracture, dislocation, or overuse injury, the service treatment records are the foundation, and if they are missing, a buddy statement or lay statement describing the incident is the fallback. The rating itself under §4.71a keys on goniometer-measured degrees of flexion, extension, supination, and pronation at the C&P exam, with the rater then matching those numbers to the specific DC that produces the highest rating, M21-1, Part III, Subpart iv, Chapter 4, Sections A–B (Musculoskeletal Conditions) requires the examiner to address painful motion, functional loss, and flare-up impact, and an exam that skips any of those elements is the single most common reason a veteran gets rated lower than the law allows.
The three elements the VA must find. All three. Every time.
These come out of Caluza v. Brown and Shedden v. Principi, and they are the checklist a rating officer works through on your file. Miss one and the claim fails on that element alone.
A current, diagnosed disability
A doctor has to have written a diagnosis in a medical record, For example, an imaging report reading "ununited fracture of the radial head with marked cubitus valgus deformity" (DC 5209) or "nonunion of the ulna with loss of bone substance greater than 2.5 cm" (DC 5211) is the kind of objective finding that anchors a higher evaluation, bring it to the exam.. Symptoms by themselves are not a disability the VA can rate. Saunders v. Wilkie held that pain causing functional impairment can be a disability, but you still need a clinician to document it as diagnosed and impairing. The diagnosis must exist now, during the claim period, not only years ago.
An in-service event, injury, illness or aggravation
Something in service had to have happened, an injury, an exposure, a documented sick call, or steady wear over a career. It does not have to be one dramatic moment and it does not have to be spelled out in your service treatment records: buddy statements, unit records, performance evaluations and your own competent lay testimony can establish it.
A medical nexus linking the two
A qualified medical opinion that says the current diagnosis is at least as likely as not related to the in-service event. That phrase matters: at least as likely as not means 50 percent or better. Under 38 C.F.R. §3.102, when the evidence is evenly balanced, the benefit of the doubt goes to you and the claim must be granted.
The five ways service connection is established
Most veterans only know the first one. The other routes are lower-effort paths to the same grant, and the secondary route is the one most often left on the table.
Direct, 38 C.F.R. §3.303(a)
The injury or disease began in service and never went away. The classic route: three elements, one nexus opinion.
Chronicity and continuity, §3.303(b)
A chronic condition shown in service, plus continuity of the same symptoms from separation to now, can establish the link without a formal nexus opinion. Your own testimony about symptoms you can observe is competent evidence.
Presumptive, §3.307 and §3.309
Certain chronic diseases are presumed service connected if they manifest to a compensable degree within a set window after separation. You do not have to prove causation at all.
Secondary, §3.310(a) and (b)
A disability proximately due to, or aggravated by, an already service-connected condition is itself service connected. This is how For example, a veteran service-connected for an elbow disability who develops numbness and tingling into the ring and little fingers can claim ulnar neuropathy at the cubital tunnel as secondary under §3.310, earning a separate rating under §4.124a. get on the rating sheet.
Aggravation of a pre-service condition, §3.306
If you entered service with a condition and service made it permanently worse, the increase is compensable. The VA must rebut the presumption of soundness by clear and unmistakable evidence, a bar it frequently fails to meet.
VA medical care, 38 U.S.C. §1151
An additional disability caused by VA treatment, surgery, or a failure to diagnose is compensated as if it were service connected.
The bottom line, there is no way around this
No diagnosis, no rating. It has to be chronic. It has to cause impairment.
Without a diagnosis, the VA will not rate your claim.
The VA cannot assign a diagnostic code to 'elbow pain' or 'forearm weakness', the record must contain a named structural or functional diagnosis such as post-traumatic arthritis, malunion, nonunion, ankylosis, or limitation of motion with an identified cause. Veterans lose this element when their only documentation is sick-call entries saying the elbow hurts, with no imaging, no orthopedic note, and no diagnosis attached to a pathology. If your treating physician has not written a diagnosis that maps to DC 5205–5213, the rater has nothing to hang a rating on and will deny for lack of a current disability.
The condition must be chronic.
A one-time elbow complaint that resolved with no follow-up will not carry a rating, the VA needs a documented history of ongoing symptoms or structural findings showing the condition persisted from service into the present. For fracture-based claims, imaging showing malunion, nonunion, or post-traumatic arthritic changes is the clearest proof of chronicity because the bone tells the story even decades later. Veterans who were treated in service, separated, and then waited years to seek care face a gap the VA will exploit, private treatment records, VA treatment records, or a credible lay statement explaining why care was delayed all close that gap under §3.303.
It must cause actual impairment.
Under DC 5205–5213 and §4.1, impairment is measured in degrees of lost motion against the normal arc, flexion 0–145°, extension 0°, supination 0–80°, pronation 0–80°, and if your C&P exam shows full or near-full motion with no painful arc documented, the rater will assign zero percent even if you are in real pain. The zero-percent trap hits veterans whose examiner records only the end-range measurement without noting where pain begins in the arc, which §4.40, §4.45, and the *DeLuca* doctrine require to be captured and credited as functional loss. A rating of zero percent means service connection is technically granted but no compensation flows, and that outcome is often the product of an inadequate exam, not an accurate picture of your elbow.
What this means for you before you file: Before you file, pull your service treatment records for any elbow or forearm injury, get current imaging (X-ray at minimum, MRI if available), and make sure a treating physician has written a diagnosis, not just a symptom, that names the structural condition. If your C&P exam does not include goniometric measurements, a painful-motion finding, and a flare-up assessment, request a new exam or submit a private DBQ that covers all three. Under Colvin v. Derwinski, the VA cannot override a treating urologist with its own unqualified medical opinion, insist that any contradicting assessment come from a physician of equal specialization.
The Percentages
Rating Schedule, Elbow & Forearm, DC 5205–5213
Where a percentage is shown as two numbers (for example 30% / 40%), the first is the non-dominant (minor) arm and the second is the dominant (major) arm, per §4.69. Under the Note to Codes 5205–5213, multiple impaired finger movements caused by tendon tie-up, muscle or nerve injury are rated separately and combined, not to exceed the rating for loss of use of the hand. Painful motion and flare-ups under §4.40 and §4.45 must be considered in every evaluation. The governing questionnaire is VA Form 21-0960M-2 (Elbow and Forearm Conditions).
50% / 60%
DC 5205, Unfavorable ankylosis of the elbow, at an angle of less than 50 degrees or with complete loss of supination or pronation (50% minor, 60% major). DC 5209, Flail joint of the elbow (50% minor, 60% major).
40% / 50%
DC 5205, Intermediate ankylosis, at an angle of more than 90 degrees or between 70 and 50 degrees (40% minor, 50% major). DC 5206, Flexion limited to 45 degrees (40% minor, 50% major). DC 5207, Extension limited to 110 degrees (40% minor, 50% major). DC 5210, Nonunion of both the radius and ulna with flail false joint (40% minor, 50% major).
30% / 40%
DC 5205, Favorable ankylosis, at an angle between 90 and 70 degrees (30% minor, 40% major). DC 5206, Flexion limited to 55 degrees (30% minor, 40% major). DC 5207, Extension limited to 100 degrees (30% minor, 40% major). DC 5211/5212, Nonunion of the ulna or radius with false movement and loss of bone substance (1 in. / 2.5 cm or more) and marked deformity (30% minor, 40% major). DC 5213, Loss of forearm rotation fixed in supination or hyperpronation (30% minor, 40% major).
20% / 30%
DC 5206, Flexion limited to 70 degrees (20% minor, 30% major). DC 5207, Extension limited to 90 degrees (20% minor, 30% major). DC 5211/5212, Nonunion of the ulna or radius with false movement, without loss of bone substance or deformity (20% minor, 30% major). DC 5213, Loss of forearm rotation with motion lost beyond the middle of the arc, or bone fusion with the hand fixed in full pronation (20% minor, 30% major).
20%
DC 5206, Flexion limited to 90 degrees (20% either arm). DC 5207, Extension limited to 75 degrees (20% either arm). DC 5208, Flexion limited to 100 degrees AND extension limited to 45 degrees (20% either arm). DC 5209, Joint fracture with marked cubitus varus/valgus deformity, or ununited fracture of the head of the radius (20% either arm). DC 5211/5212, Nonunion in the lower/upper half of the ulna or radius (20% either arm). DC 5213, Limitation of pronation with motion lost beyond the last quarter of the arc, or bone fusion near the middle of the arc (20% either arm).
10%
DC 5206, Flexion limited to 100 degrees. DC 5207, Extension limited to 45 or 60 degrees. DC 5211, Malunion of the ulna with bad alignment. DC 5212, Malunion of the radius with bad alignment. DC 5213, Limitation of supination to 30 degrees or less. Painful motion under §4.59 supports a minimum 10% where compensable motion is present.
0%
DC 5206, Flexion limited to 110 degrees (noncompensable), but still service-connected and important to establish for future increases and secondary claims.
Service Connection
Advice from the Advocate
This is where I stop explaining the rules and tell you how I would build your Elbow & Forearm (DC 5205–5213) claim if you were sitting across my desk. Read the causation notes below twice. The VA will not connect the dots for you, even though 38 CFR 3.159 says it has a duty to assist. Your job is to put the in-service event, the current diagnosis and the medical link on paper, then make the examiner deal with all three.
The advocate's notes on causation, Elbow & Forearm (DC 5205–5213)
The separate arguments that decide this code: where the VA will attack, the regulation that answers it, and the evidence that closes the gap.
1Direct service connection, §3.303(a)
An elbow condition diagnosed in service, or documented as chronic within the first year after separation under §3.307/§3.309, establishes direct service connection. Pull your service treatment records and look for every sick-call entry, line-of-duty determination, and separation-exam note that mentions the elbow, forearm, or arm, even an entry that was never formally worked up is powerful corroboration of onset.
2Continuity of symptoms, §3.303(b)
Where the record is thin, continuity of symptomatology can carry the claim. Consistent lay evidence that your elbow has hurt, weakened, or lost motion ever since service, from you, from family, and from those who served with you, is competent evidence under *Buchanan v. Nicholson* and can establish service connection on its own.
3Do not let it be folded into the shoulder
A genuine elbow or forearm condition must be evaluated on its own diagnostic codes, not swept into a single upper-extremity rating with the shoulder. If your decision lumped the two together, that is an under-rating you can challenge, the elbow has separate codes (5205–5213) and is entitled to a separate evaluation.
4Secondary, ulnar neuropathy, §3.310(a)
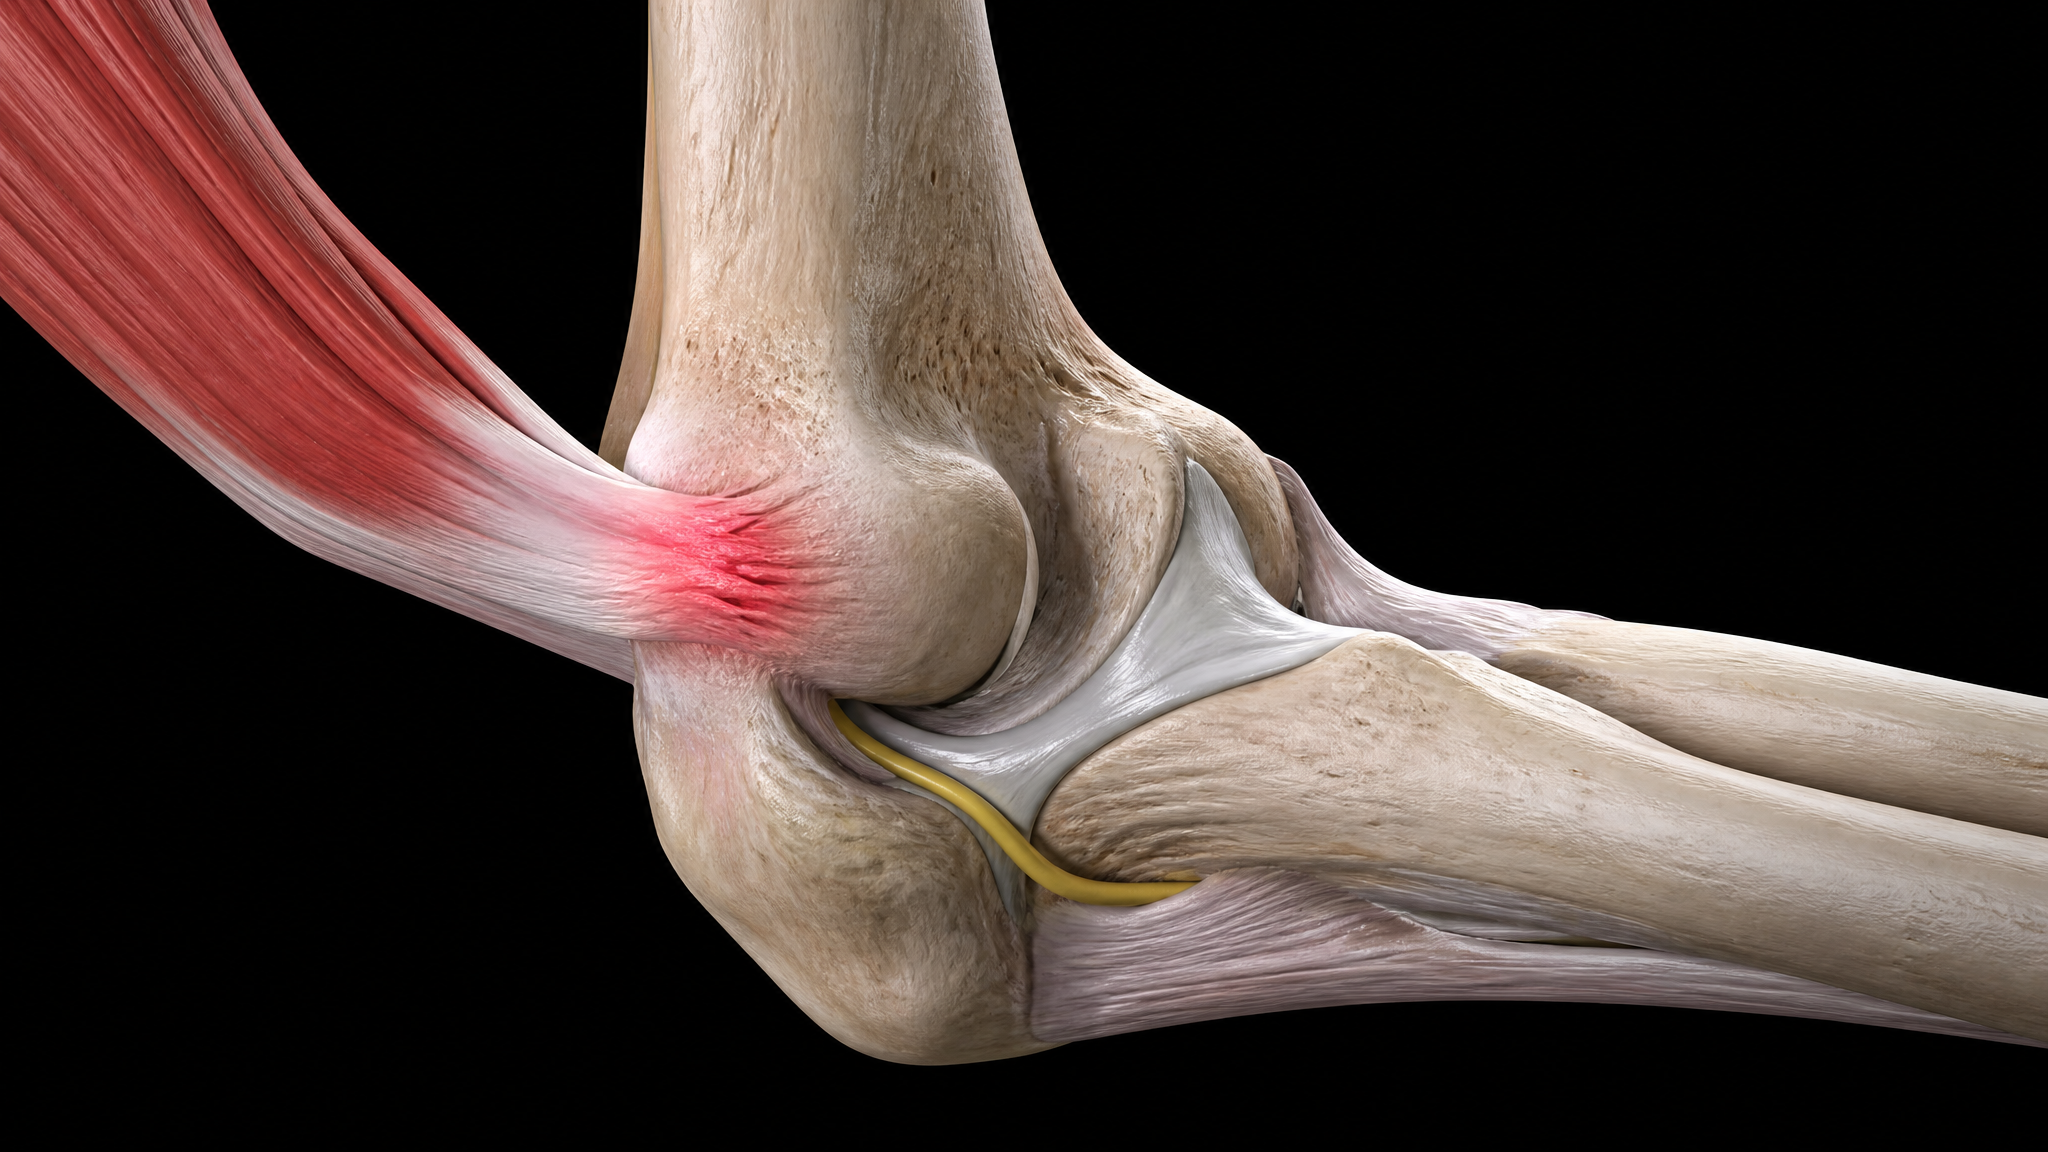
Ulnar nerve irritation at the cubital tunnel, numbness and tingling into the ring and little fingers, is a recognized complication of chronic elbow disability and is separately ratable under §4.124a. If you have those nerve symptoms, claim the neuropathy as secondary to the elbow condition for an additional, separate rating.
5Secondary, compensatory overuse, §3.310(a)
When one arm is impaired, the opposite arm and the same-side shoulder and wrist absorb the extra load and wear out faster. A condition that develops in the compensating joint is service connected on an aggravation or proximate-cause theory under §3.310, a nexus letter tying the new condition to the altered mechanics is the key evidence.
Exposure & Aggravation
Repetitive Load, Trauma & the Aggravation Path

The VA wants an in-service event, and most veterans think that means one dramatic injury. It does not. Years of duty that wore the body down count too, and under 38 CFR 3.306 a condition service made worse can still be connected. Find yourself in the list below, then put that duty in writing with dates, units and names. The board only weighs what you put on paper.
How veterans pick this up in uniform, Elbow & Forearm (DC 5205–5213)
Most service-connected elbow conditions do not come from a single dramatic injury, they come from years of repetitive load: ruck marches, weapons handling, low-crawling, and the manual-labor demands of physically demanding MOSs, punctuated by the occasional fall, parachute landing, or direct blow. Where a pre-existing elbow problem was made permanently worse by service, the aggravation rule applies: the VA must rate the increase in severity attributable to service, and it carries the burden of showing by clear and unmistakable evidence that any worsening was merely the natural progression of the condition.
- Repetitive load through the joint, ruck marches, weapons handling, low-crawling, and the manual-labor demands of infantry, artillery, engineer, and mechanic MOSs
- Acute trauma, a documented fall, vehicle accident, parachute landing, or direct blow that fractured or dislocated the elbow
- Overuse tendon injury, lateral epicondylitis (tennis elbow) and medial epicondylitis (golfer’s elbow) from repetitive gripping and lifting
- Post-surgical residuals, hardware, scarring, and lost motion following an in-service elbow or forearm surgery
- Ulnar nerve involvement at the cubital tunnel, years of leaning, load, and repetitive flexion that irritate the nerve behind the elbow
- Compensatory wear, an altered lifting and carrying pattern after a service-connected shoulder, wrist, or opposite-arm injury
Who is most prone to it
Veterans from infantry, airborne, artillery, engineer, motor-transport, and other physically demanding fields; anyone with a documented in-service elbow fracture, dislocation, or surgery; veterans who developed tennis or golfer’s elbow from repetitive gripping and lifting; and veterans whose elbow mechanics changed to compensate for a service-connected shoulder or wrist condition. The elbow is frequently under-claimed because veterans assume it is part of the shoulder, it is not, and it carries its own codes and its own rating.
The Symptoms
What Elbow & Forearm (DC 5205–5213) Actually Feels Like
Read this list the way the examiner will. Every symptom you live with but never report is a symptom the VA treats as if it does not exist. The rating schedule pays for how Elbow & Forearm (DC 5205–5213) affects your daily life and your work, so the details matter. Check off what matches your day, tell your doctor in those words, and make sure it lands in your treatment record before the exam.

- Pain deep in the elbow with lifting, pushing, pulling, or carrying, worse under load and after repetitive use
- Loss of full bend (flexion) or full straightening (extension) of the arm, measured in degrees against a normal 0–145° arc
- Difficulty turning the forearm palm-up or palm-down, trouble with a key, a doorknob, a screwdriver, or a coffee cup
- Grip weakness and dropped objects, the elbow and forearm feeding weakness into the hand
- Locking, catching, or a grinding sensation (crepitus) in the joint with motion
- Swelling, tenderness, or a bony deformity at the elbow after a fracture or over years of wear
- Numbness or tingling into the ring and little fingers, ulnar nerve irritation at the cubital tunnel
- Pain over the bony points of the elbow, lateral epicondylitis (tennis elbow) or medial epicondylitis (golfer’s elbow)
How this one is rated
Elbow and forearm conditions are rated under 38 CFR §4.71a, Diagnostic Codes 5205–5213. Limitation of flexion is rated under DC 5206 and limitation of extension under DC 5207, each on its own scale of measured degrees. Ankylosis, a fused, immobile joint, is rated under DC 5205 and carries the highest values, up to 50%/60%. Flail joint and impairment of the ulna and radius are rated under DC 5209–5212, and loss of forearm rotation (supination and pronation) under DC 5213. Under §4.69 the dominant (major) arm is rated higher than the non-dominant (minor) arm for the same impairment, and under §4.40/§4.45 painful motion and flare-ups must be factored into the final evaluation.
What you are measured against
Normal elbow motion for VA purposes is 0 degrees of extension to 145 degrees of flexion, with forearm supination of 0–85 degrees and pronation of 0–80 degrees. Every percentage in Codes 5205–5213 is measured against those arcs, on a goniometer, on both arms, active and passive. Flexion limited to 110° is noncompensable; 100° pays 10% and it steps up to 50% at 45°. Extension limited to 45° pays 10% and climbs to 50% at 110°. Limitation of supination to 30° or less is compensable on its own under DC 5213. Under *DeLuca v. Brown* and *Mitchell v. Shinseki*, the examiner must record the point at which pain begins and estimate the additional degrees lost during a flare-up or with repetitive use, the rating is built on your functional arc, not just the number you can reach once in a cold exam room.
Each One On Its Own Page
Secondary Conditions, Aggravated or Caused by a Current Service-Connected Condition
Under 38 CFR §3.310(a), a disability that is proximately due to a service-connected condition is service-connected in its own right, and under §3.310(b), so is any additional disability caused when a service-connected condition aggravates a problem you already had. Each condition below is a separate evaluation with its own diagnostic code and its own percentage. They do not fold into the elbow & forearm (dc 5205–5213) rating, they stack on top of it. A veteran who claims only the primary condition leaves these ratings on the table.

Ulnar neuropathy at the cubital tunnel
The ulnar nerve runs through a groove behind the elbow, the cubital tunnel, and chronic elbow disability irritates it. Numbness and tingling into the ring and little fingers, weakness in grip, and loss of fine motor control are the hallmarks. This is separately ratable under §4.124a as a peripheral nerve condition, on top of the elbow rating. If you have those symptoms, claim the neuropathy as secondary to the elbow under §3.310(a) for an additional, separate percentage.
The opposite arm, the shoulder, and the wrist
When one arm is impaired, the other arm, the same-side shoulder, and the wrist absorb the extra load and wear out faster. A condition that develops in the compensating joint is service connected on a proximate-cause or aggravation theory under §3.310(a). Report the new aches in the good arm, the shoulder that now does all the overhead work, and the wrist that carries everything the injured elbow cannot, they are evidence, not complaints.

Depression, lost work, and the TDIU question
An elbow you cannot trust makes trades work, manual labor, and any job requiring grip strength or lifting impossible. That is a straight line to TDIU under §4.16, the disability that makes you unemployable. The mental health toll of chronic pain and lost function is separately compensable as depression or anxiety secondary to the elbow condition under §3.310. Document every work task the elbow has taken away and every shift you have missed.
Accredited Claims Agent #45147
Ready To Get This Rated Correctly?
You have read how the VA rates Elbow & Forearm (DC 5205–5213). Now the question is whether your file proves it. We represent veterans on a No Win, No Fee basis: 20% Direct-Pay paid by the VA from back pay, or 30% High-Complexity, and you owe nothing for representation if your rating does not increase. If you only need the roadmap, the Mission 5 Brief is a separate $750 flat fee. You bring the records, we build the argument.
Elbow & Forearm Conditions, In Detail
Elbow & Forearm Conditions, Service Connection In Depth
Here is each claimable condition in this group on its own terms, what it is, what service did to it, and what the VA requires before it will connect it.

Elbow & Forearm Conditions, Limitation of Motion & Bone Impairment
The elbow is a deceptively complex joint, and the VA rates it on four separate motions plus the condition of the two forearm bones. Under 38 CFR §4.71a, Diagnostic Codes 5205–5213, your rating is built from measured flexion and extension, from ankylosis if the joint has fused, and from nonunion, malunion, or flail-joint impairment of the ulna and radius. Forearm rotation, supination and pronation, the motion you use to turn a key, a doorknob, or a screwdriver, is rated on its own scale under Code 5213 and can be compensable entirely on its own. The rating turns on two things veterans routinely lose points on. The first is measured motion with pain considered: under §4.40 and §4.45, and under *DeLuca* and *Mitchell*, the examiner must record where pain begins and estimate the additional loss during a flare-up, an exam that only reports the end of the arc is inadequate. The second is the dominant-hand rule under §4.69: the identical limitation pays more on your dominant arm, so the examiner recording your handedness correctly is worth real money. Above all, do not let an elbow or forearm condition be folded into your shoulder claim. It has its own diagnostic codes, and it deserves its own rating.
You are reading this page now
The C&P Exam
What To Expect At The Elbow & Forearm (DC 5205–5213) Exam
This is the encounter your rating is built on. The examiner has a checklist and a limited window, what follows is exactly what happens in that room, so none of it surprises you.
Clinical Section, What To Expect at the Exam
What to Expect at Your Elbow & Forearm C&P Examination
Diagnostic Codes 5205–5213, measured motion, forearm rotation, and the dominant-hand designation decide everything
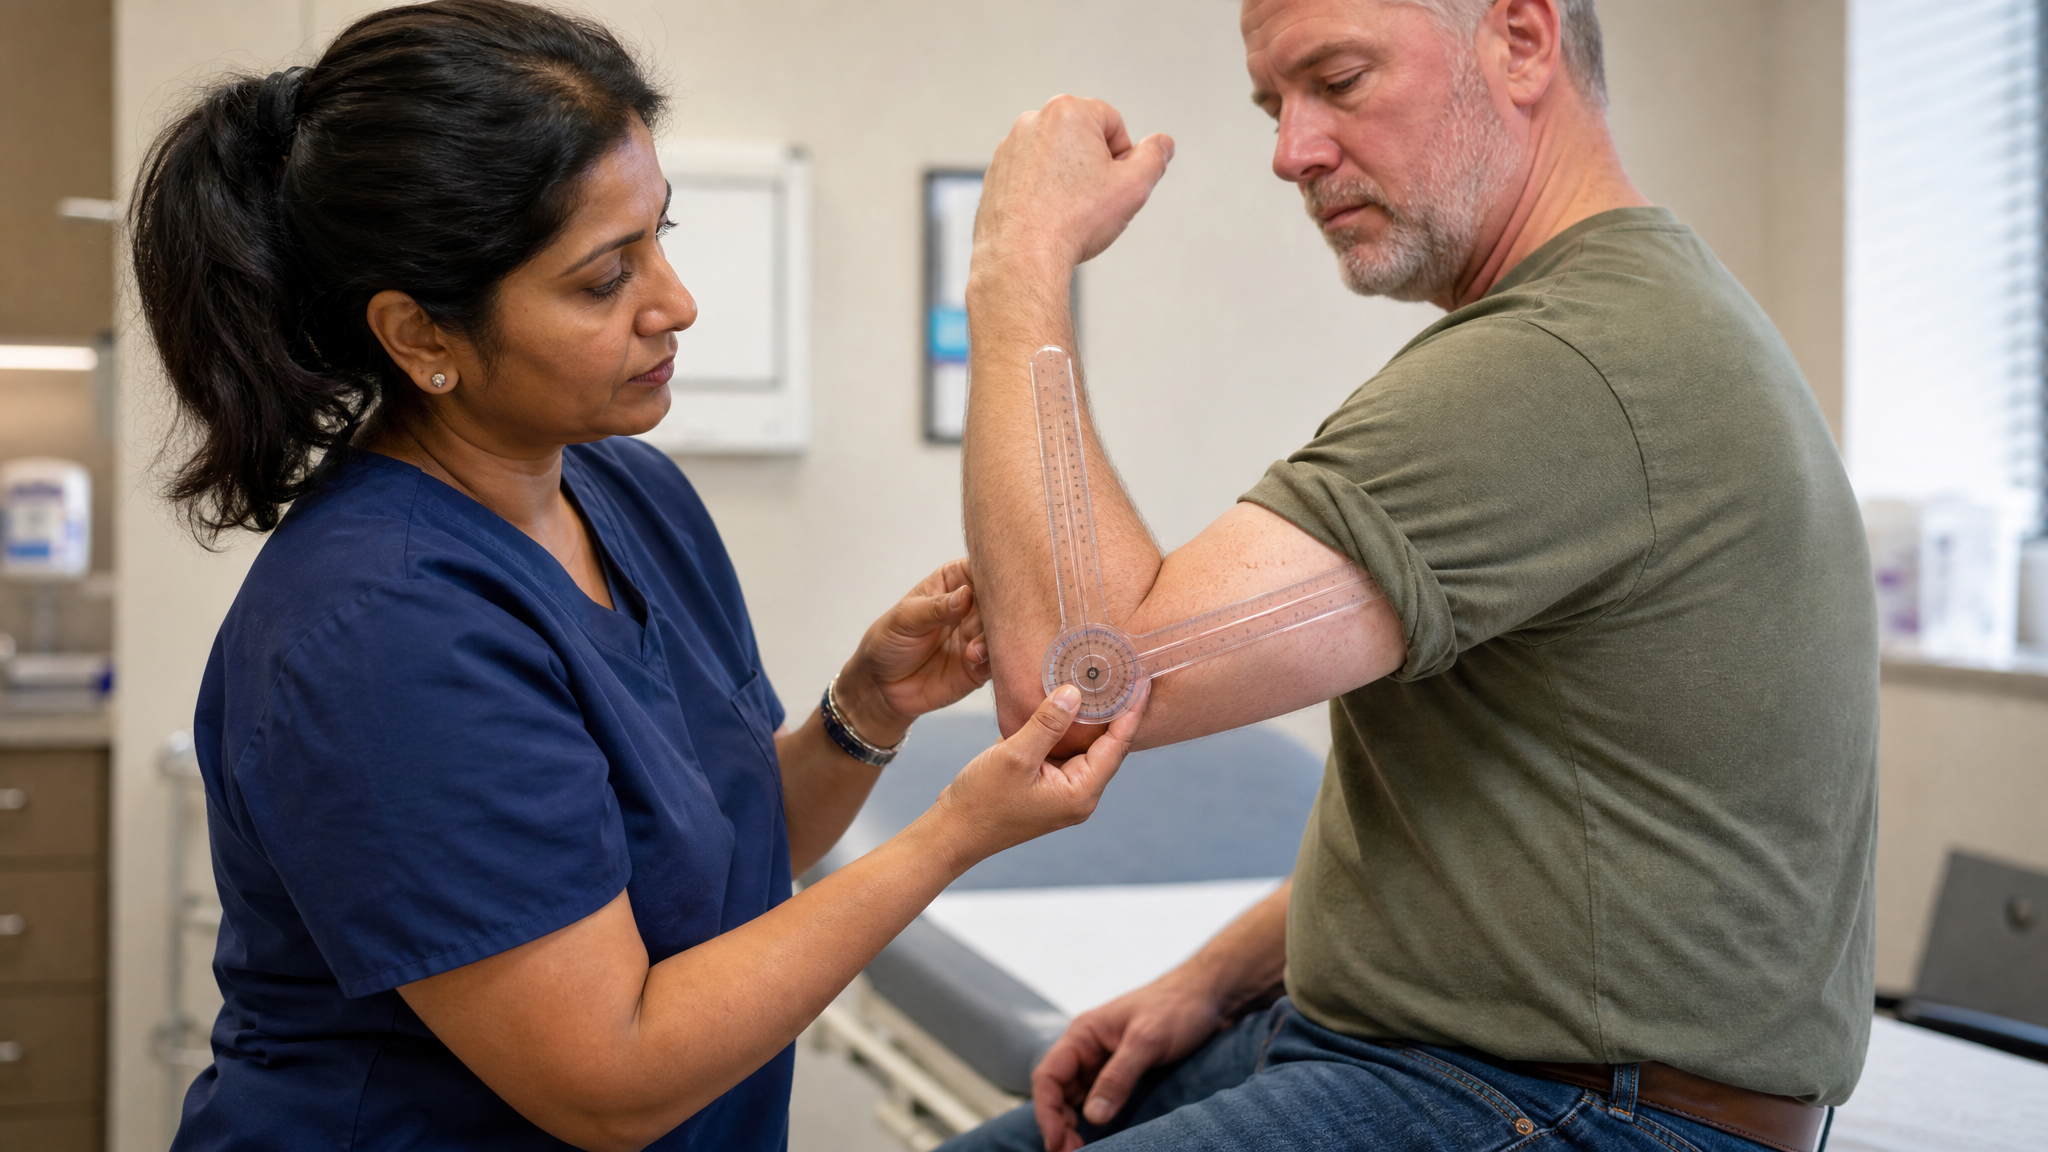
The elbow exam is a range-of-motion exam, and the whole outcome turns on how carefully the examiner measures and records what happens in that room. The elbow is rated on **four separate motions**, flexion, extension, supination, and pronation, and each is measured with a **goniometer**, on **both arms**, active and passive. The examiner should record your **handedness** first, because Diagnostic Codes 5205 through 5213 pay different amounts for the **major (dominant)** and **minor (non-dominant)** arm. The most damaging mistakes are an examiner who measures only the elbow and forgets that **forearm rotation is rated separately** under Code 5213, and an examiner who records only the end of your motion without noting where **pain begins** or estimating the **additional loss during a flare-up**. Under *DeLuca* and *Mitchell*, that flare and painful-motion analysis is required, an exam that skips it is legally inadequate. Bring your imaging, describe your worst days, and make sure every one of the four motions is measured and written down.
Condition
Elbow & Forearm (DC 5205–5213), DC 5205–5213
Governing questionnaire
VA Form 21-0960M-2, Elbow and Forearm Conditions Disability Benefits Questionnaire, goniometer-measured flexion and extension, forearm supination and pronation, stability testing, and the impact of pain and flare-ups
Click the form number to open the official questionnaire on VA.gov.
01In The Room
What happens during the exam
The tests and maneuvers for this condition
- Handedness recorded, because Diagnostic Codes 5205 through 5213 all pay different amounts for the major and minor arm
- Goniometer measurement of elbow flexion and extension, both arms, active and passive
- Separate measurement of forearm supination and pronation, limitation of supination to 30 degrees or less is compensable on its own under Diagnostic Code 5213
- Repetitive-use testing, the point at which pain begins, and a flare-up estimate expressed in degrees
- Stability testing for the ulnar and radial collateral ligaments, and examination for cubitus varus or valgus deformity
- Palpation and provocative testing for lateral and medial epicondylitis (tennis and golfer’s elbow)
- Examination for ulnar nerve involvement at the cubital tunnel, an ulnar neuropathy is separately ratable under 38 CFR §4.124a
- Imaging review for ununited radial head fracture, nonunion or malunion of the radius or ulna, and any loss of bone substance measured in centimeters
What gets measured, and to what number
Elbow flexion (bending)
Measured against a normal 0–145° arc. Flexion limited to 100° pays 10%, stepping up to 50% at 45° on the major arm. This is the primary driver of the DC 5206 rating.
Elbow extension (straightening)
Measured as the degrees short of full straightening. Extension limited to 45° pays 10% and climbs to 50% at 110° on the major arm under DC 5207.
Forearm supination (palm-up rotation)
Normal 0–85°. Limitation to 30° or less is compensable on its own under DC 5213, a motion examiners frequently forget to measure.
Forearm pronation (palm-down rotation)
Normal 0–80°. Loss of pronation is rated on its own scale under DC 5213, up to 30%/40% where the hand is fixed in supination or hyperpronation.
Dominant vs. non-dominant designation
Your handedness under §4.69 decides which column of the rating table applies, the same limitation is worth more on the dominant (major) arm.
Ankylosis and bone impairment
A fused joint (DC 5205), flail joint (DC 5209), or nonunion/malunion of the ulna or radius (DC 5210–5212) carry the highest values, up to 60% for the major arm.
Painful motion and flare-up loss
The point where pain begins and the estimated additional degrees lost during a flare or with repetitive use, per §4.40/§4.45 and DeLuca/Mitchell.
02Orientation
What to expect during this exam
What makes this exam different from every other C&P exam
1The elbow is rated on four motions, not one
Flexion and extension are measured on their own scales, and forearm supination and pronation are rated separately under DC 5213. Limitation of supination to 30 degrees or less is compensable entirely on its own, make sure forearm rotation is measured, not skipped.
2The dominant-hand rule changes the payout
Under §4.69 the identical limitation pays more on your dominant (major) arm than on your non-dominant (minor) arm. Confirm the examiner records your handedness correctly, it decides which column of the table you are rated in.
3Pain and flare-ups must be in the numbers
Under §4.40, §4.45 and DeLuca/Mitchell, the examiner must note where pain begins and estimate the additional degrees lost during a flare-up or with repetitive use. An exam that reports only the end of the arc understates your disability and is inadequate.
See it before you sit in the room
03Preparation
Know your symptoms and secondary factors
What the report must actually say about elbow & forearm (dc 5205–5213), dc 5205–5213
- "My dominant hand is my [right/left] hand", establish handedness so the examiner rates you in the correct §4.69 column.
- "My pain starts at [X] degrees, well before I reach the end of my motion", put the DeLuca painful-motion point on the record.
- "During a flare-up I lose roughly [X] more degrees and cannot [lift / turn / carry]", force the required flare-up estimate.
- "I cannot turn my forearm palm-up or palm-down, I struggle with a key, a doorknob, and a screwdriver", flag the separately-rated forearm rotation under DC 5213.
- "I get numbness and tingling into my ring and little fingers", open a separate ulnar-neuropathy rating under §4.124a.
- "This is my elbow, not my shoulder, I want it rated on its own codes", prevent the under-rating that folds the elbow into the shoulder.
Pain level, frequency, lost work and functional loss, how to say them
Describe the motion you cannot make, flexion, extension, and rotation as three separate losses
The rating schedule rates each motion on its own ladder. Flexion limited to 100 degrees is 10 percent under DC 5206. Extension limited to 45 degrees is 10 percent under DC 5207. Limitation of supination to 30 degrees is 10 percent under DC 5213. If you lump them into "my elbow hurts," the examiner picks one number and the others disappear. Say each motion separately and describe the point in the arc where it stops or where it starts to hurt, that is the number the rating is built on.
Demonstrate each motion in the room: bend the arm, straighten it, turn the palm up, turn it down. If one is worse than the others, say so.
"I can bend it to about here, maybe 90 degrees, and then it locks. Straightening it out, I lose the last 20 or 30 degrees. And turning my palm up is maybe halfway."

State your hand dominance before the examiner starts
Under §4.69, the identical limitation is worth more on your dominant (major) arm than on your non-dominant (minor) arm. For example, forearm flexion limited to 55 degrees is 30 percent on the minor arm and 40 percent on the major arm under DC 5206. The examiner must record your handedness on the DBQ, if it is wrong or missing, the percentage is built on the wrong column.
Say it at the very start: "I am right-handed and this is my right elbow." Confirm it is recorded before any measurements begin.
"Before we start, I am right-handed, and this is my dominant arm. That matters for the rating."

Report the flare-ups with a count and a calendar
Sharp v. Shulkin requires the examiner to estimate additional functional loss during a flare. Without your count, how many bad days, how long they last, what triggers them, the examiner writes "cannot estimate" and your rating is built on a good day. Come with the numbers already counted.
Go back twelve months and count: bad days per month, duration of each, and what you could not do. Bring the list and read it aloud.
"I get a bad flare two or three times a month. Each one lasts two to three days. During a flare I cannot grip a coffee mug or turn a steering wheel."

Name every task the elbow has taken from you, grip, twist, lift, carry
Functional loss under §4.40 is the currency of the rating schedule. "My elbow hurts" gets logged as pain. "I cannot turn a doorknob, I cannot carry a bag of groceries, I dropped three things last week" gets logged as functional impairment, and that is what converts a diagnosis into a percentage. Tasks are verifiable; sensations are not.
Map the tasks to the motions: gripping is flexion strength, turning a key is forearm rotation, reaching overhead with a straight arm is extension. The examiner can cross-check your account against the goniometer.
"I cannot turn a doorknob with that hand. I cannot carry anything over ten pounds. I dropped a pan last week because my grip gave out mid-lift."
Tell them forearm rotation is limited, supination and pronation separately
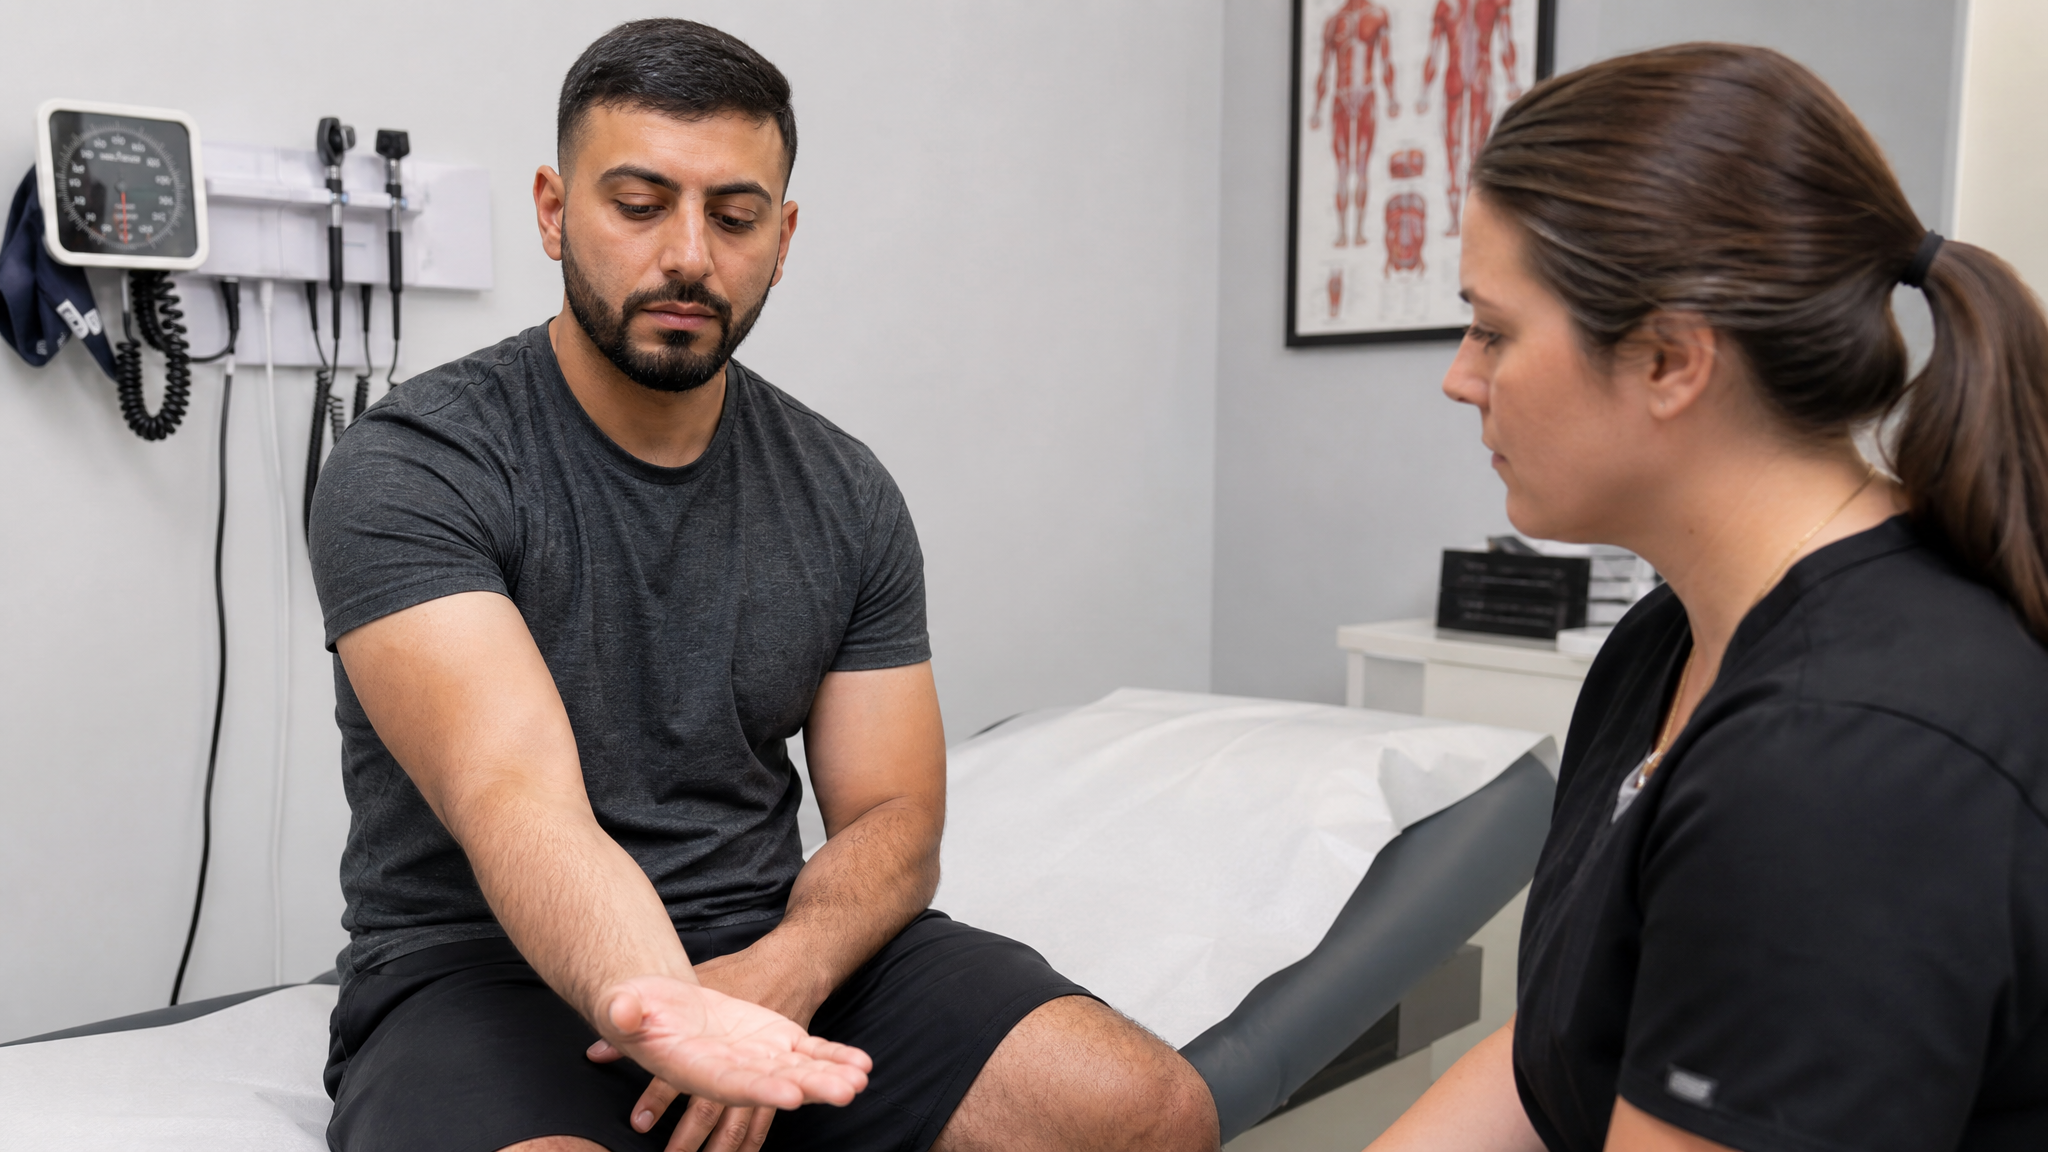
DC 5213 rates loss of forearm rotation on its own scale, and most examiners never measure it. Limitation of supination to 30 degrees or less is 10 percent. Loss of rotation fixed in full pronation is 20 percent (minor) or 30 percent (major). If you do not say it, and the examiner does not test it, a whole ratable motion disappears from the report.
Demonstrate it in the room: hold your forearm out and try to turn your palm all the way up, then all the way down. Show where it stops.
"My forearm will not rotate all the way, I cannot turn my palm fully up. It stops about halfway through supination."
Secondary conditions to raise in the same appointment
Every secondary condition laid out in the Secondary Conditions section above belongs in this same appointment. Name each one out loud, tell the examiner how the primary condition caused it or made it worse, and ask that it be noted in the report. Under 38 CFR 3.310, a secondary condition the examiner never hears about is a secondary condition the VA never rates. Bring your list on paper so nothing gets left in the parking lot.
What to expect at this specific exam
- Bring copies of any X-ray, MRI, or CT reports showing arthritis, an ununited radial head fracture, or nonunion/malunion of the ulna or radius, with any loss of bone substance noted in centimeters.
- Write down, before the exam, the degrees at which your pain starts and what a bad flare-up costs you in motion and function.
- List the daily tasks the elbow and forearm limit, lifting, carrying, turning a key or doorknob, using tools, in concrete terms.
- Know and state your dominant hand, and be ready to correct the examiner if it is recorded wrong.
- If you have numbness or tingling into the hand, describe it clearly so ulnar neuropathy is documented and can be claimed separately.
- Do not mask the pain before the exam, the examiner needs to see your true functional limitation, and the point where pain begins is part of the rating.
04The Protocol
What procedures are required during the exam
These are not courtesies. Each comes out of the regulation or out of binding case law. Take this list in with you and tick them off as they happen.
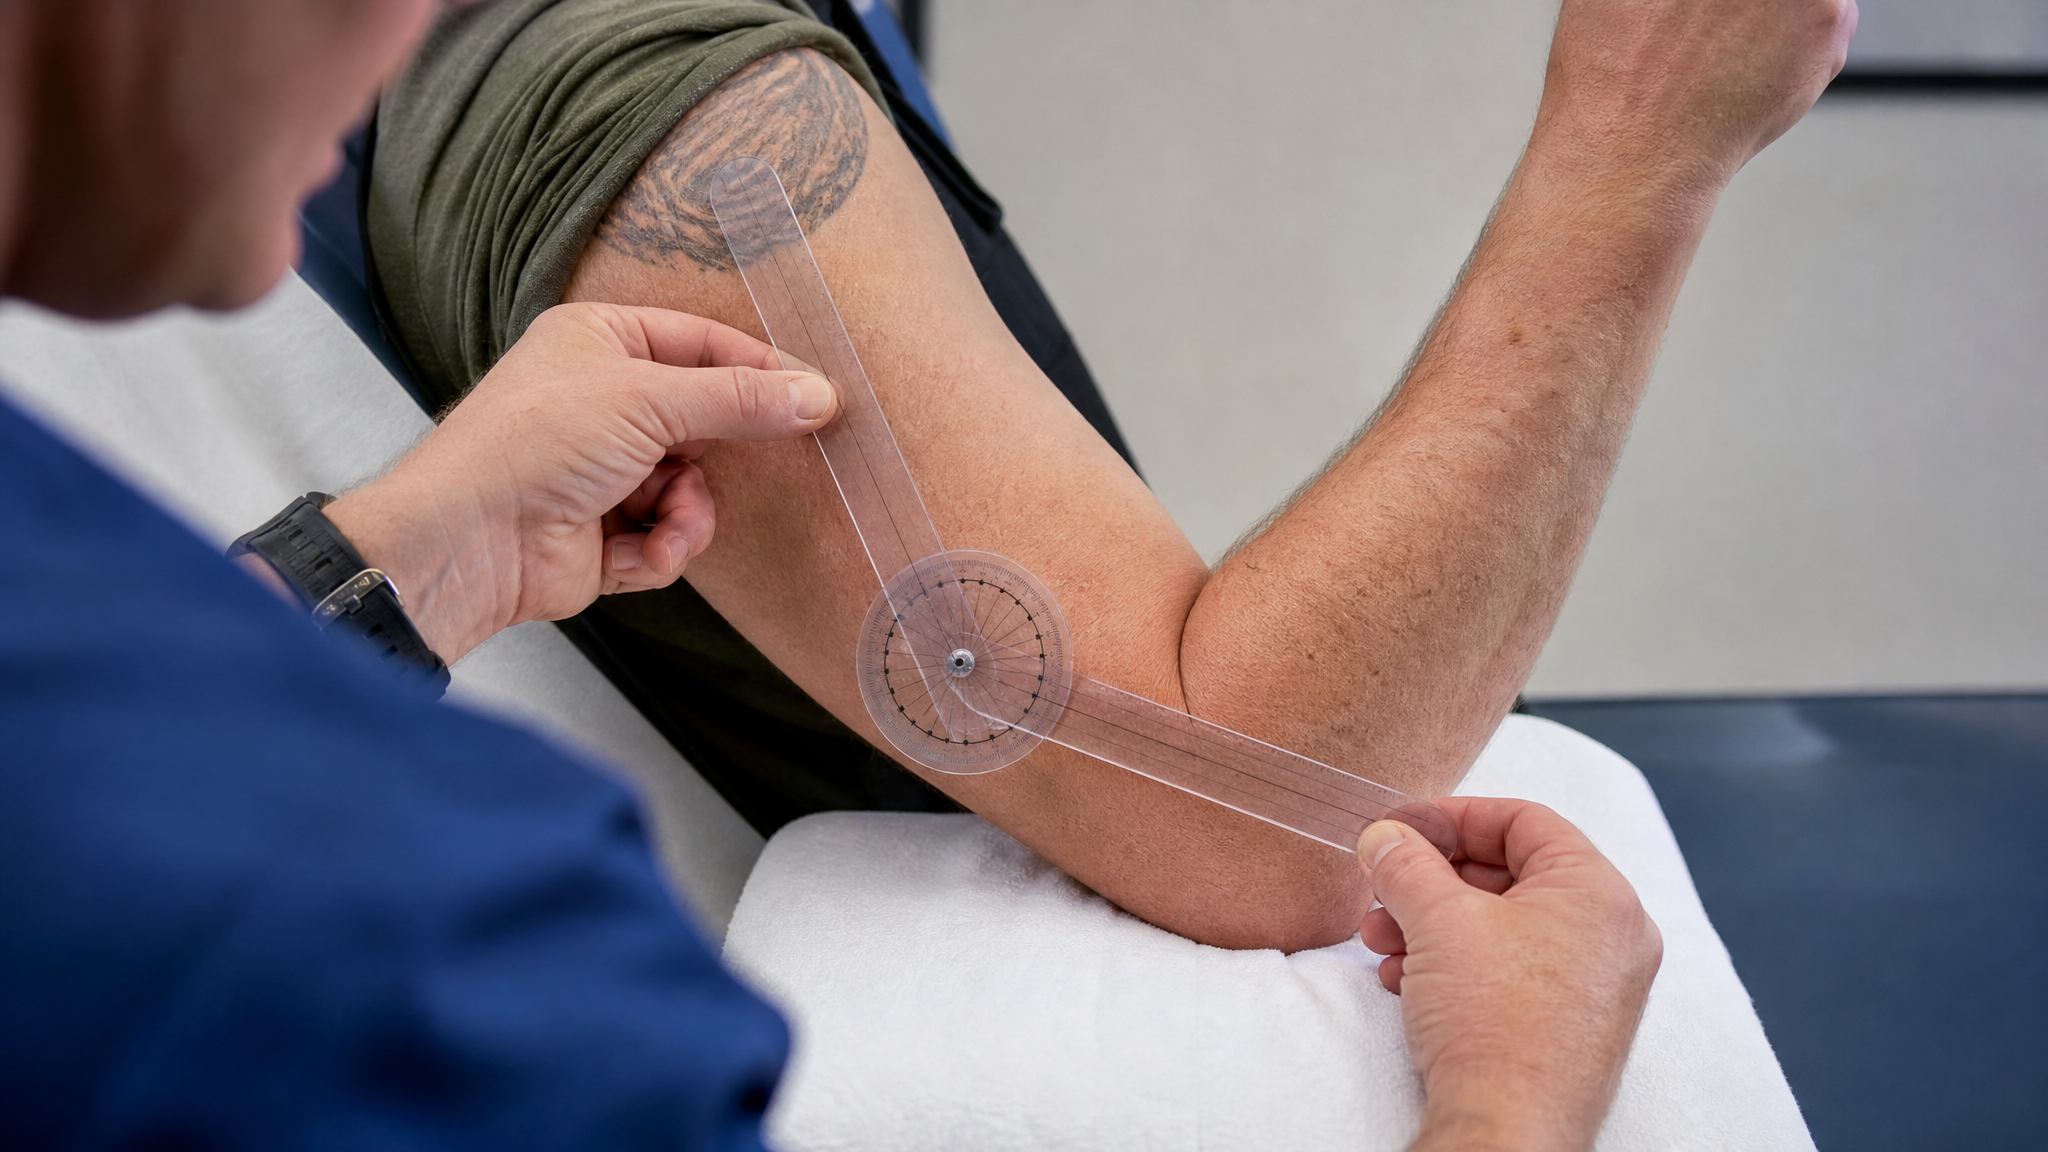
01Measured range of motion with a goniometer, flexion and extension
38 CFR §4.46
Active motion in flexion (0–145 degrees normal) and extension (145–0 degrees), recorded in degrees, taken with the hinged instrument. 38 CFR §4.46 calls the goniometer indispensable. Eyeballed numbers are not compliance. The examiner aligns the stationary arm with the lateral epicondyle, follows the moving arm through your arc, and writes an actual number in each field.
The entire rating formula for DC 5206 and 5207 is a ladder of degree thresholds. A missing or invented measurement is not a paperwork problem, it is the difference between a compensable rating and a zero. Round symmetrical figures across every plane are a fingerprint of estimation, not measurement.
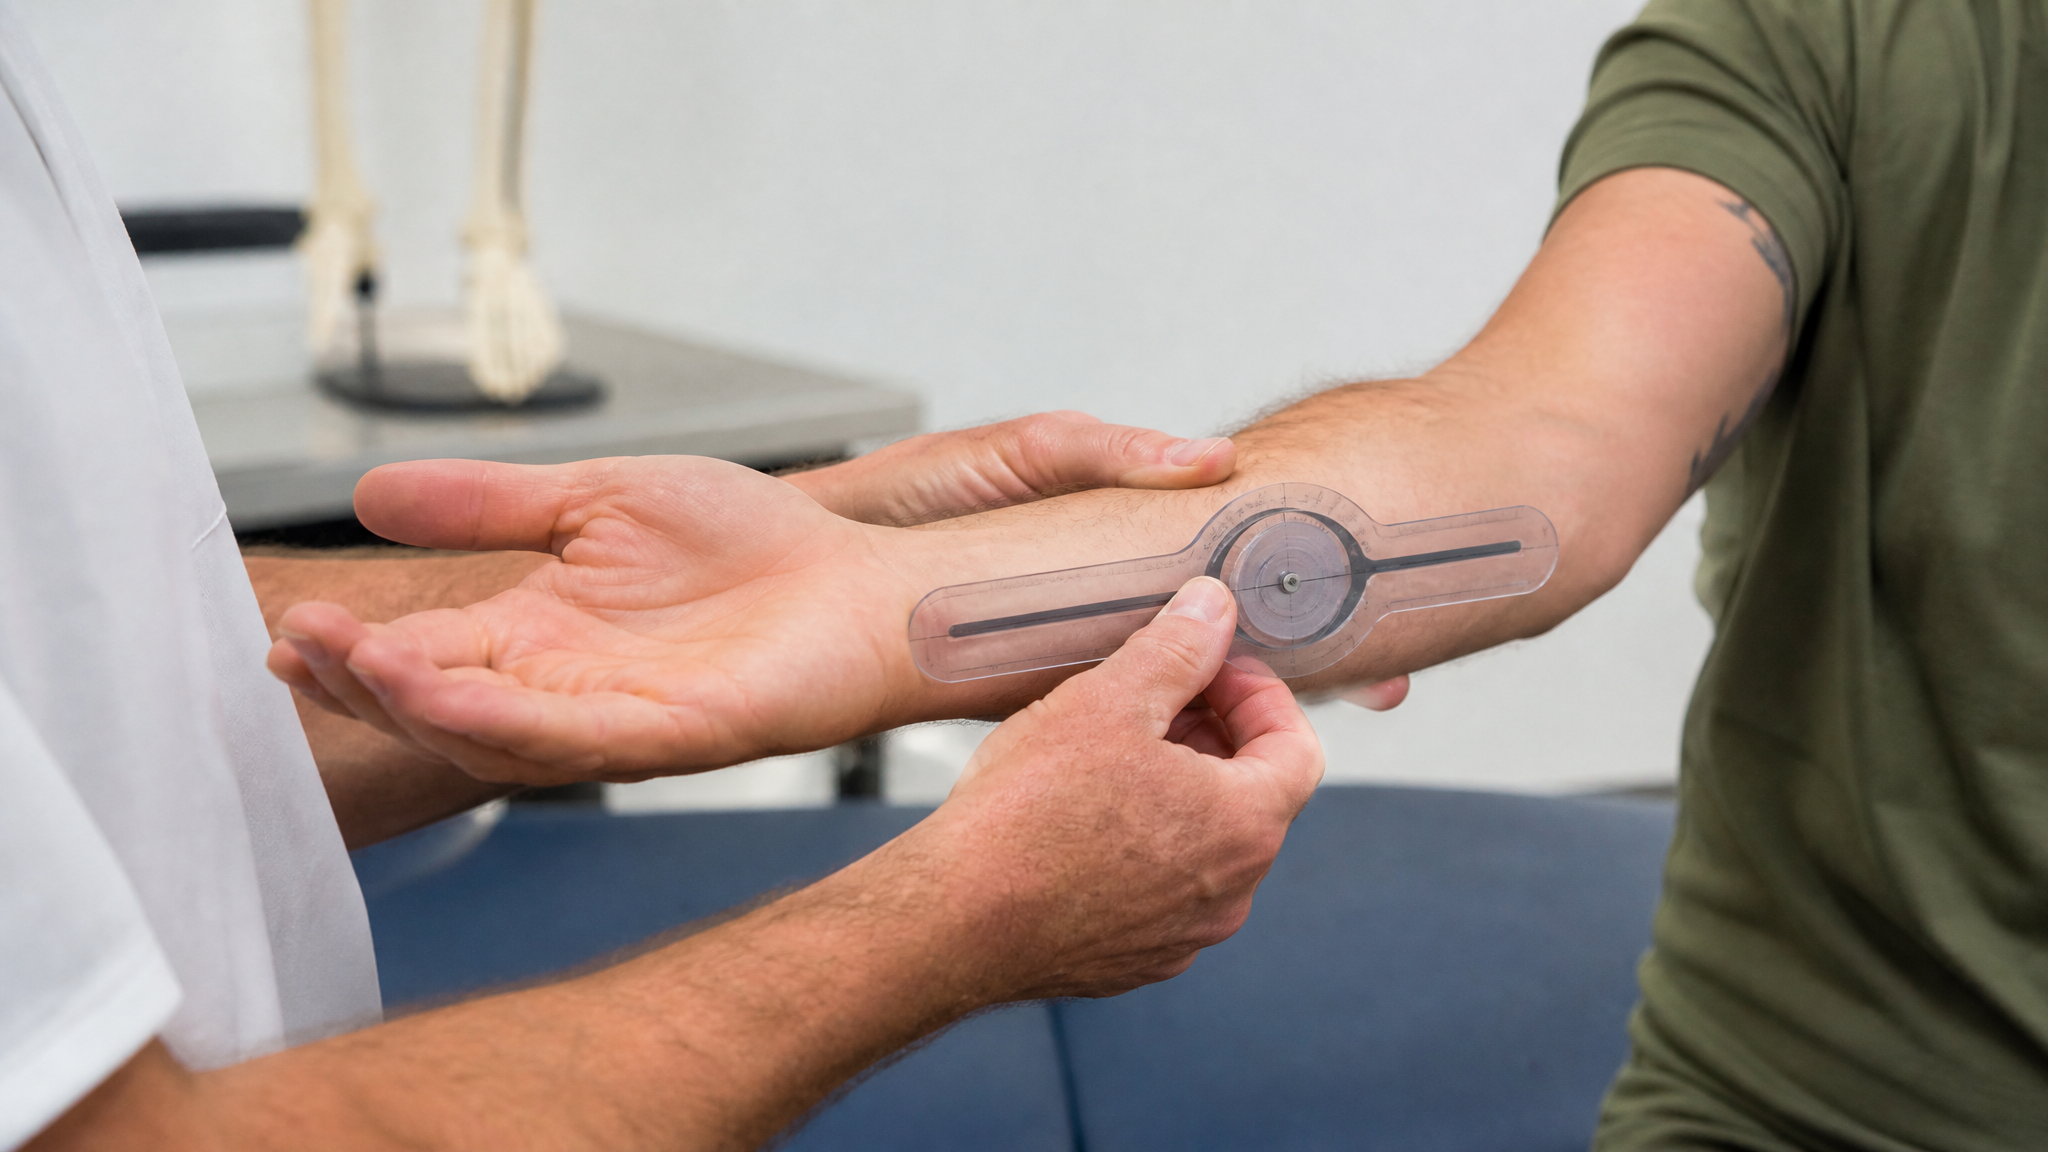
02Forearm rotation, supination and pronation measured separately
38 CFR §4.71a, DC 5213
DC 5213 rates loss of forearm rotation on its own scale, and it is the single most commonly skipped measurement in an elbow exam. The examiner must measure how far you can turn your palm up (supination, normal 0–85 degrees) and down (pronation, normal 0–80 degrees), and record the numbers. If rotation is not measured, a whole ratable motion disappears from the report.
Limitation of supination to 30 degrees or less is compensable at 10 percent. Loss of rotation fixed in supination or hyperpronation reaches 30 percent (minor) or 40 percent (major). An exam that measures only flexion and extension and skips rotation has quietly deleted half of what the diagnostic code set covers.

03Repetitive use testing, three reps minimum
38 CFR §4.40 / §4.45 · DeLuca
Three repetitions of each movement minimum, with the post-repetition measurements recorded and any additional loss expressed in degrees where feasible. DeLuca and §4.40/§4.45 require the examiner to account for what happens with use: fatigue, weakness, loss of coordination, and the extra loss of motion that follows.
A single cold repetition is the best your body will perform all day. If the third rep is worse than the first, less range, more pain, a catch or a click, that is the finding. A form that records identical figures before and after repetition, with the fatigue box left blank, has skipped the step entirely.
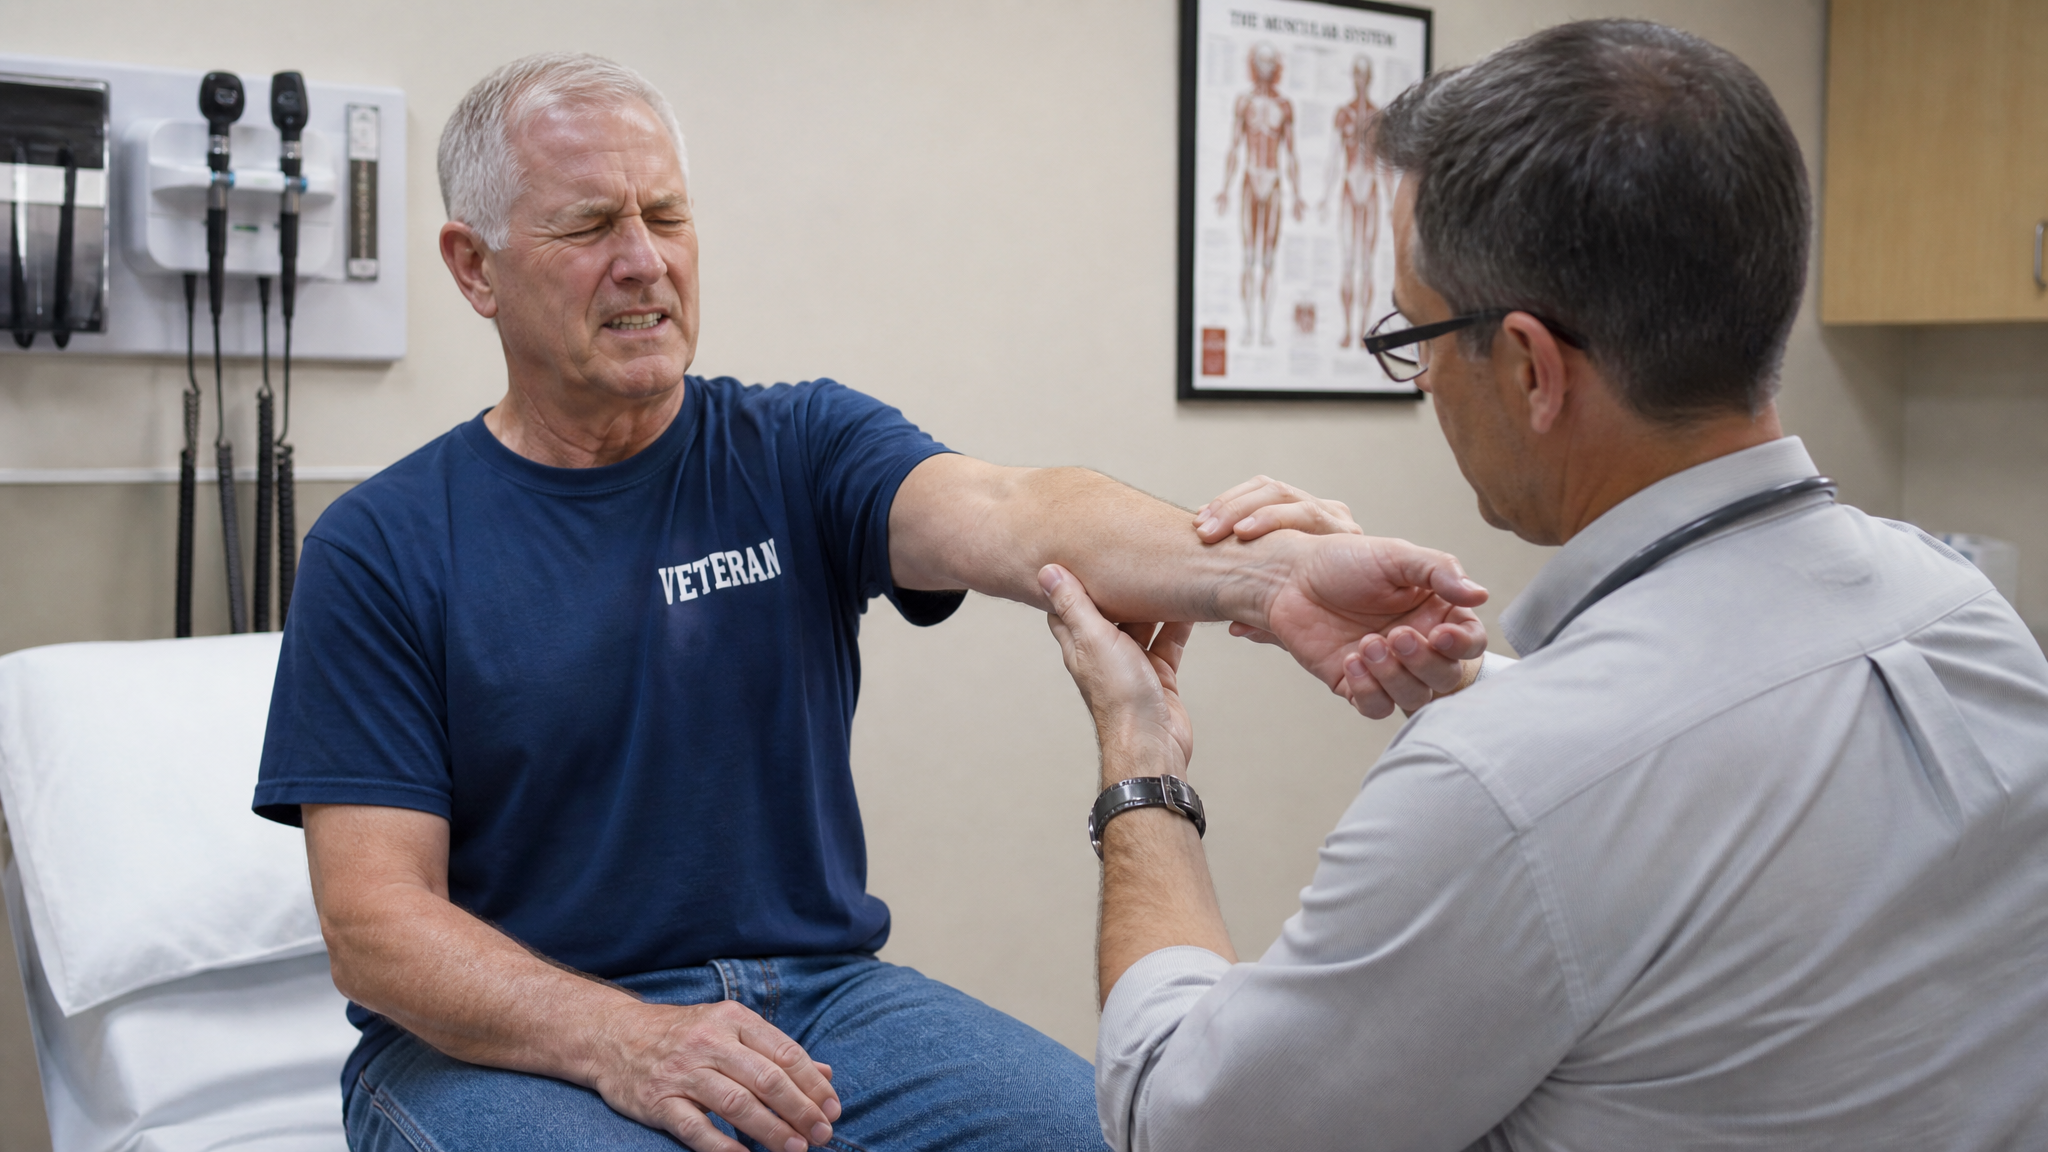
04The point at which pain begins and a flare-up estimate
38 CFR §4.59 · Sharp v. Shulkin
The examiner must record the degree at which objective evidence of painful motion starts, not just the end range, and must seek your account of flare-ups and estimate the additional functional loss during a flare, or explain specifically why an estimate cannot be made.
§4.59 entitles you to consideration at the point painful motion begins. Sharp v. Shulkin closed the oldest loophole: the examiner can no longer write "cannot estimate without resorting to speculation" and walk away. Come prepared with specifics: how many bad days a month, how long they last, what you cannot do. "It flares sometimes" gives the examiner room to write nothing.
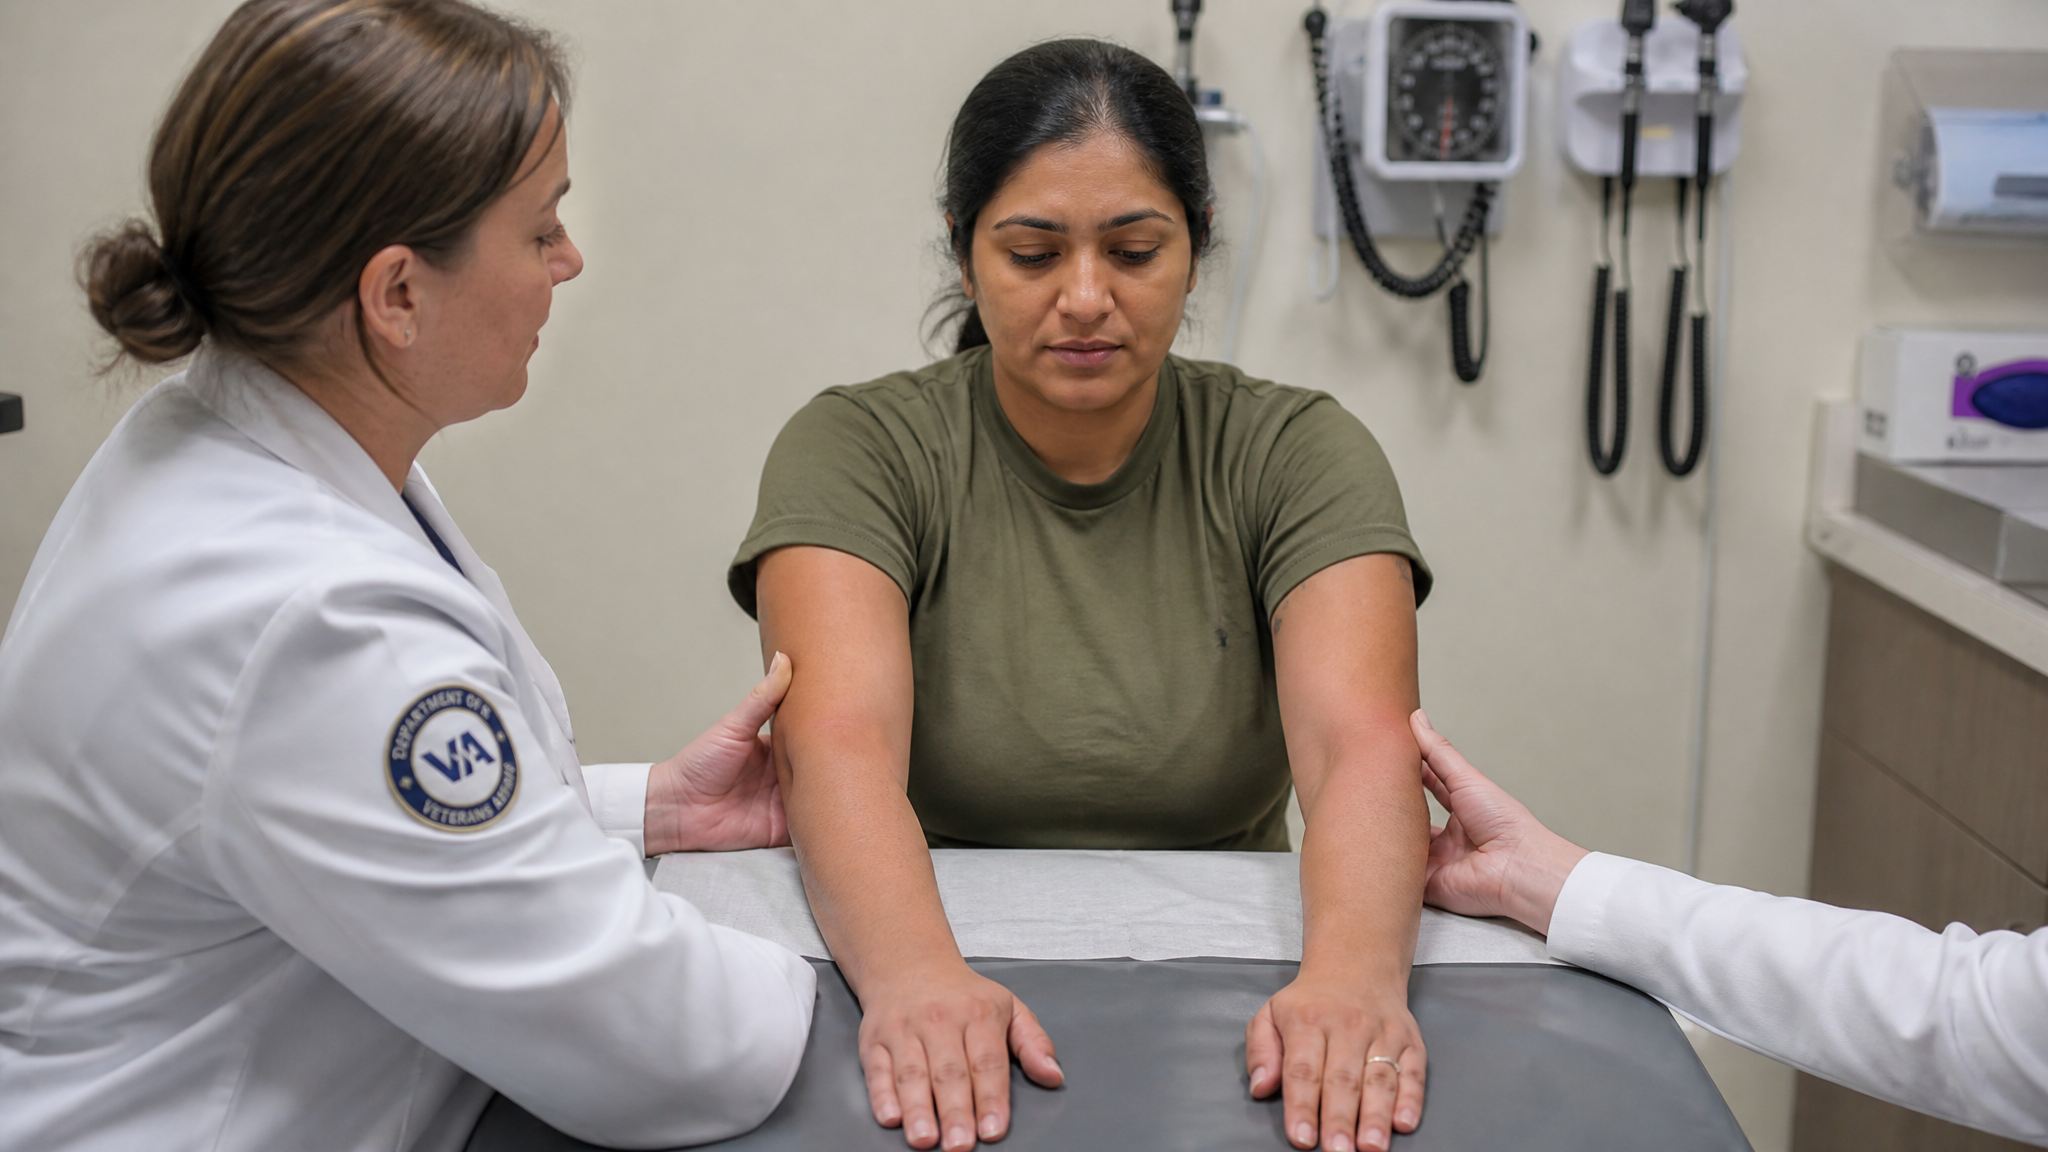
05Bilateral comparison, both elbows, all four test conditions
Correia v. McDonald
The examiner must test active, passive, weight-bearing and non-weight-bearing motion wherever possible, and compare the injured elbow against the uninjured one. One set of numbers on one arm in one condition is an incomplete examination.
Correia v. McDonald held that a joint examination is incomplete unless it tests in all four conditions where practical and pairs the damaged joint against the undamaged one. Four separate measurements, not one number copied across four boxes. If a condition genuinely cannot be tested, the examiner must say so and explain why, silence is not an explanation. This is one of the most common grounds on which the Board remands a claim.
05The Standard
What makes an exam adequate
Read your exam report against these. An exam that fails the standard is legally inadequate, and an inadequate exam is something you challenge rather than accept.
The range of motion has to be MEASURED, not estimated
38 CFR §4.46 states that the use of a goniometer in the measurement of limitation of motion is indispensable in examinations conducted within the Department of Veterans Affairs. An examiner who eyeballs your bend and writes a number has not complied with the regulation. This is the most common defect in a spine exam and it is the easiest one to spot from the chair.
Joints must be tested in every required condition
Under Correia v. McDonald, a joint examination for pain must, wherever possible, record active motion, passive motion, motion in weight-bearing and motion in non-weight-bearing, and where relevant, the range of the opposite undamaged joint. An exam that records one set of numbers and stops is incomplete on its face, and that incompleteness is grounds to challenge it.
Flare-ups have to be addressed, not dodged
Under Sharp v. Shulkin, when a veteran describes flare-ups, the examiner is obligated to estimate the additional loss of motion during a flare based on all the available evidence, including your own account of it. "I cannot opine without resorting to mere speculation" is not automatically acceptable; the examiner has to have actually sought the information first and explained why an estimate is impossible.
Repetitive use and functional loss must be factored in
Sections 4.40 and 4.45, and the DeLuca line of cases, require that pain, weakness, fatigability, incoordination and lack of endurance after repeated use be considered, and expressed in additional degrees of lost motion where that is feasible. Your rating is supposed to reflect what you can do on the fifth repetition and on a bad day, not just the first careful bend of the morning.
Neurological findings must be separately documented
Note (1) to the General Rating Formula requires that any associated objective neurologic abnormality be evaluated separately under an appropriate diagnostic code. If your leg symptoms were mentioned in the narrative but never tested and never assigned, the exam did not do what the schedule requires of it.
The examiner must review the record when the question requires it
Where a medical opinion on cause, aggravation or a secondary relationship was requested, the examiner is expected to review the relevant evidence and give a reasoned explanation. A bare conclusion, "less likely than not related to service" with no reasoning attached, carries little weight, and an opinion with no rationale is challengeable.
The examiner has to be qualified for the body system
The VA may use its own clinicians or a contract vendor. Either way, the examiner is expected to have the competence to evaluate the system being examined. If a spinal exam with a neurological component was performed by someone who never tested a reflex, that is a problem worth raising.
The exam has to be CURRENT
A rating is supposed to reflect your condition now. An exam performed before a documented worsening, or years before the decision, may not support the current evaluation, and you can request a new one on that basis.
06Afterward
What happens after your exam is complete
The examiner writes the report and submits it, it is reviewed for completeness, and only then does the claim move toward a rating decision. Here is what actually controls the clock.

The examiner writes and submits the report
Days 1–5 after the exam
The examiner compiles the history, the physical findings, the measurements and any testing into the questionnaire, adds any requested medical opinion, and submits it. Contract vendors typically have a turnaround requirement measured in days, not weeks.
Nothing about your claim moves while this is happening, and nothing you do speeds it up. What matters is that the report is written from notes taken in the room, which is exactly why what you said, and how the examiner recorded it, is already locked in by the time you get to your car. Request your copy now rather than later.

Quality review, and the request for clarification
Days 3–30
The report is reviewed for completeness. If it is internally inconsistent, missing a required field or missing the opinion the VA asked for, it goes back for correction or a second opinion. This is the single most common cause of a claim appearing to stall after the exam.
Understand what a finished exam actually means: it means the appointment happened, not that your claim is ready for a decision. If the reviewer finds a blank range-of-motion field, an opinion that does not answer the question that was asked, or findings that contradict each other, the file goes back out for more information. That is a normal quality control step, not a rejection of your claim, and it is not a sign that you did something wrong, but it does add weeks, and it is the reason so much of what you read online sounds like the system is broken.
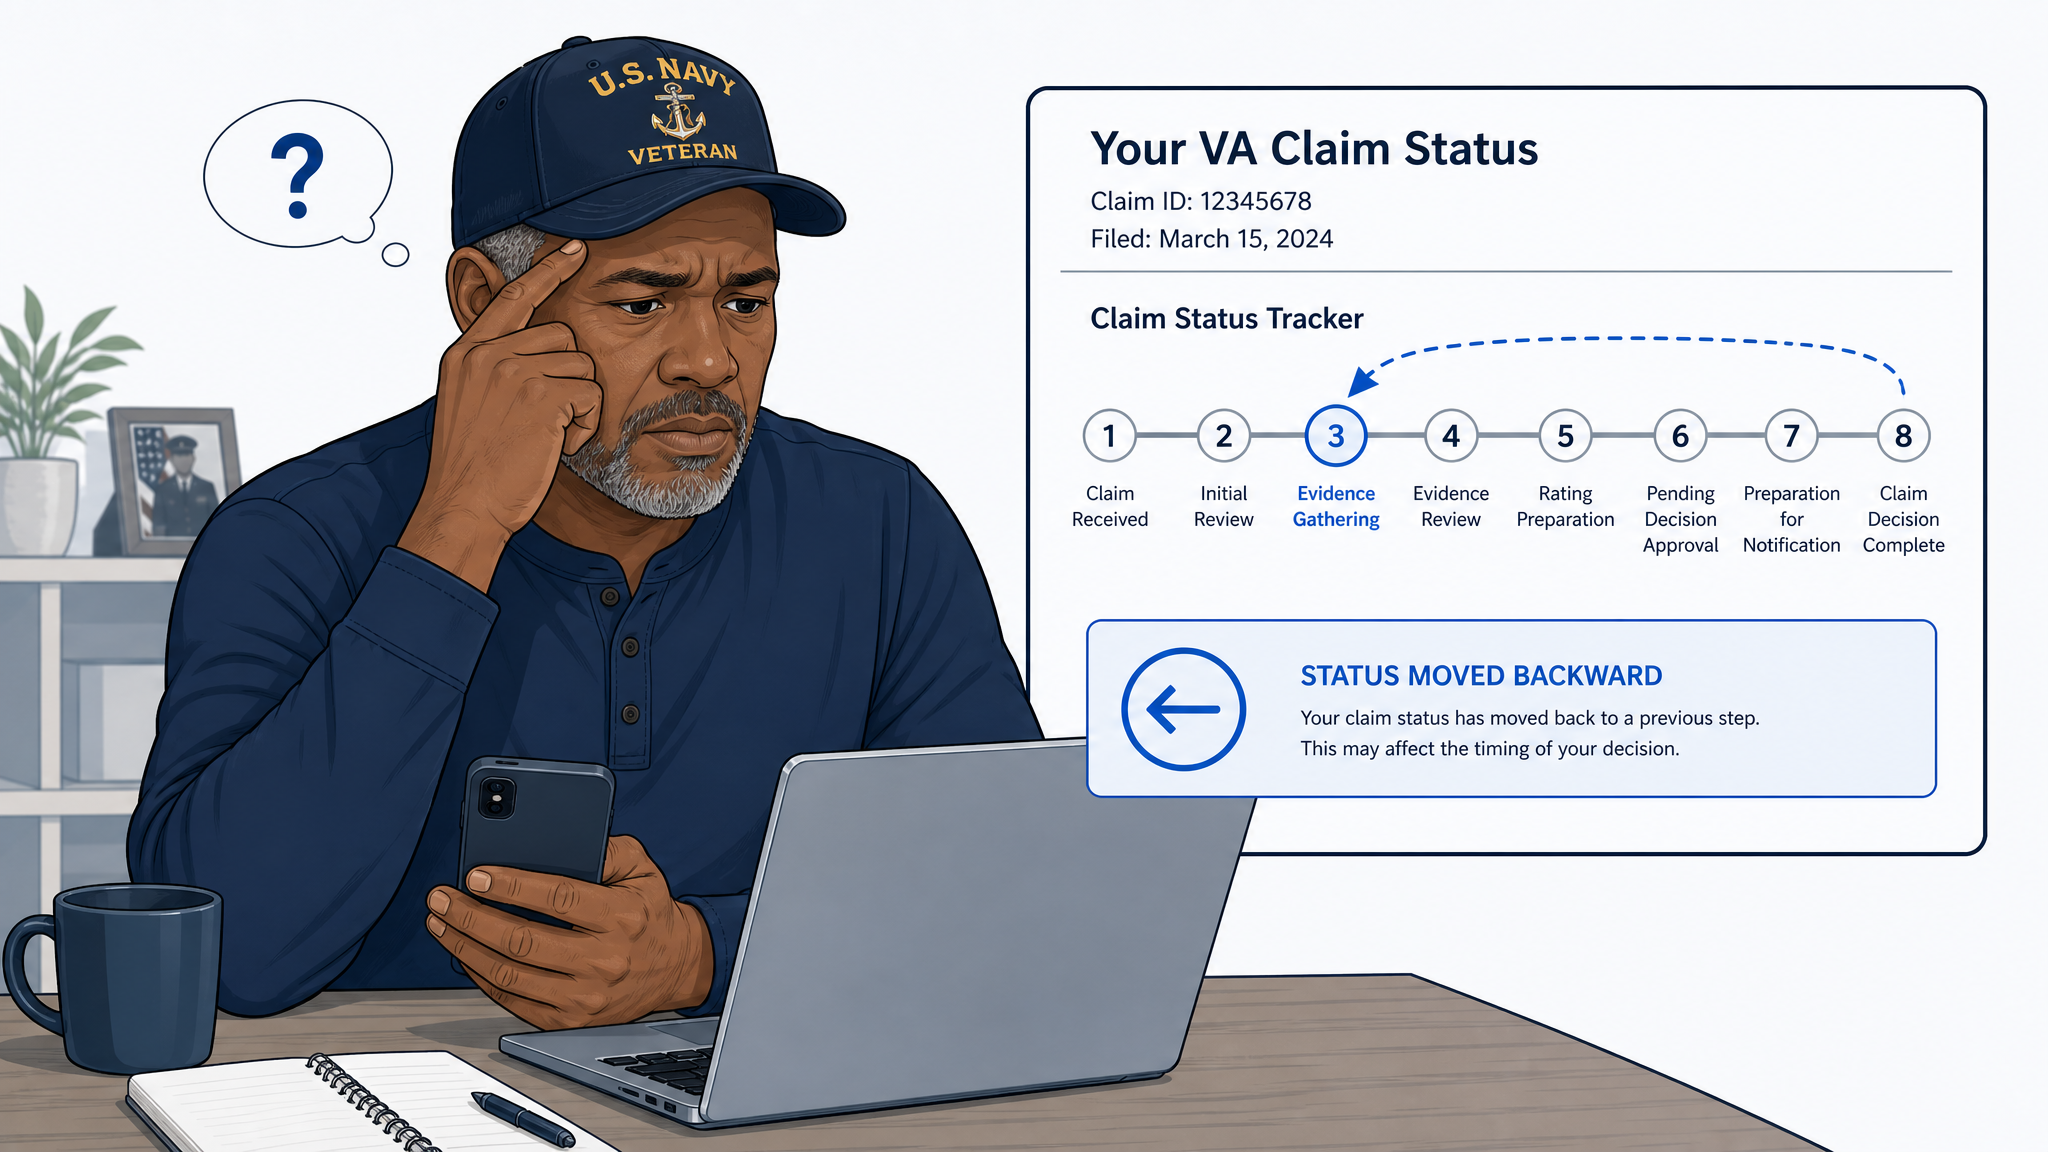
Your status tracker moves backward, and it is usually not bad news
Any time after the exam
The online tracker shows eight steps. Veterans watch it reach step 7 or 8, then find it back at step 3 or 4 a week later. That regression almost always means one thing: the file went back for additional information, most often a returned or clarified exam.
This is the number one thing veterans panic about, and it is misread constantly. The tracker is not a countdown, it is a location marker. When the VA decides it needs one more piece of evidence, a corrected exam, a clarifying medical opinion or an outstanding record, the claim is routed back to the evidence gathering step and the bar redraws itself where the file physically is. It does not mean a denial. It does not mean your case was thrown out or restarted. It does not erase anything already in the file, and it does not change your effective date. What it does mean is that something in the record was not good enough to decide on yet, which is worth knowing, because if the weak link is the exam, this is the window where a corrective statement or a private opinion from your own doctor does the most good.

Evidence gathering closes
Varies
Before anyone rates your claim, the file has to be built. This is the stretch where the Regional Office pulls together everything the decision will rest on: your service treatment records, your VA medical records, any federal records, the C&P exam report, and any private records it has requested on your behalf. The claim sits here until the VA is satisfied the record is complete enough to decide, which is exactly why a status tracker can appear to stall or slide backward at this step. You are not powerless while it sits here. Anything you put into the file yourself lands the day you send it, and every relevant record you add now is one less thing the rater can later say was missing.
A VA request to a private provider is a letter that may or may not be answered, and the VA will wait on it for weeks before moving on, sometimes without ever getting a response. A record you walk in yourself, or upload through your claim, is in the file the day you send it. So do not sit and wait to be asked. If you know a treatment record, an imaging report, a surgical note or a buddy statement exists and it matters, send it now, with a VA Form 21-4138 statement that explains in plain words what the document is and what it shows. This is also the window where a corrective statement or a private medical opinion from your own doctor does the most good, before the rater has locked in a decision, not after. Once the evidence gathering step closes, the file goes to a rating specialist, and your chance to shape the record cheaply and quickly closes with it.

Rating decision and promulgation
Typically several weeks after the last piece of evidence lands
This is the stage where your evidence finally becomes a number. A rating specialist, not the examiner, and not a doctor, takes everything in the file and applies the rating schedule to it: the exam findings, your range-of-motion measurements, your lay statements, your private records and any medical opinions. They assign a diagnostic code to each condition, pull a percentage from the schedule, set your effective date, and either grant, deny or defer each issue. The decision is then reviewed and authorized, promulgation is simply the VA’s word for making it official, and the decision letter and code sheet are generated and mailed. Where an award is made, payment follows the effective date rules, and back pay is calculated to that date.
Read the code sheet, not just the percentage. It names the diagnostic code used, the exact measurements relied on and the effective date assigned, and that is where most mistakes live. This is a human being reading a file under a production quota, and the two things that go wrong most often are a rater using the pre-repetition range-of-motion numbers instead of the worst-case figures §4.59 and §4.40 require, and a claimed condition being decided on a thin record or quietly left out. Check whether painful motion was accounted for, whether your radiculopathy was rated separately under Note (1) or folded into the spine rating, and whether every condition you claimed was actually addressed. A decision you do not read is a decision you cannot challenge, and the deadline to challenge it starts the day the letter is dated, not the day you understand it.

C&P examination is the decision letter
The day it lands in your mailbox
The envelope holds two different documents: the narrative decision letter, and the code sheet. Together they are the single most important piece of paper in your claim, because every deadline, every appeal option and every dollar of back pay is set by what is printed on them, not by what you were told at the exam.
Most veterans read one thing on that letter: the percentage. Then they either celebrate it or get angry at it, and file it in a drawer. That is the mistake. The percentage is the conclusion; the reasons section is the reasoning, and the reasoning is what you attack. It tells you which diagnostic code the rater used, which range-of-motion figures they relied on and which they ignored, whether painful motion under §4.59 was accounted for, whether your neurological findings were rated separately under Note (1) or folded into the spine rating, which conditions were decided, which were deferred, and which were never addressed at all. It also assigns your effective date, which controls back pay. A rating that looks low is very often not a disagreement about how bad your neck is, it is a rater who used the pre-repetition numbers, or missed the radiculopathy, or rated one side and not both. You cannot see any of that from the percentage. Do not go by the percentage alone, and do not decode it by yourself if you are not sure what you are looking at, have someone who reads these for a living read it with you before the clock runs out. You have one year from the date on that letter to file a Higher-Level Review (VA Form 20-0996), a Supplemental Claim (VA Form 20-0995) or a Board appeal, and the deadline runs from the date printed on the letter, not the date you opened it. Bring it to this office and we will go through it line by line, at no cost, and tell you plainly whether it is right.
What normal looks like: 30 to 60 days for a simple claim, longer for a complex one
After your exam you should expect some kind of notification from the VA, a decision, a request for more information, or a notice that another exam has been scheduled. For a straightforward, single-issue claim that often lands within 30 to 60 days. But 30 to 60 days is a rough guide, not a rule, and it is not a ceiling. A claim with several conditions, a toxic-exposure or presumptive question, a returned exam, or missing records routinely takes 90 days or more, and that alone does not mean anything is wrong, the more moving parts your case has, the longer the VA takes to work it. Inside the window that is normal for a case like yours, silence is expected and there is nothing to fix, and a tracker that jumps backward is normal too.
What matters is not a fixed number of days, it is whether the claim is still moving and whether you can get a straight answer about where it is. Once you are well past what is normal for a case like yours and the VA either goes silent or cannot tell you what the claim is waiting on, stop waiting. That is usually where the real trouble hides, an exam that came back twice, a records request that was never answered, a claimed condition that got dropped, or a file sitting in the wrong queue. Call the VA at 800-827-1000, ask specifically what the claim is waiting on and who it is assigned to, and write down the answer. If you cannot get a straight answer, or the answer tells you the exam is the problem, that is the moment to bring it to this office rather than sitting on it for another three months. Problems raised early get fixed inside the claim. Problems discovered in a denial letter get fixed on appeal, and that costs you a year.
Other things that control the clock
Six things decide how long you wait, and none of them are visible from the tracker alone.

The average is a moving number
Check it at the source, not second-hand
The VA publishes an average days-to-complete figure for disability claims that moves month to month; check the current number on the VA’s own claim status page rather than relying on any second-hand figure. In practice, most veterans see a decision somewhere between roughly three and eight months from the date the claim was filed, with the exam usually falling in the middle of that window.
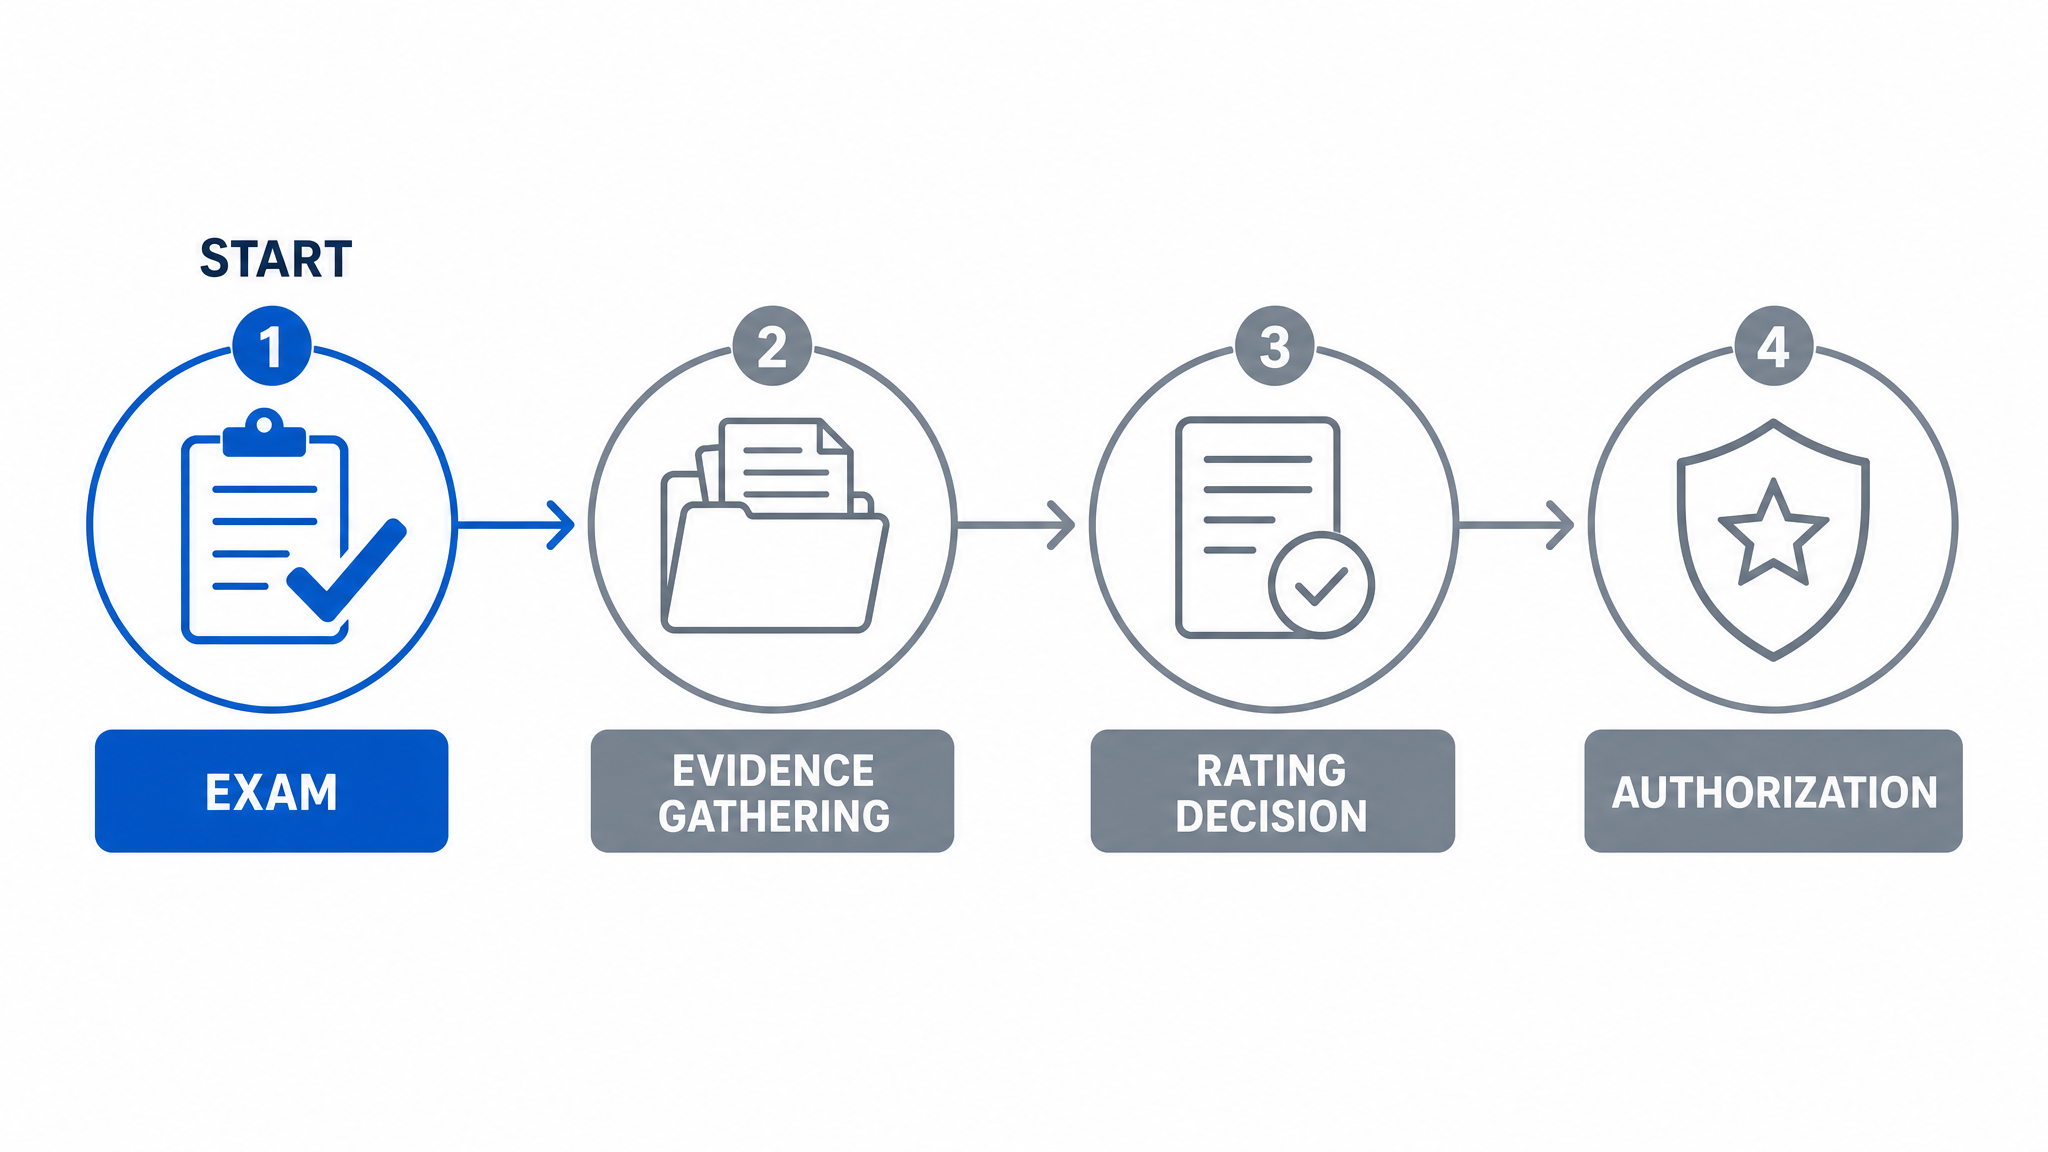
The exam is not the last step
Three stages still sit in front of you
The exam is not the last step. The clock does not start at the exam and it does not stop there either, the claim still has to clear evidence gathering, the rating decision and authorization.
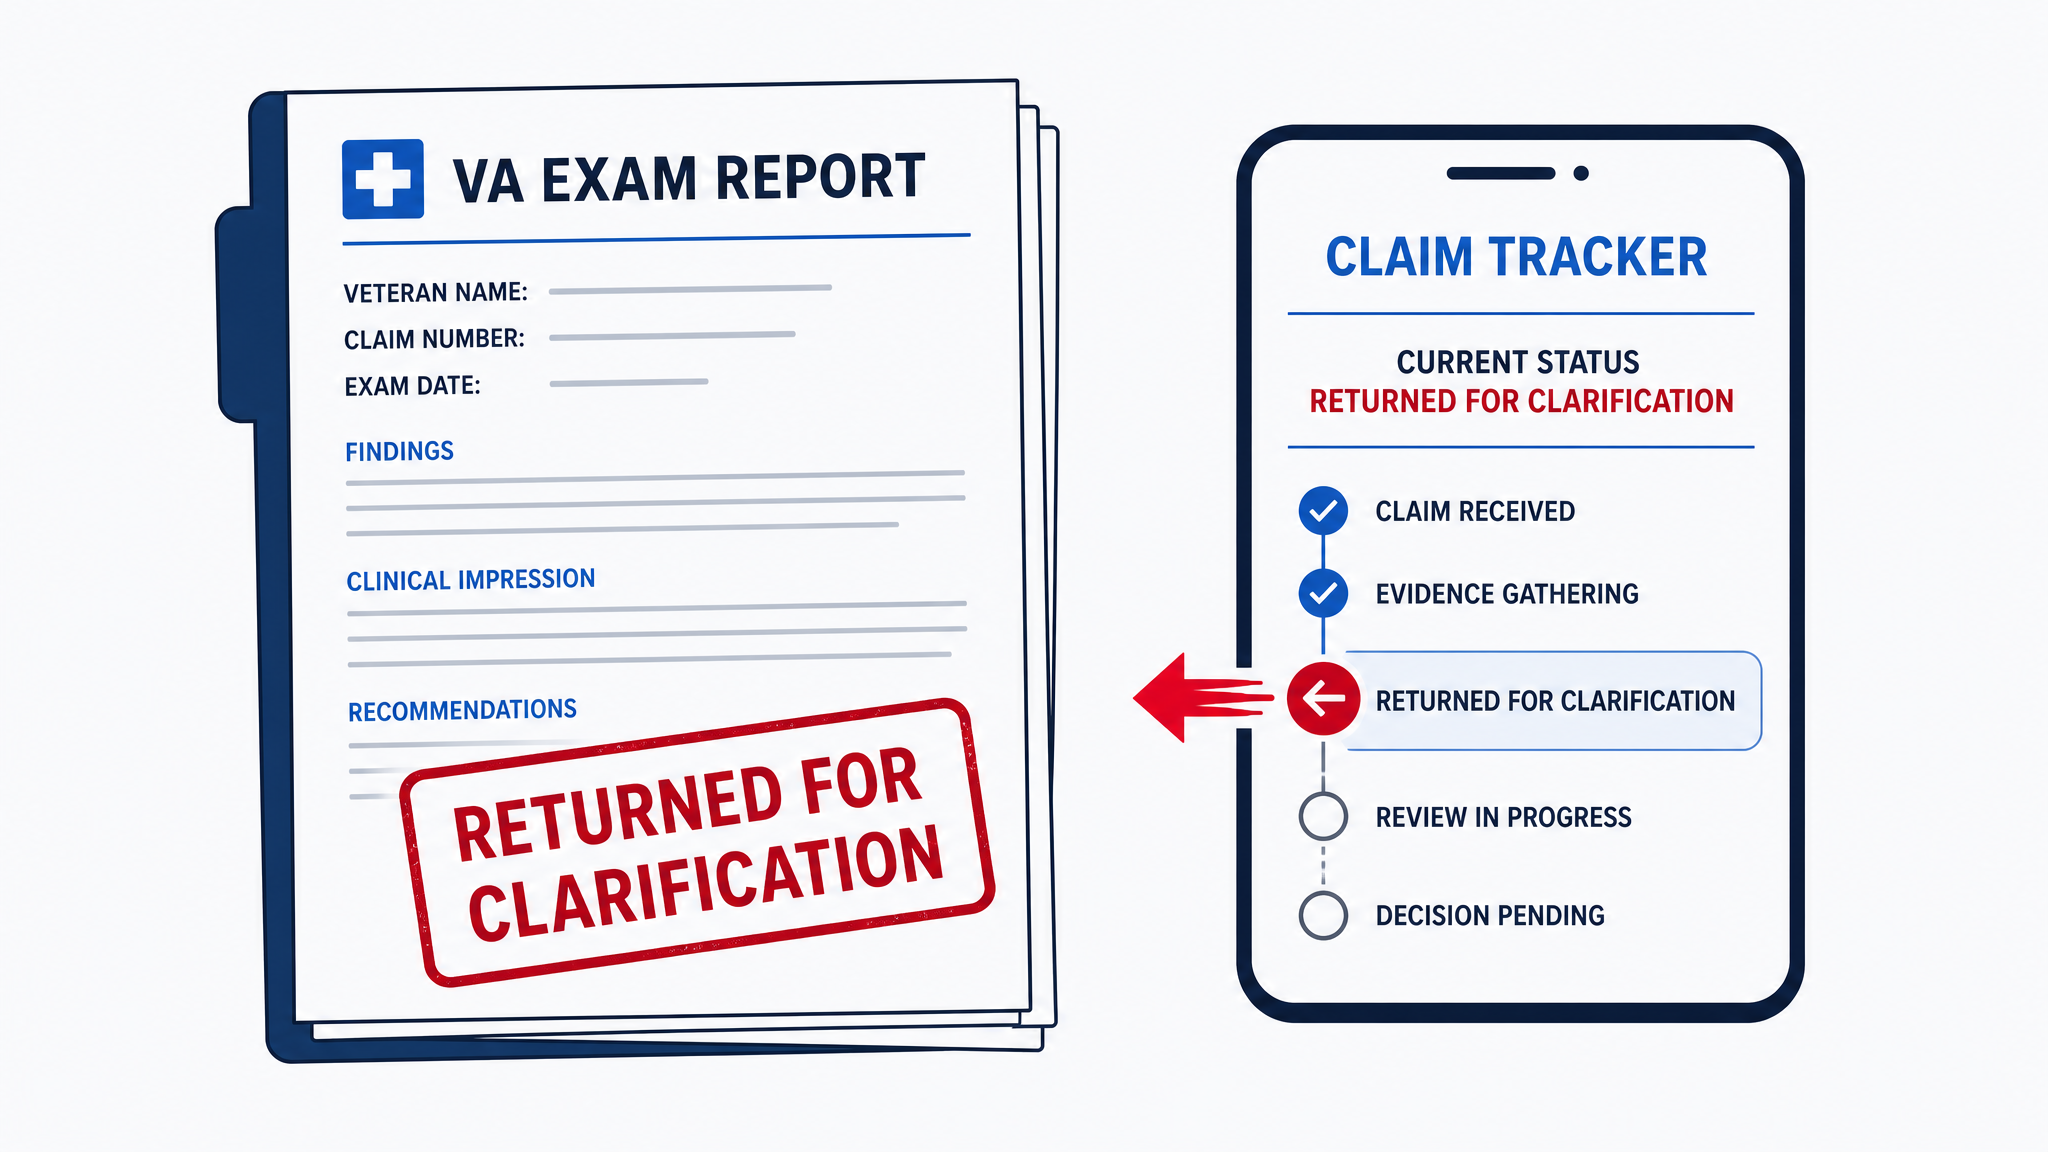
A returned exam is the invisible delay
The reason a tracker slides backward
A returned or clarified exam is the most common invisible delay, and it is why a tracker can slide backward. Expect some contact from the VA within 30 to 60 days of the exam. Past 60 days with nothing at all, call and ask specifically what the claim is waiting on.
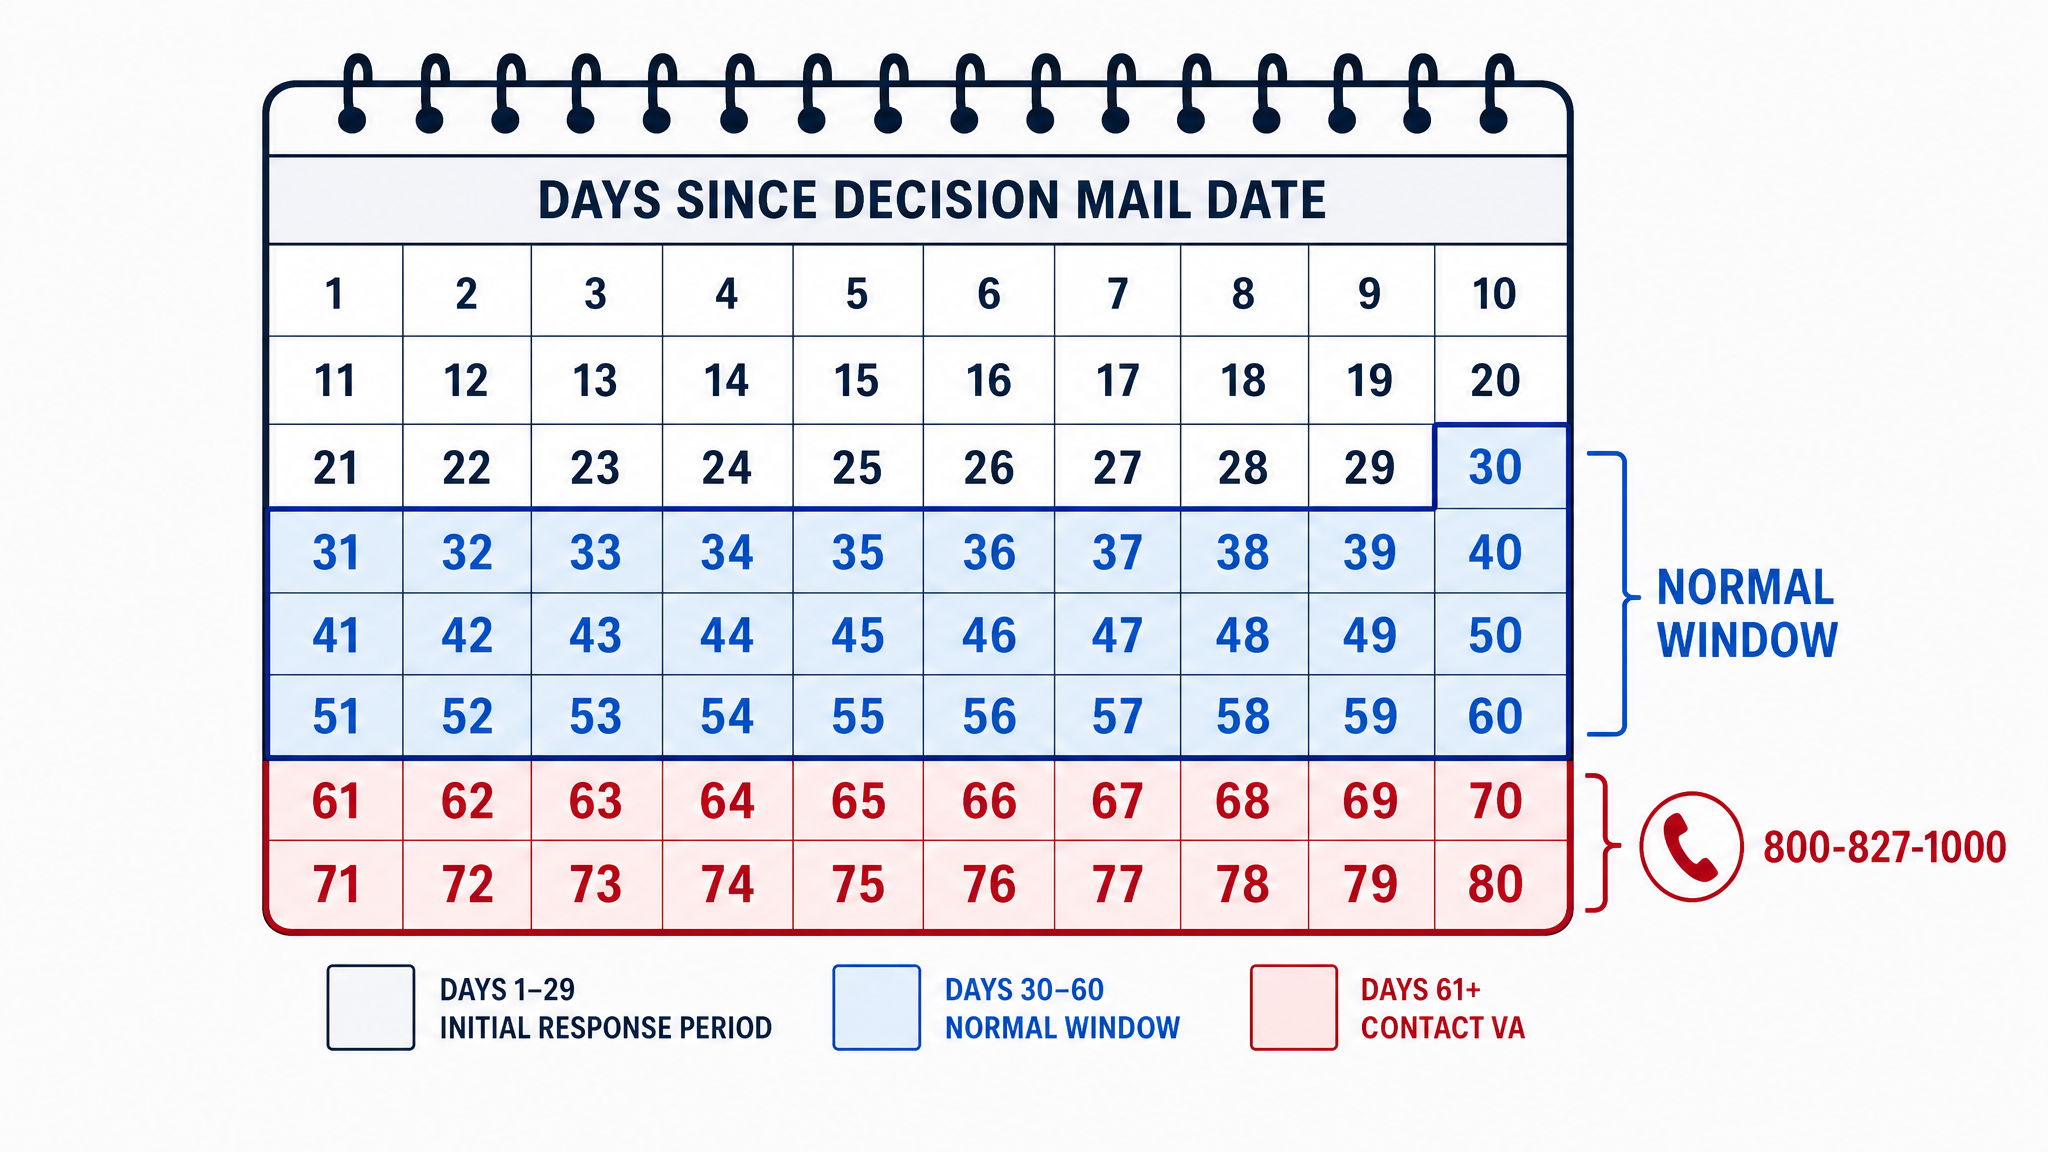
30 to 60 days is a guide, not a deadline
A complex case can take 90 days or more
Thirty to sixty days is a rough average for a simple, single-issue claim, not a hard rule and not a ceiling. A claim with several conditions, a presumptive or toxic-exposure question, a returned exam, or missing records can easily take 90 days or more, and that alone does not mean anything is wrong. Watch whether the claim is still moving, not the calendar. Only when it stalls well past what is normal for a case like yours, and no one can tell you what it is waiting on, should you stop waiting, call 800-827-1000 and ask what the claim is waiting on and who it is assigned to.
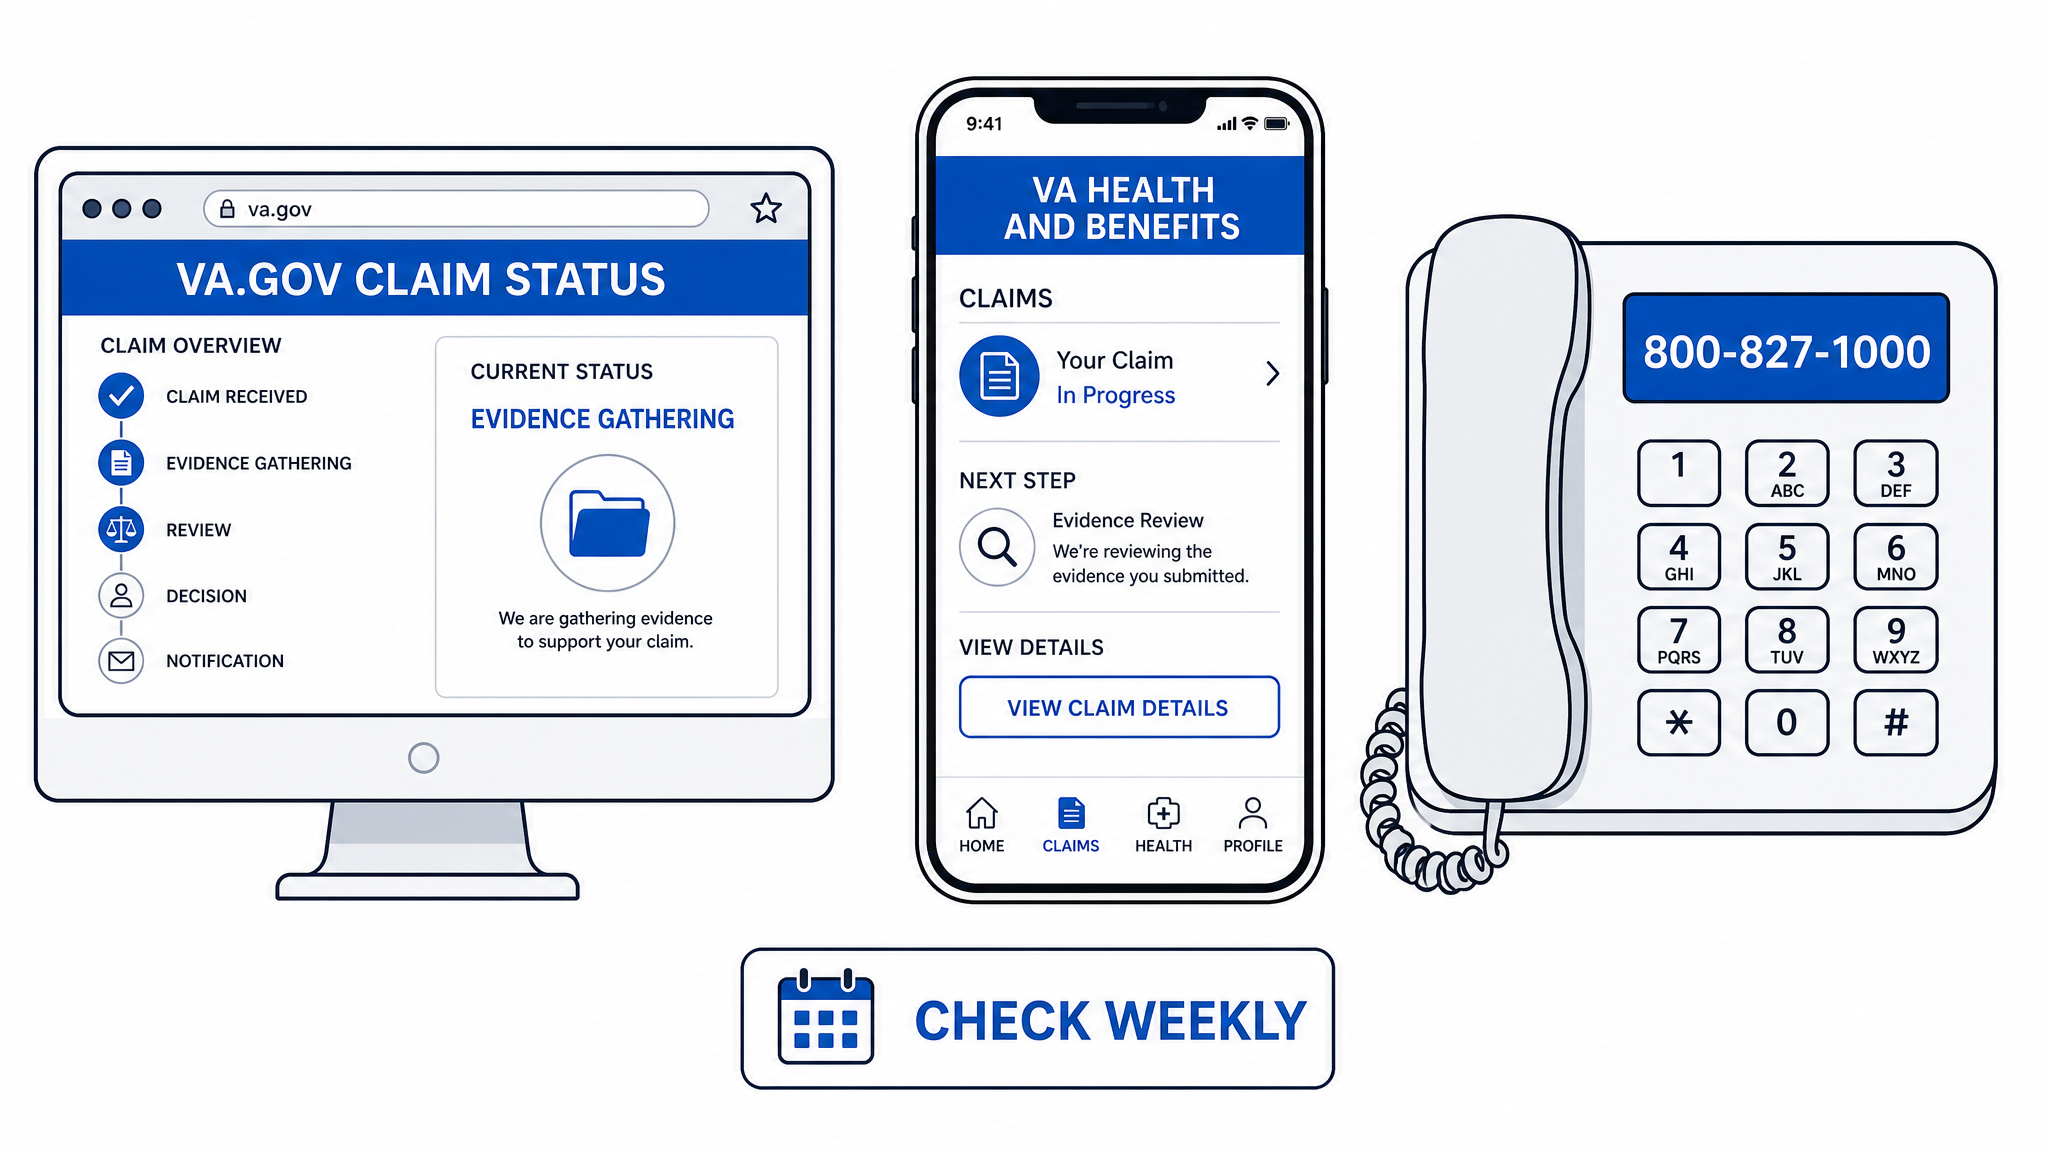
Watch your status yourself, in one of three places
Weekly, not daily
Check your own status in one of three places: your VA.gov claim status page, the VA Health and Benefits mobile app, or by calling 800-827-1000. Check it weekly, not daily. And understand exactly what a status check can tell you: if a decision is posted in your account, it is live; if it is not posted, it is not ready. That is the whole rule. This is not something your representative or your attorney can speed up, we see the same thing you see, at the same time, and calling us to ask does not move it. Calling the VA to ask for an update does not move it either. Watch it yourself, weekly, and the moment a decision posts, bring it to us.
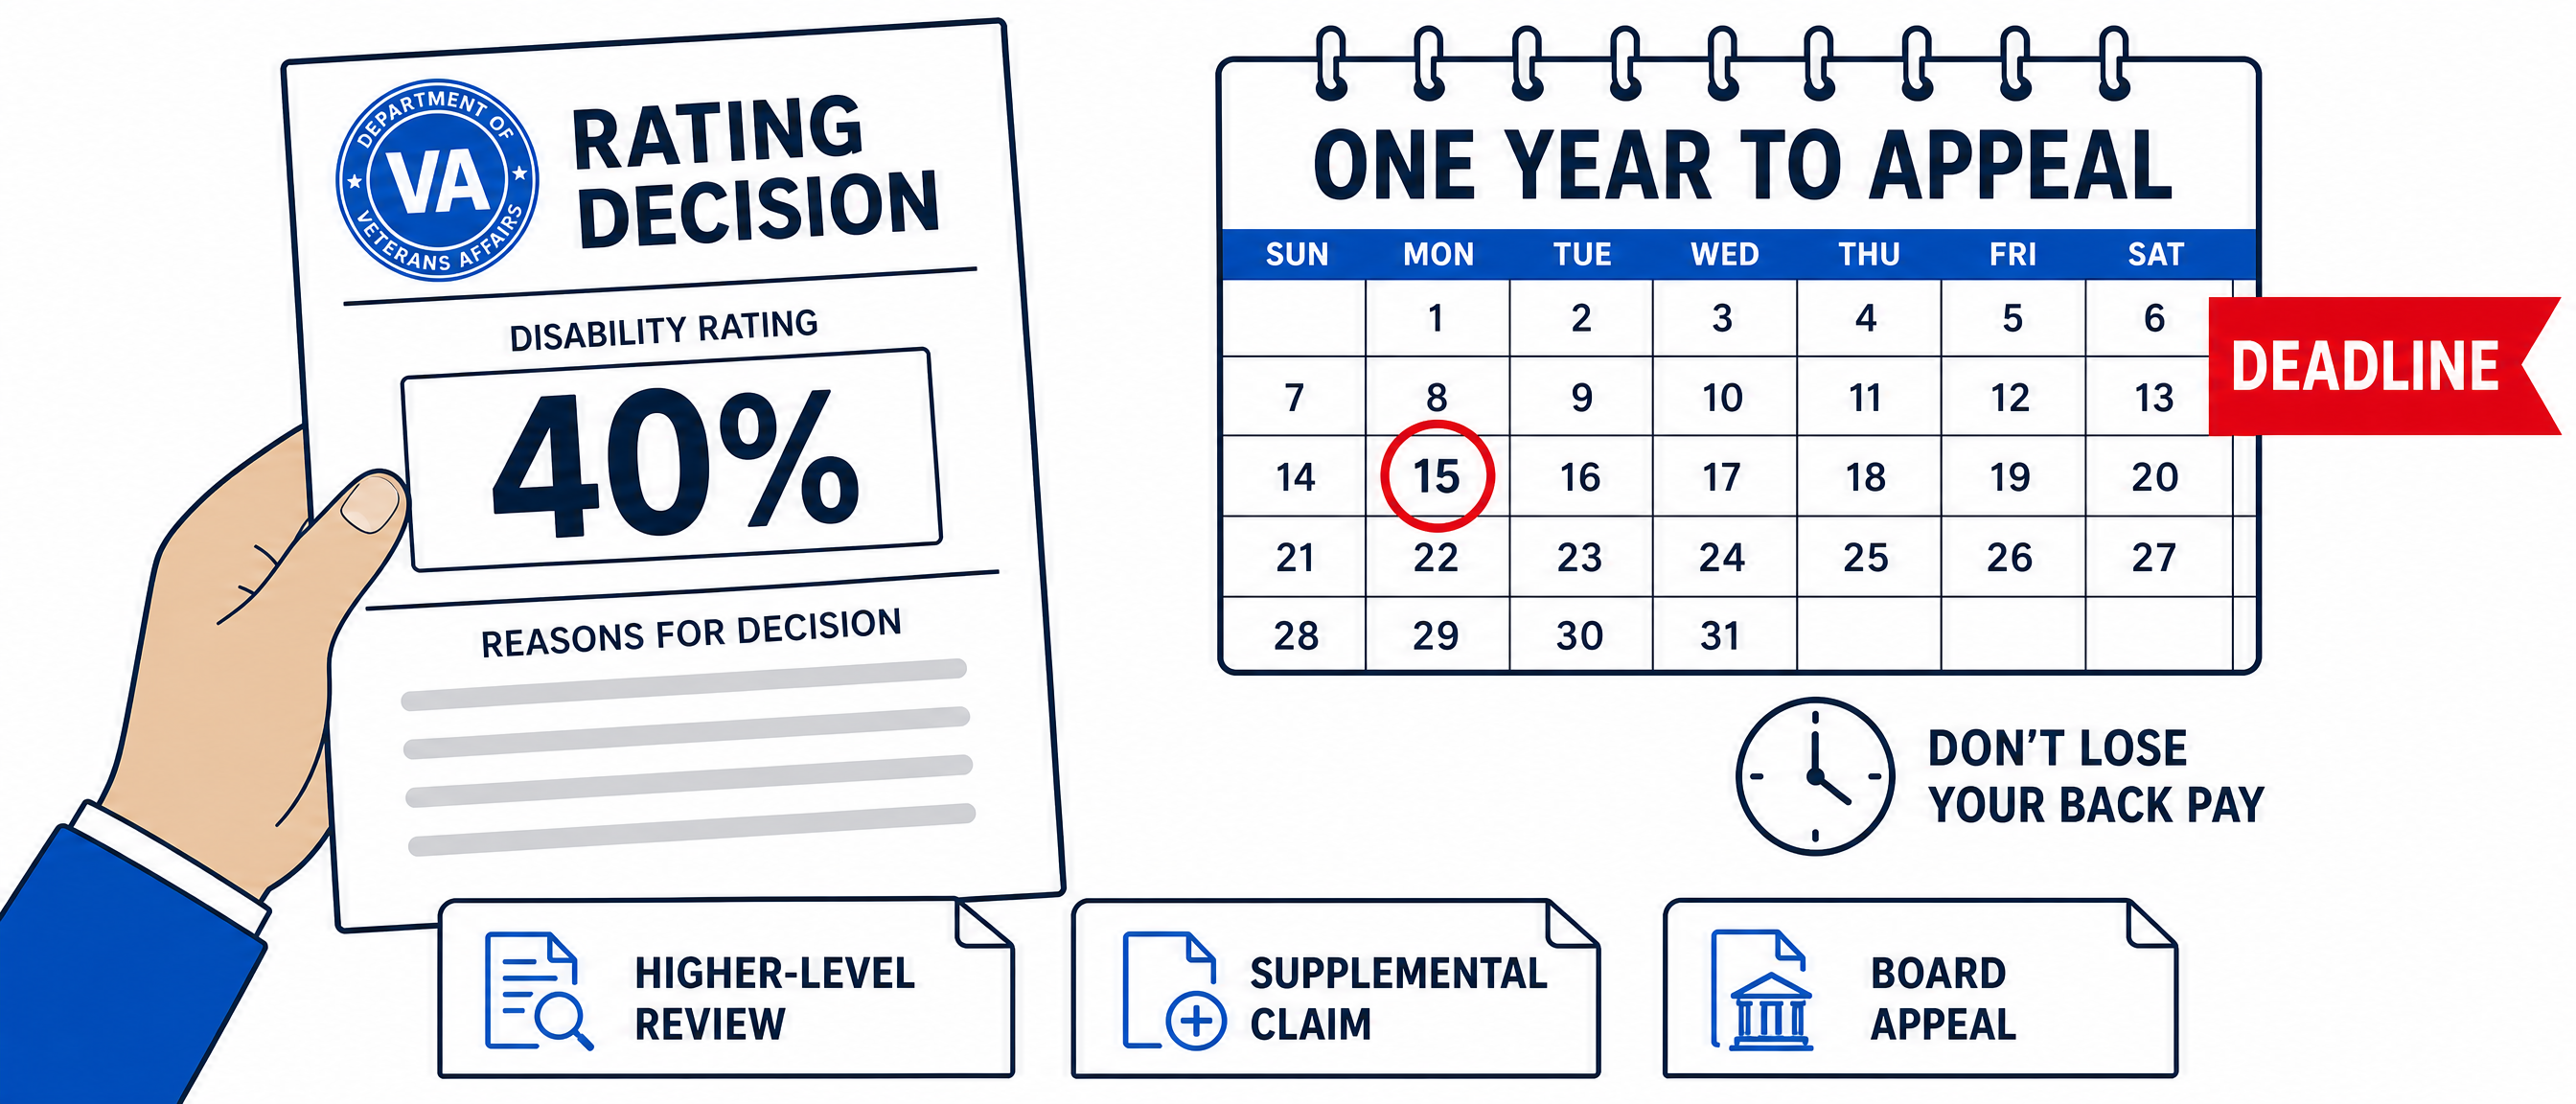
Your decision letter arrives, read it, then start the appeal clock
What to do the day it lands in your mailbox
The decision letter is the finish line of the claim and the starting line of the appeal, and the moment it arrives, a one-year clock starts running. Read it the same day. Find the combined rating, the percentage assigned to each condition, and the effective date, because the effective date controls how far back your back pay reaches. Then request a copy of your C&P exam report so you can see whether the rater used your real range-of-motion numbers or ignored the radiculopathy. If any part of the decision is wrong, a low rating, a denied condition, or a bad effective date, you have three appeal lanes, and you must choose one within one year of the date printed on the letter: a **Higher-Level Review (VA Form 20-0996)**, where a senior reviewer re-decides on the same evidence; a **Supplemental Claim (VA Form 20-0995)**, when you have new and relevant evidence such as a private DBQ or your own range-of-motion exam; or a **Board Appeal (VA Form 10182)** to a Veterans Law Judge. Miss that one-year deadline and the decision becomes final. You can still file again later, but you lose the original effective date, and that lost time is lost back pay you never get back. Bring the letter to this office before the year runs out and we will read it with you, line by line, at no cost.
07Remedy
How to report a bad exam
Where this exam goes wrong
The two biggest traps in an elbow claim are the **incomplete motion exam** and the **shoulder fold-in**. First, examiners routinely measure only flexion and extension and never measure forearm supination and pronation, yet limitation of supination to 30 degrees or less is compensable on its own under DC 5213, so a whole ratable motion gets left off the report. Second, an examiner who reports only the end of your arc, without noting where pain begins or estimating the additional loss during a flare, produces a report that understates your disability and is legally inadequate under §4.40/§4.45 and DeLuca/Mitchell. The third trap is having a genuine elbow condition swept into a single upper-extremity rating with the shoulder, the elbow has its own codes (5205–5213) and is entitled to its own evaluation. If the report skips forearm rotation, skips the flare analysis, or folds your elbow into your shoulder, that is an exam you challenge rather than accept.

Write it down the moment you get to your car
Date, start time, end time, the examiner’s name and credentials, the vendor, every test that was performed, and every test that was not. A contemporaneous note written the same day is evidence. A memory reconstructed four months later is not.

Get the exam report and the questionnaire
Request a copy through VA.gov, through a written request to the Regional Office, or by calling 800-827-1000. You cannot challenge what you have not read. Compare it line by line against what actually happened in the room.

Name the defect specifically, with the citation
Never write "the exam was unfair." Write "no goniometer was used, contrary to 38 CFR §4.46" or "flare-ups were reported and not addressed, contrary to Sharp v. Shulkin" or "repetitive use testing was not performed, contrary to 38 CFR §4.40 and DeLuca." A specific, citable defect is what forces action.

Submit a statement asking for a new examination
VA Form 21-4138, Statement in Support of Claim, filed through VA.gov or mailed to the Evidence Intake Center. State the defect, cite the authority, and request a new or supplemental examination. Do this BEFORE the decision if the claim is still open, it is far easier than undoing a decision afterward.
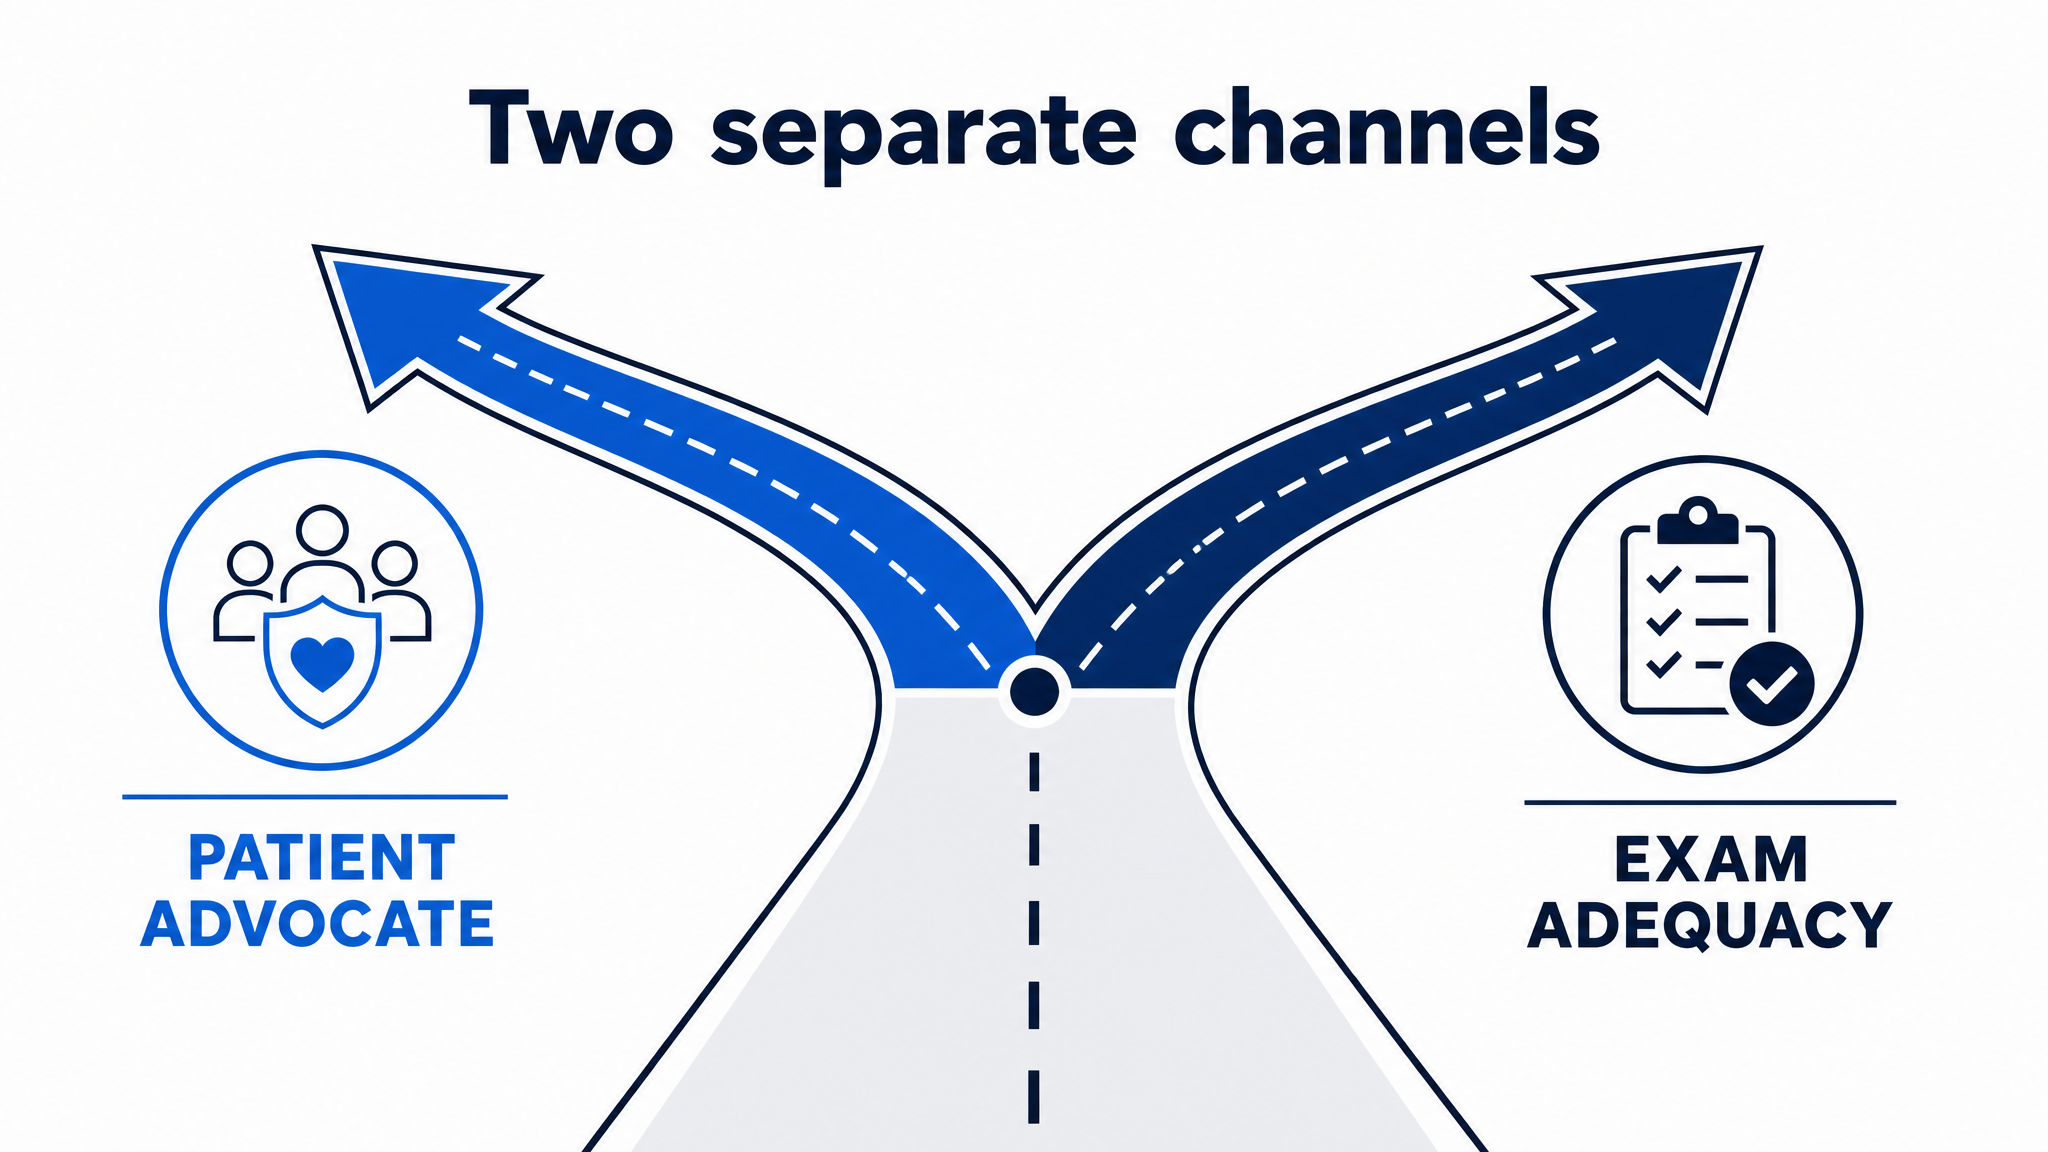
Report examiner conduct separately
If the problem is behavior rather than methodology, you were rushed out, dismissed, never touched, or treated with hostility, file a complaint with the VA facility’s Patient Advocate, or with the vendor directly for a contract exam, and copy the Regional Office. Conduct complaints and adequacy challenges are two different tracks and you can run both.
If a decision has already issued, pick the right lane
A Higher-Level Review (VA Form 20-0996) argues the VA erred on the evidence it had, the right vehicle when the exam was inadequate on its face. A Supplemental Claim (VA Form 20-0995) is the vehicle when you are adding new and relevant evidence, such as your own private range-of-motion examination or a completed DBQ from your treating provider.
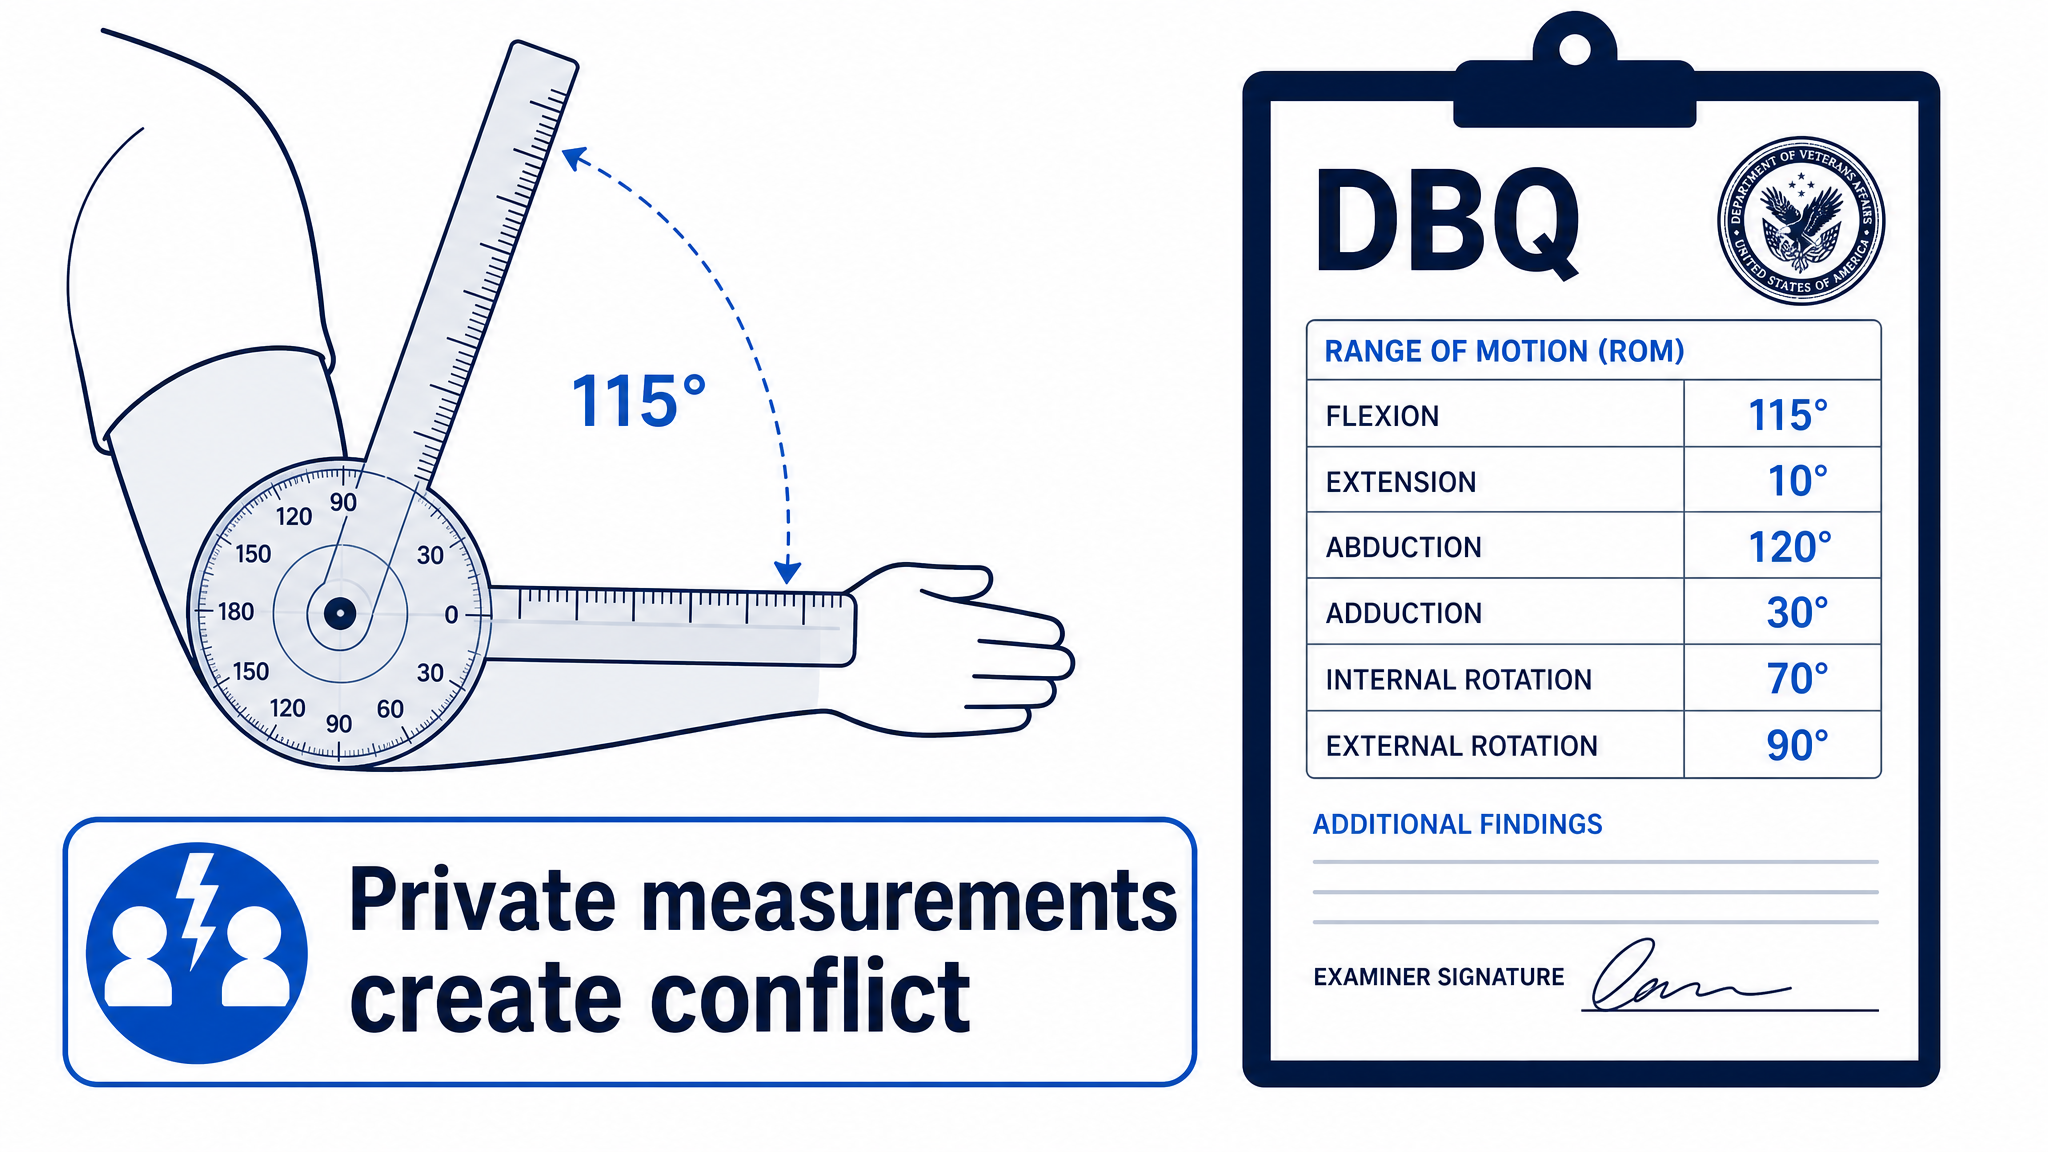
Put your own measurements on the table
A private examination with full goniometric measurements, or a DBQ completed by your own provider, creates a conflict in the evidence that the VA has to resolve, and under 38 CFR §3.102 reasonable doubt is resolved in your favor.
End of clinical section
Elbow & Forearm (DC 5205–5213), DC 5205–5213
The Questions Veterans Actually Ask
Elbow & Forearm (DC 5205–5213) Claims, Frequently Asked Questions
Straight answers to the questions that decide elbow & forearm (dc 5205–5213) claims, the ratings, the separate evaluations, and the exam mistakes that cost veterans money. Read every answer with your own file open. If an answer depends on a record you do not have yet, that is the next thing to request, from your doctor, your unit or the VA itself.
Elbow and forearm conditions are rated under 38 CFR §4.71a, Diagnostic Codes 5205–5213. The single highest scheduler value is 60%, assigned for unfavorable ankylosis of the elbow (DC 5205) on the dominant (major) arm, or for a flail joint of the elbow (DC 5209) on the major arm. Every other code, limitation of flexion, limitation of extension, and impairment of the ulna or radius, pays less, and the dominant-hand rule under §4.69 means the exact same limitation is worth more on your dominant side. Where you land depends on measured motion and documented bone impairment, not on how the joint feels on an average day.
Every condition in Elbow & Forearm Conditions



