

Digestive
Gastrointestinal Disorders (GERD / IBS)
Digestive ratings, medication-induced GERD, and Gulf War presumptions
GERD is often secondary to medications taken for a service-connected condition. IBS may qualify as a Gulf War presumptive medically unexplained chronic multisymptom illness.
Each Condition, Broken Out
Every Condition In This Category Has Its Own Page
These are separate diagnostic codes with separate criteria, separate exams and separate money. Each one below opens a full page: how it is rated, the schedule spelled out, the service-connection arguments, and exactly what happens at that specific C&P exam.
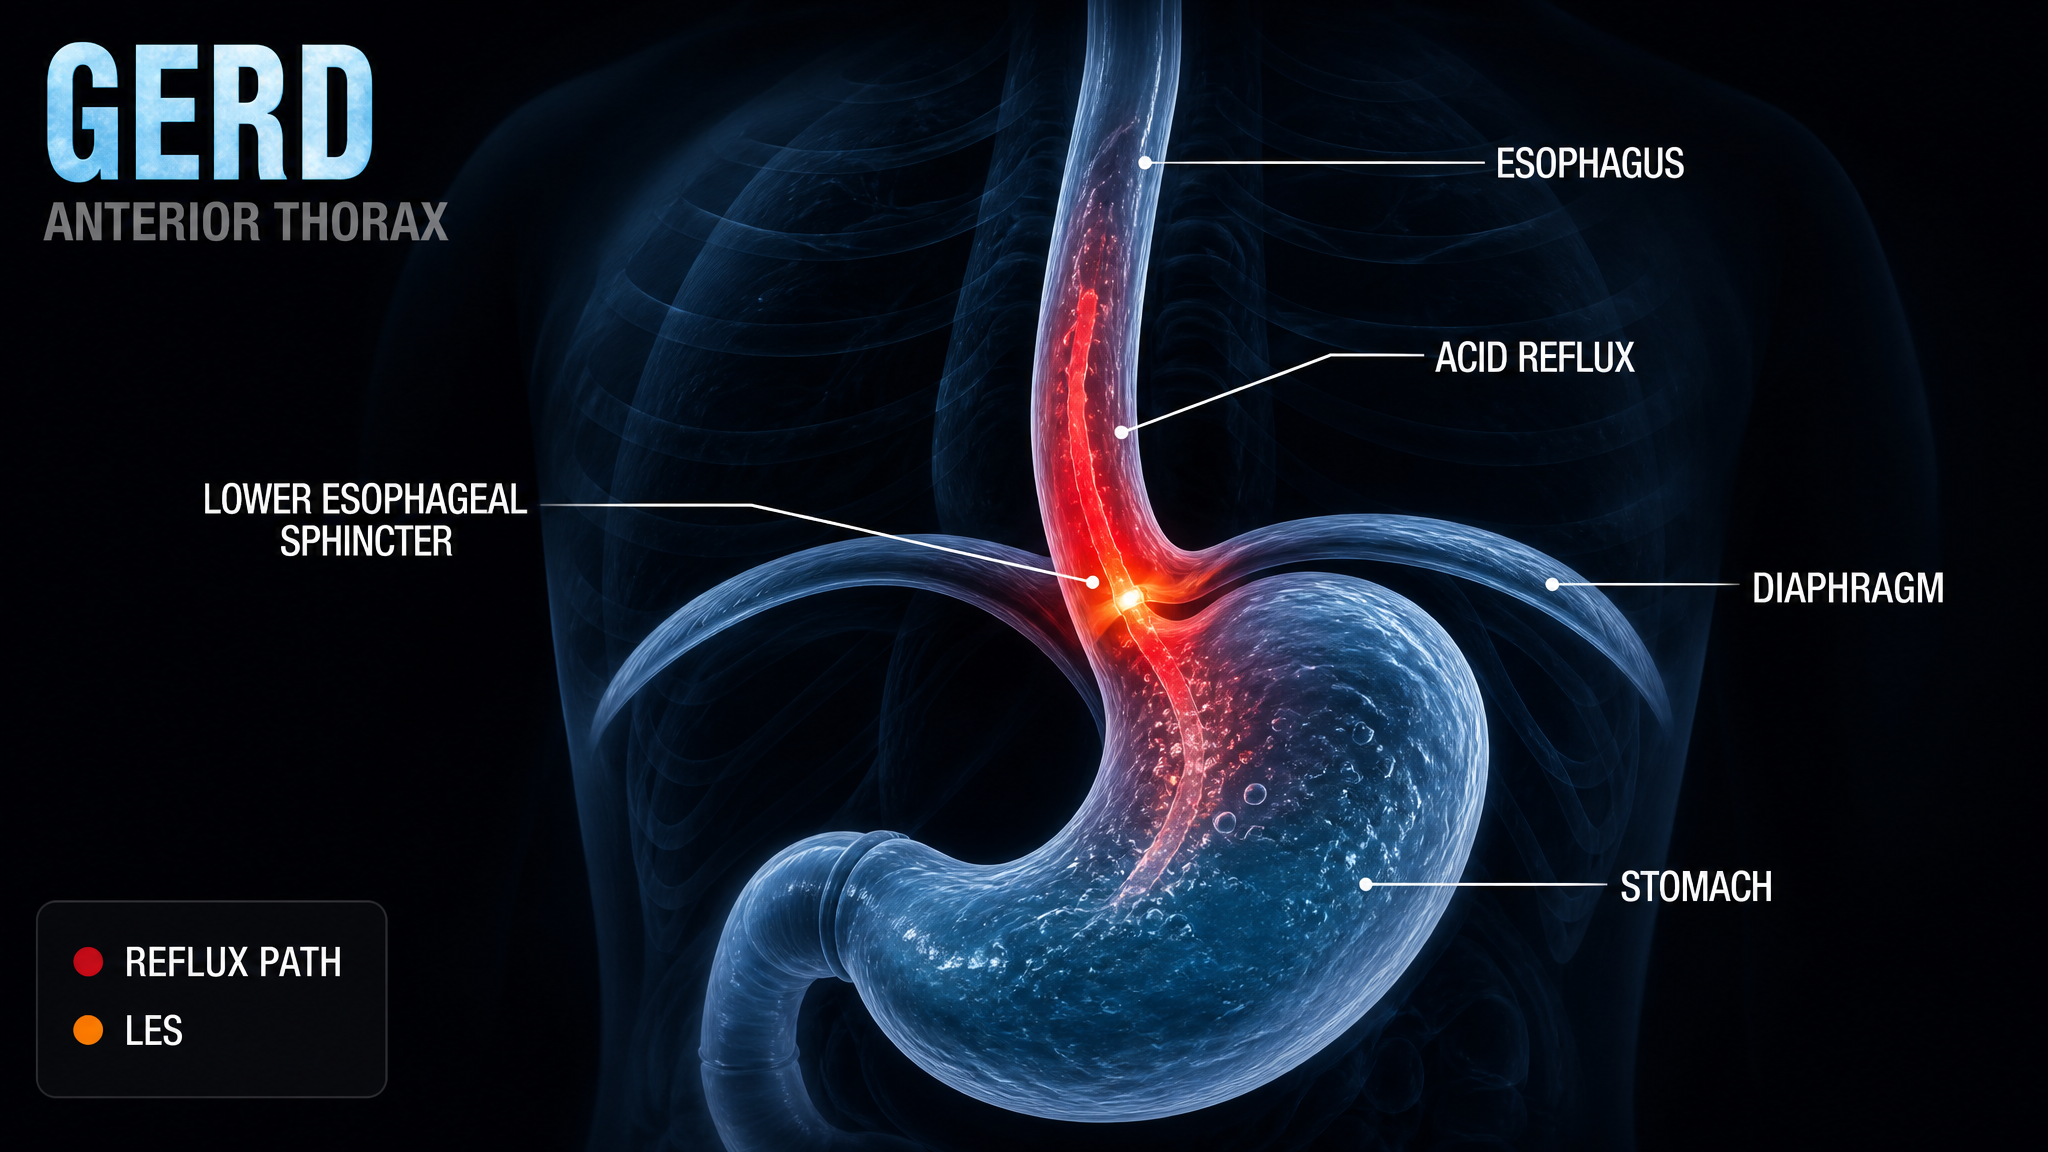
DC 7206
GERD (Gastroesophageal Reflux Disease)
Acid backing up from the stomach into the esophagus, burning, regurgitation and chest pain that reflux medication only partly controls.
Read the full GERD (DC 7206) page
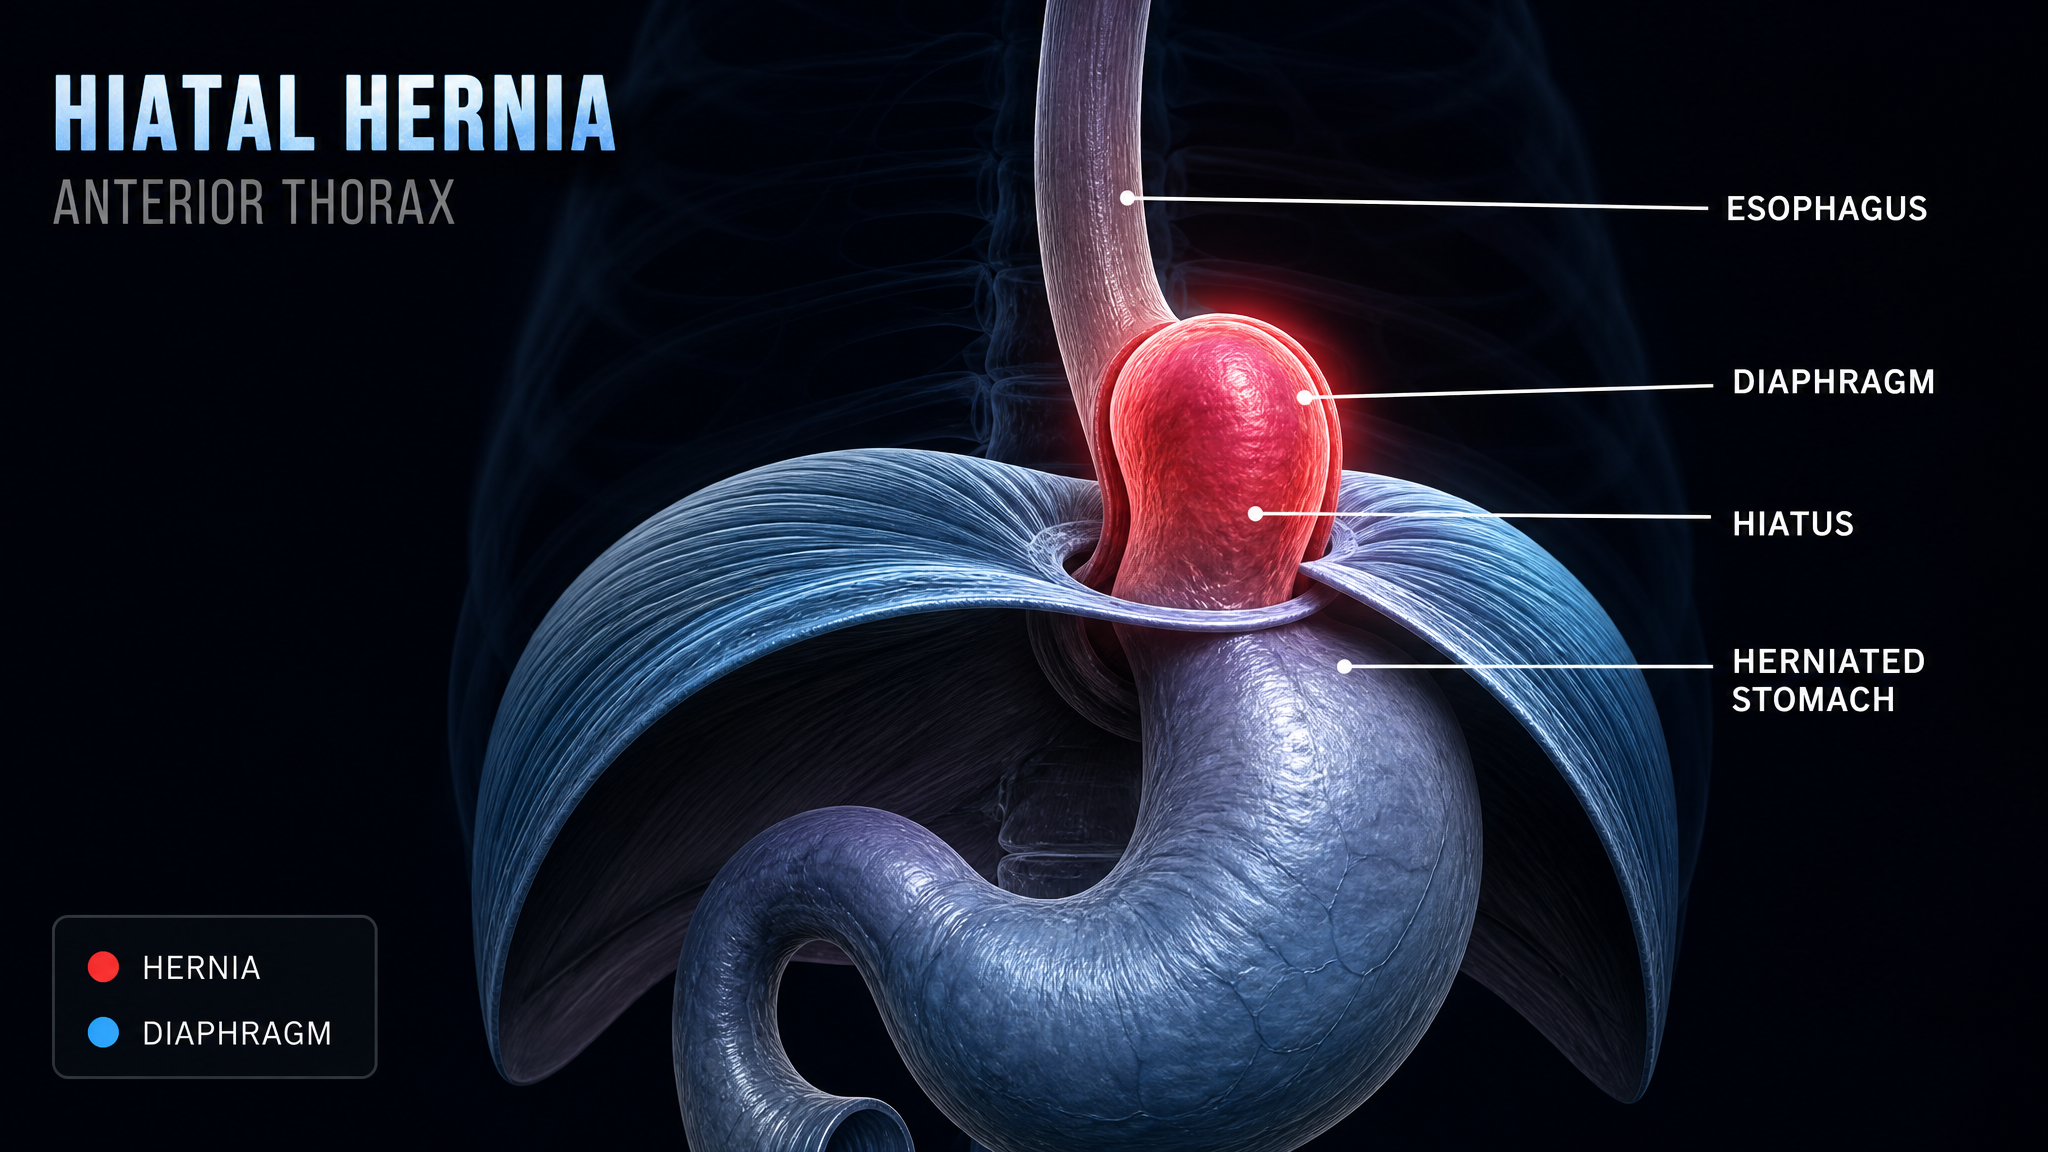
DC 7346
Hiatal Hernia
The upper stomach pushes up through the diaphragm into the chest, weakening the valve that keeps acid down and driving chronic reflux.
Read the full Hiatal Hernia (DC 7346) page
What Gastrointestinal Disorders (GERD / IBS) Really Is
Your gut stopped working the way it used to. Maybe it is acid climbing your throat every night, maybe it is cramping and running to the bathroom before every meeting, maybe it is both. The VA files all of it under the digestive system, and that system is one of the most poorly rated areas in the entire schedule because the criteria talk about symptom frequency and weight loss rather than how much of your day the condition steals.

What it actually means
Your gut stopped working the way it used to. Maybe it is acid climbing your throat every night, maybe it is cramping and running to the bathroom before every meeting, maybe it is both. The VA files all of it under the digestive system, and that system is one of the most poorly rated areas in the entire schedule because the criteria talk about symptom frequency and weight loss rather than how much of your day the condition steals.

What the VA measures
For reflux the VA looks at persistently recurrent epigastric distress, pyrosis, regurgitation, arm or shoulder pain, dysphagia, and whether the whole picture is productive of considerable or severe impairment of health. For irritable bowel the schedule looks at how often you have disturbances of bowel function with abdominal distress and whether it is more or less constant.

Why claims get missed
Veterans describe their worst night and the examiner records their best day. They also fail to connect the gut to the real culprit: the medication. Years of NSAIDs for a service-connected back or knee, or an SSRI for service-connected PTSD, will wreck a stomach lining, and that makes the GERD secondary and compensable.
What in Your Service Causes Gastrointestinal Disorders (GERD / IBS)
Service connection is not a feeling, it is a chain of evidence. These are the pathways the VA already recognises. Find yours, then make sure your file says it out loud.
Deployment food, water, and schedule
Irregular meals, MREs, contaminated water, and eating on a two-hour rotation for months at a time changes gut function. Gulf War and Southwest Asia veterans have a presumptive path for functional gastrointestinal illness under 38 CFR 3.317.
Medication you were told to take
NSAIDs, steroids, antibiotics, and psychiatric medications prescribed for another service-connected condition are a classic secondary route to GERD, gastritis, and ulcer disease.
Untreated stress and hypervigilance
The gut-brain axis is real medicine, not a metaphor. PTSD, anxiety, and chronic pain drive irritable bowel symptoms, and the VA rates the digestive result separately from the mental health condition.
Infection or parasite picked up overseas
A documented episode of dysentery, giardia, or campylobacter in service can leave post-infectious irritable bowel behind for decades.
GERD Is Frequently a Medication Injury
Gastroesophageal reflux disease is commonly caused or aggravated by long-term use of NSAIDs and other medications prescribed for a service-connected orthopedic or psychiatric condition. That makes it a classic secondary claim under §3.310, but only if someone connects the medication to the reflux.

IBS and the Gulf War Path
Irritable bowel syndrome is one of the functional gastrointestinal disorders that can be presumptively connected under §3.317 for veterans who served in the Southwest Asia theater. It falls under medically unexplained chronic multisymptom illness, meaning you do not need a nexus, only qualifying service and the qualifying symptoms.
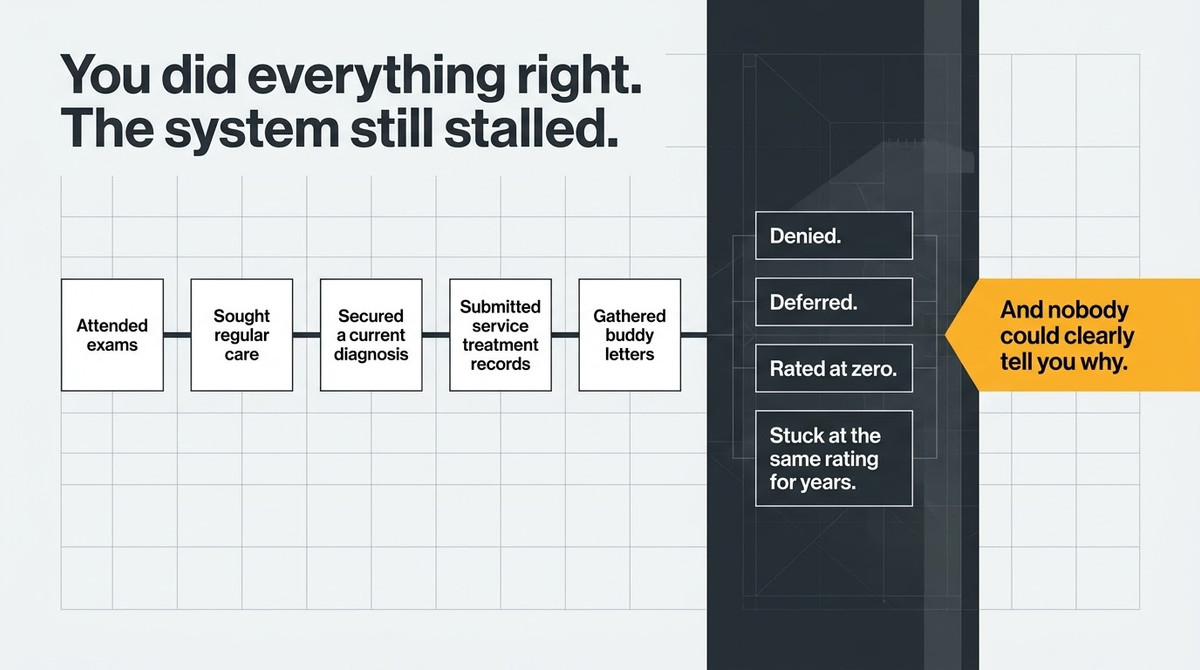
Documenting Digestive Claims
Digestive claims are often won as secondary under §3.310, because the pain pills and psychiatric medications you take for other service-connected conditions can tear up your stomach. That link has to be written down by a doctor. Keep your pharmacy history, your endoscopy or treatment records, and a symptom log with dates. You are the only one who sees your bad days, so record them.

Medication history tying NSAIDs or psychiatric meds to GERD

Endoscopy or treatment records

Symptom frequency and severity logs

Qualifying Gulf War service for the presumptive route
Establishing Service Connection
To establish service connection for a gastrointestinal condition, veterans must meet three criteria. First, there must be a current diagnosis. Second, there must be evidence of an in-service onset, illness, or exposure that could have caused or aggravated it. Third, a nexus, a medical link, must connect the in-service event to the current condition.

Current diagnosis of the gastrointestinal condition

In-service onset, illness, or qualifying exposure

Medical nexus linking the condition to service ("at least as likely as not")

Records of symptom frequency, severity, and treatment

Endoscopy, imaging, or lab results where available
Why Work With an Accredited Advocate
Veterans should seek the assistance of an Accredited VA Disability Advocate because we guide you through the complex claims process and ensure all necessary evidence is gathered and presented effectively. Our advocates are trained to identify and link service-related conditions, increasing the likelihood of a successful claim. We also provide personalized representation, helping veterans navigate appeals and secure the benefits they deserve. As a VA-Accredited Claims Agent, our fees are regulated under 38 CFR §14.636, and there are no fees unless we win your appeal.

The Rating Schedule, Spelled Out
Digestive conditions are rated under 38 CFR §4.114. GERD is rated by analogy to hiatal hernia (Diagnostic Code 7346); irritable bowel syndrome falls under Diagnostic Code 7319; and peptic ulcer disease under Diagnostic Code 7305. Under §4.113 and §4.114, coexisting abdominal conditions generally cannot be combined, the VA assigns a single predominant rating.
Two or more of the symptoms required for the 30% rating, but of less severity.
Persistently recurrent epigastric distress with dysphagia, pyrosis (heartburn) and regurgitation, accompanied by substernal or arm or shoulder pain, productive of considerable impairment of health.
Symptoms of pain, vomiting, material weight loss and hematemesis or melena with moderate anemia; or other symptom combinations productive of severe impairment of health.
Mild; disturbances of bowel function with occasional episodes of abdominal distress.
Moderate; frequent episodes of bowel disturbance with abdominal distress.
Severe; diarrhea, or alternating diarrhea and constipation, with more or less constant abdominal distress.
Mild; with recurring symptoms once or twice yearly.
Moderate; recurring episodes of severe symptoms two or three times a year averaging ten days in duration, or with continuous moderate manifestations.
Moderately severe; less than severe but with impairment of health manifested by anemia and weight loss, or recurrent incapacitating episodes averaging ten days or more at least four times a year.
Severe; pain only partially relieved by standard treatment, periodic vomiting, recurrent hematemesis or melena, with anemia and weight loss productive of definite impairment of health.
Key Points to Remember
These are the rules the rating board applies to this condition, stripped down to what you can act on. Read each one and ask a single question: does my file prove it? If the answer is no, that is your homework, not the VA's. The VA has a duty to assist under 38 CFR 3.159, but it has no duty to build your argument for you.

Rated under 38 CFR §4.114, GERD by analogy to hiatal hernia (DC 7346), IBS under DC 7319

The rating turns on symptom frequency and severity, not just the diagnosis

Only one predominant digestive condition is generally rated when symptoms overlap

Document persistent symptoms, treatment, and any weight loss or anemia
What to Expect at Your Gastrointestinal C&P Examination
The digestive section of the schedule was rewritten, and GERD is now rated under Diagnostic Code 7206 on the presence of specified symptoms and on documented findings such as esophageal stricture or recurrent aspiration, not on the old catch-all hiatal hernia code. Irritable bowel syndrome under Diagnostic Code 7319 is rated on the frequency of abdominal distress episodes. Either way, the exam runs on frequency counts and on endoscopy reports.

A symptom frequency history in numbers: episodes per week and per month, and how many days per month you are symptomatic.

For reflux, documentation of pyrosis, regurgitation, substernal or arm and shoulder pain, dysphagia, and any recurrent aspiration or sleep disturbance from nocturnal reflux.

Endoscopy, barium swallow or manometry results, and specifically whether esophageal stricture, erosive esophagitis or Barrett esophagus is documented.

For irritable bowel syndrome, the frequency of abdominal distress episodes and the pattern of diarrhea, constipation or alternation between them.

Weight history and documentation of any malnutrition, anemia or vitamin deficiency.
Complete medication history including proton pump inhibitors and whether symptoms persist despite them.

A nexus opinion where the condition is claimed secondary to PTSD medication, NSAIDs taken for a service-connected musculoskeletal condition, or burn pit exposure.
What Happens Once the C&P Exam Is Complete
The examiner compiles a detailed report, your medical history, physical findings, and diagnostic results, and assesses the severity, symptoms, and impact of your condition. That report is sent to the VA Regional Office handling your claim and becomes part of your official file, reviewed alongside your other evidence.
The VA may send the report back for corrections, clarification, or a second opinion if it finds it incomplete or unclear. This can delay your claim, because the VA requires thorough and accurate information to decide. Your claim only moves to the decision phase once the VA is satisfied with the evidence, which is exactly why the quality of the file we build for you matters so much. Once decided, your effective date controls how far back your back pay reaches, and any denial can be challenged through a Supplemental Claim, Higher-Level Review, or Board appeal.

The Advocate’s Take
If a service-connected condition put you on daily NSAIDs and now your stomach is wrecked, that is a secondary claim the VA should have raised for you, and didn’t.
Every Level the VA Can Assign You
These percentages come straight out of the rating schedule that governs gastrointestinal disorders (gerd / ibs), Diagnostic Code 7346. Read them slowly. If your current rating does not match what your records actually show, that gap is exactly what an appeal exists to correct.
10%
Two or more of the symptoms required for the 30% rating, but of less severity.
30%
Persistently recurrent epigastric distress with dysphagia, pyrosis (heartburn) and regurgitation, accompanied by substernal or arm or shoulder pain, productive of considerable impairment o…
60%
Symptoms of pain, vomiting, material weight loss and hematemesis or melena with moderate anemia;
Secondary Claims, Both Directions
Under 38 CFR §3.310, a condition caused or made worse by an already service-connected condition is itself service connected. That runs in both directions, and it is the single largest pool of unclaimed compensation in the system.
What can cause gastrointestinal disorders (gerd / ibs)
If one of these is already service connected, this condition can be claimed as secondary to it.
PTSD, anxiety, or depression
Both the condition itself and the medication used to treat it disturb bowel and stomach function.
Musculoskeletal pain conditions
Years of prescribed NSAIDs erode the stomach lining and produce reflux, gastritis, and ulcers.
Sleep apnea
Nighttime airway collapse pulls stomach contents upward and worsens nocturnal reflux.
What gastrointestinal disorders (gerd / ibs) can cause
If this condition is already service connected, each of these is a separate claim you may be owed.
Dental erosion
Chronic acid exposure destroys enamel, and dental damage caused by a service-connected condition is claimable.
Sleep impairment
Nightly reflux fragments sleep and feeds an insomnia or mental health claim.
Anemia and malnutrition
Chronic bleeding or malabsorption produces measurable lab findings that raise your rating.
Esophageal stricture or Barrett esophagus
Long-standing reflux progresses, and the complication is separately compensable.
A secondary claim still needs two things: a current diagnosis of the secondary condition, and a medical opinion saying it is at least as likely as not caused or aggravated by the service-connected condition. You do not have to prove it happened in service.
Building a Gastrointestinal Disorders (GERD / IBS) Claim That Wins
Every claim stands on three legs. Knock one out and the claim falls over, no matter how bad your symptoms are. Before you file, look at your file and find all three.
 01
A current diagnosis
A doctor has to say you have it, now, in writing. Not "reports symptoms of", a diagnosis. Without this leg, nothing else in the file matters.
 02
A link to your service
An event, an injury, an exposure, or an already service-connected condition. Service records, unit records, buddy statements, and your own account all count as evidence.
 03
A nexus that ties the two together
A medical opinion stating it is at least as likely as not that your service caused or aggravated the condition. That phrase is a legal standard: 50 percent or better. It is the leg most denials break.
Document the problem before you file
• Keep a dated symptom log for at least 30 days. Frequency, severity, and what it stopped you from doing.
• Get statements from people who see it, a spouse, a coworker, a battle buddy. Lay evidence is legal evidence.
• Pull your private treatment records. The VA only has to help; it does not have to go find everything.
• Write down what you have stopped doing. Lost work, lost sleep, lost activities. That is what impairment looks like on paper.
Your Rights in This Process
Most veterans walk into this system without knowing the rules the VA itself has to follow. That is how claims get denied for missing evidence the VA was supposed to help you find, and how exams get done by the wrong clinician. These six rights are written into federal regulation. Know them before you file, and make the VA honor every one of them when it decides your claim.

It costs nothing to file
Filing a VA claim is free. Accredited representatives may only charge for work on an appeal after an initial decision, and those fees are capped by 38 CFR §14.636.

The VA has a Duty to Assist you
Under 38 CFR §3.159 the VA must help you get the evidence it needs, and it must tell you what is missing before it denies you for missing it.

You can ask for a different examiner
You may request a trauma-informed clinician, or a clinician of a specific gender, for a C&P examination. Ask before the exam is scheduled.
You can claim every condition you have
There is no limit and no penalty. Primary conditions, secondary conditions, and conditions made worse by service all get filed.

You can appeal and be re-evaluated
A denial is not the end. You may submit new evidence, request a higher-level review, appeal to the Board, and ask for re-evaluation when your condition worsens.

You must be considered for TDIU
If your service-connected conditions keep you from holding substantially gainful employment, you may be paid at the 100 percent rate without a 100 percent rating.
Questions Veterans Ask About Gastrointestinal Disorders (GERD / IBS) Claims
Why did the VA rate my GERD at 10 percent when I have symptoms every single day?
Because the examiner recorded symptoms without recording impairment of health. The 30 percent level requires the symptom cluster to be productive of considerable impairment of health. Bring documented weight change, sleep loss, missed work, and dietary restriction so the record shows the impairment and not just the heartburn.
Can I get both GERD and IBS rated?
Often yes, but the VA will try to pyramid them under one digestive code. The way through is to show distinct symptomatology and distinct anatomy: upper tract acid disease versus lower tract bowel dysfunction. Separate diagnoses from separate specialists help enormously.
My stomach problems started after I began taking pain medication for my back. Is that claimable?
Yes. That is a textbook secondary service connection claim. You need the diagnosis, the documented medication history tied to your service-connected condition, and a medical opinion that the medication at least as likely as not caused or aggravated the gastrointestinal condition.
When You Are Ready to File
Talk to an accredited representative before you file. It costs nothing to ask, and the order you file in changes what the VA is allowed to award you. Albert L. Thombs Jr. is VA-Accredited Claims Agent #45147.
The application itself
This is the form that opens a disability compensation claim. List every condition you are claiming, and name the secondary conditions explicitly.
Release for private records
Authorises the VA to request records from your private doctors. Without it, treatment outside the VA may never reach your file.
Lay or buddy statement
The official form for your own statement and for statements from people who witnessed the event or the change in you.
What This Rating Is Worth (2026)
| 10% | $180.42/mo |
| 20% | $356.66/mo |
| 30% | $552.47/mo |
| 40% | $795.84/mo |
| 50% | $1,132.90/mo |
| 60% | $1,435.02/mo |
| 70% | $1,808.45/mo |
| 80% | $2,102.15/mo |
| 90% | $2,362.30/mo |
| 100% | $3,938.58/mo |
Rates shown are the veteran-alone amounts effective December 1, 2025. A spouse, children, or dependent parents increase your payment at 30% and above. Every 10% you are under-rated can cost you thousands of dollars a year for the rest of your life.
Estimate Your Exact Pay Veteran Representation
Your VA Claim Exam: What to Expect
This official VBA video walks you through the entire C&P exam process. Understanding what happens in that room is the difference between a rating that reflects your true condition and one that undervalues you.
 Veteran Representation
What It Takes to Win These Benefits
Winning is not about how bad the condition is. It is about what your file proves. The rating board checks three things, and if one is missing the claim stalls no matter how much you hurt. Line up the evidence below before you file, not after the denial. The VA must help you gather records, but you are the one who knows where they are.
The Three-Part Test
Service connection under 38 CFR §3.303 requires all three:
- 1A current, diagnosed disability
- 2An in-service event, injury, or exposure
- 3A medical nexus linking the two
 Veteran Representation
The medical evidence the VA is actually looking for:
VA Claim Exams: Gastrointestinal & General Surgery
This exam is specific to your body system. The examiner uses a specialized DBQ for this category of conditions, and the tests they perform determine your exact rating level. Watch this before your appointment.
What to Expect at Your C&P Exam
Your Compensation & Pension (C&P) exam is not treatment. It is a rating tool. The examiner will not fix anything, they complete a Disability Benefits Questionnaire (DBQ) and check the boxes that decide your rating. What happens in that room can move your rating an entire level, so walk in prepared.
 Veteran Representation
The Forms You File, We Prepare Them For You
These are the forms that drive this claim. Start any of them on our site and an accredited agent prepares and files it for you, correctly, the first time.
Application for Disability Compensation
The core application that opens or reopens your claim.
Start this with usStatement in Support of Claim
Your own account and buddy/lay statements that fill the gaps in your record.
Start this with usAppoint Us as Your Representative
Authorizes our accredited agent to act on your behalf with the VA.
Start this with usUnemployability (TDIU) Application
Claims 100% pay when your conditions keep you from working, even below 100%.
Start this with usDisability Benefits Questionnaire
The exam form that captures the severity criteria for this specific condition.
Start this with usSMC & TDIU, When Your Rating Isn't the Whole Story
TDIU, Paid at 100% Without a 100% Rating
Total Disability based on Individual Unemployability (38 CFR §4.16) pays you at the 100% rate when your service-connected conditions prevent substantially gainful employment, even if your combined rating is lower. You may qualify if:
- One condition is rated 60% or higher, or
- Two+ conditions combine to 70% with at least one rated 40%, and
- Those conditions keep you from holding steady, gainful work.
- Cannot meet the numbers? Extraschedular TDIU under §4.16(b) may still apply.
Special Monthly Compensation (SMC)
SMC (38 CFR §3.350) pays above the normal schedule for especially serious losses, loss or loss of use of a body part, being housebound, or needing the aid and attendance of another person. Common levels:
- SMC-K, Loss / loss of use, Add-on for loss or loss of use of a specific body part (hand, foot, eye, reproductive organ, or certain other losses). Paid on top of your regular compensation. Can stack (up to the statutory cap).
- SMC-S, Housebound, Statutory housebound: a single 100% disability plus additional disabilities of 60%+, or substantially confined to your home. Veteran-alone rate shown.
- SMC-L, Aid & Attendance, You need the regular aid and attendance of another person, or have anatomical loss/loss of use of both feet, one hand and one foot, blindness, or are permanently bedridden. Veteran-alone rate shown.
- SMC-M, Higher Aid & Attendance, A higher level of aid and attendance (e.g., loss of use of both hands, or loss of use of both legs at a higher level). Veteran-alone rate shown.
These are the benefits veterans most often leave on the table because no one told them they qualified. If any of this sounds like your situation, call an accredited agent at 702-992-4883, we screen for SMC and TDIU on every case.



