

Musculoskeletal
Foot Conditions
Plantar fasciitis, flatfoot, hallux valgus, and the bilateral factor under §4.71a
Foot conditions, including plantar fasciitis, now expressly rated under Code 5269, are common in veterans who marched, jumped, and stood for a career. Bilateral involvement adds a §4.26 bonus factor.
Each Condition, Broken Out
Every Condition In This Category Has Its Own Page
These are separate diagnostic codes with separate criteria, separate exams and separate money. Each one below opens a full page: how it is rated, the schedule spelled out, the service-connection arguments, and exactly what happens at that specific C&P exam.
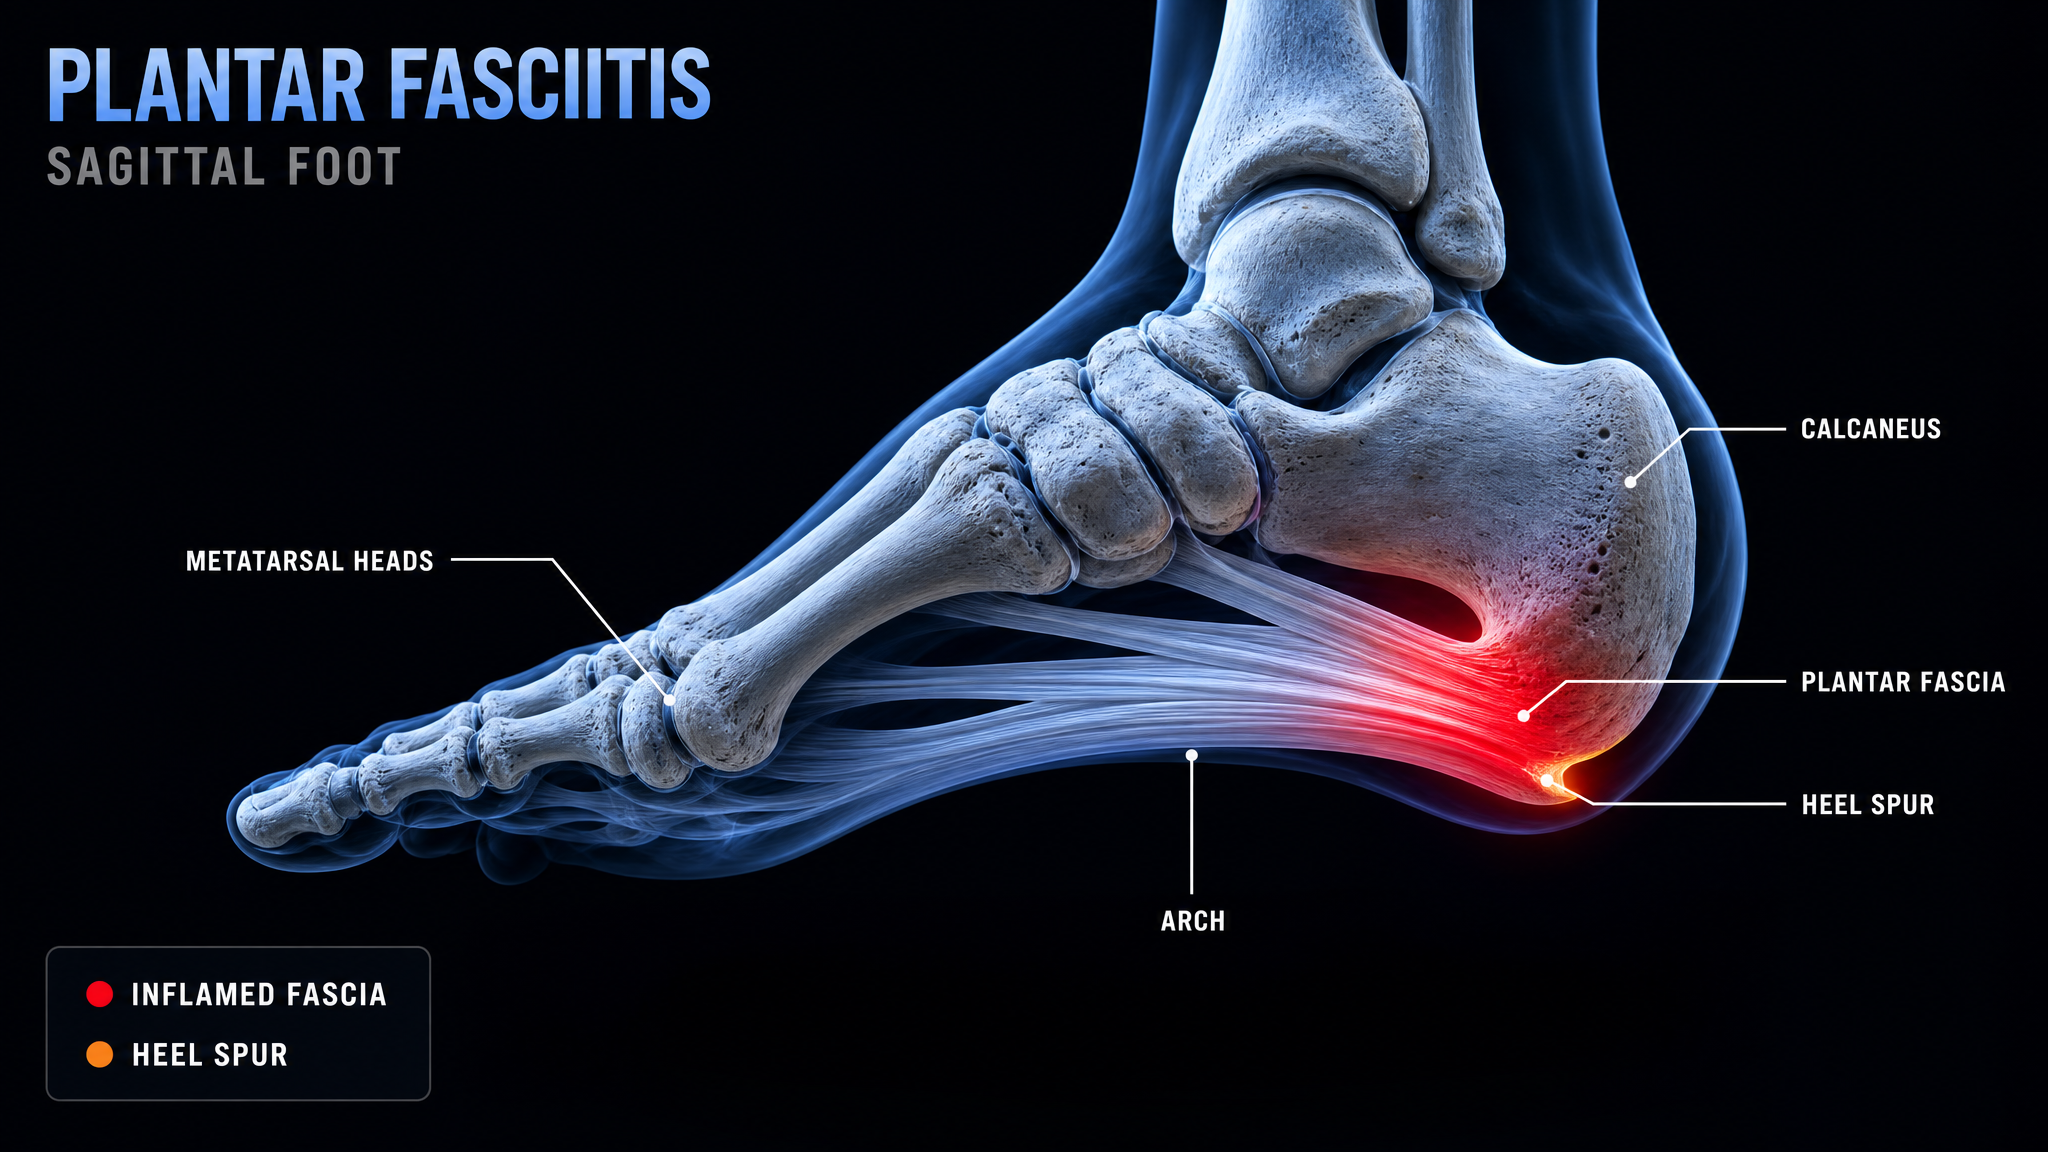
DC 5269
Plantar Fasciitis
Stabbing heel and arch pain that is worst on the first steps of the morning and flares after time on your feet.
Read the full Plantar Fasciitis (DC 5269) page
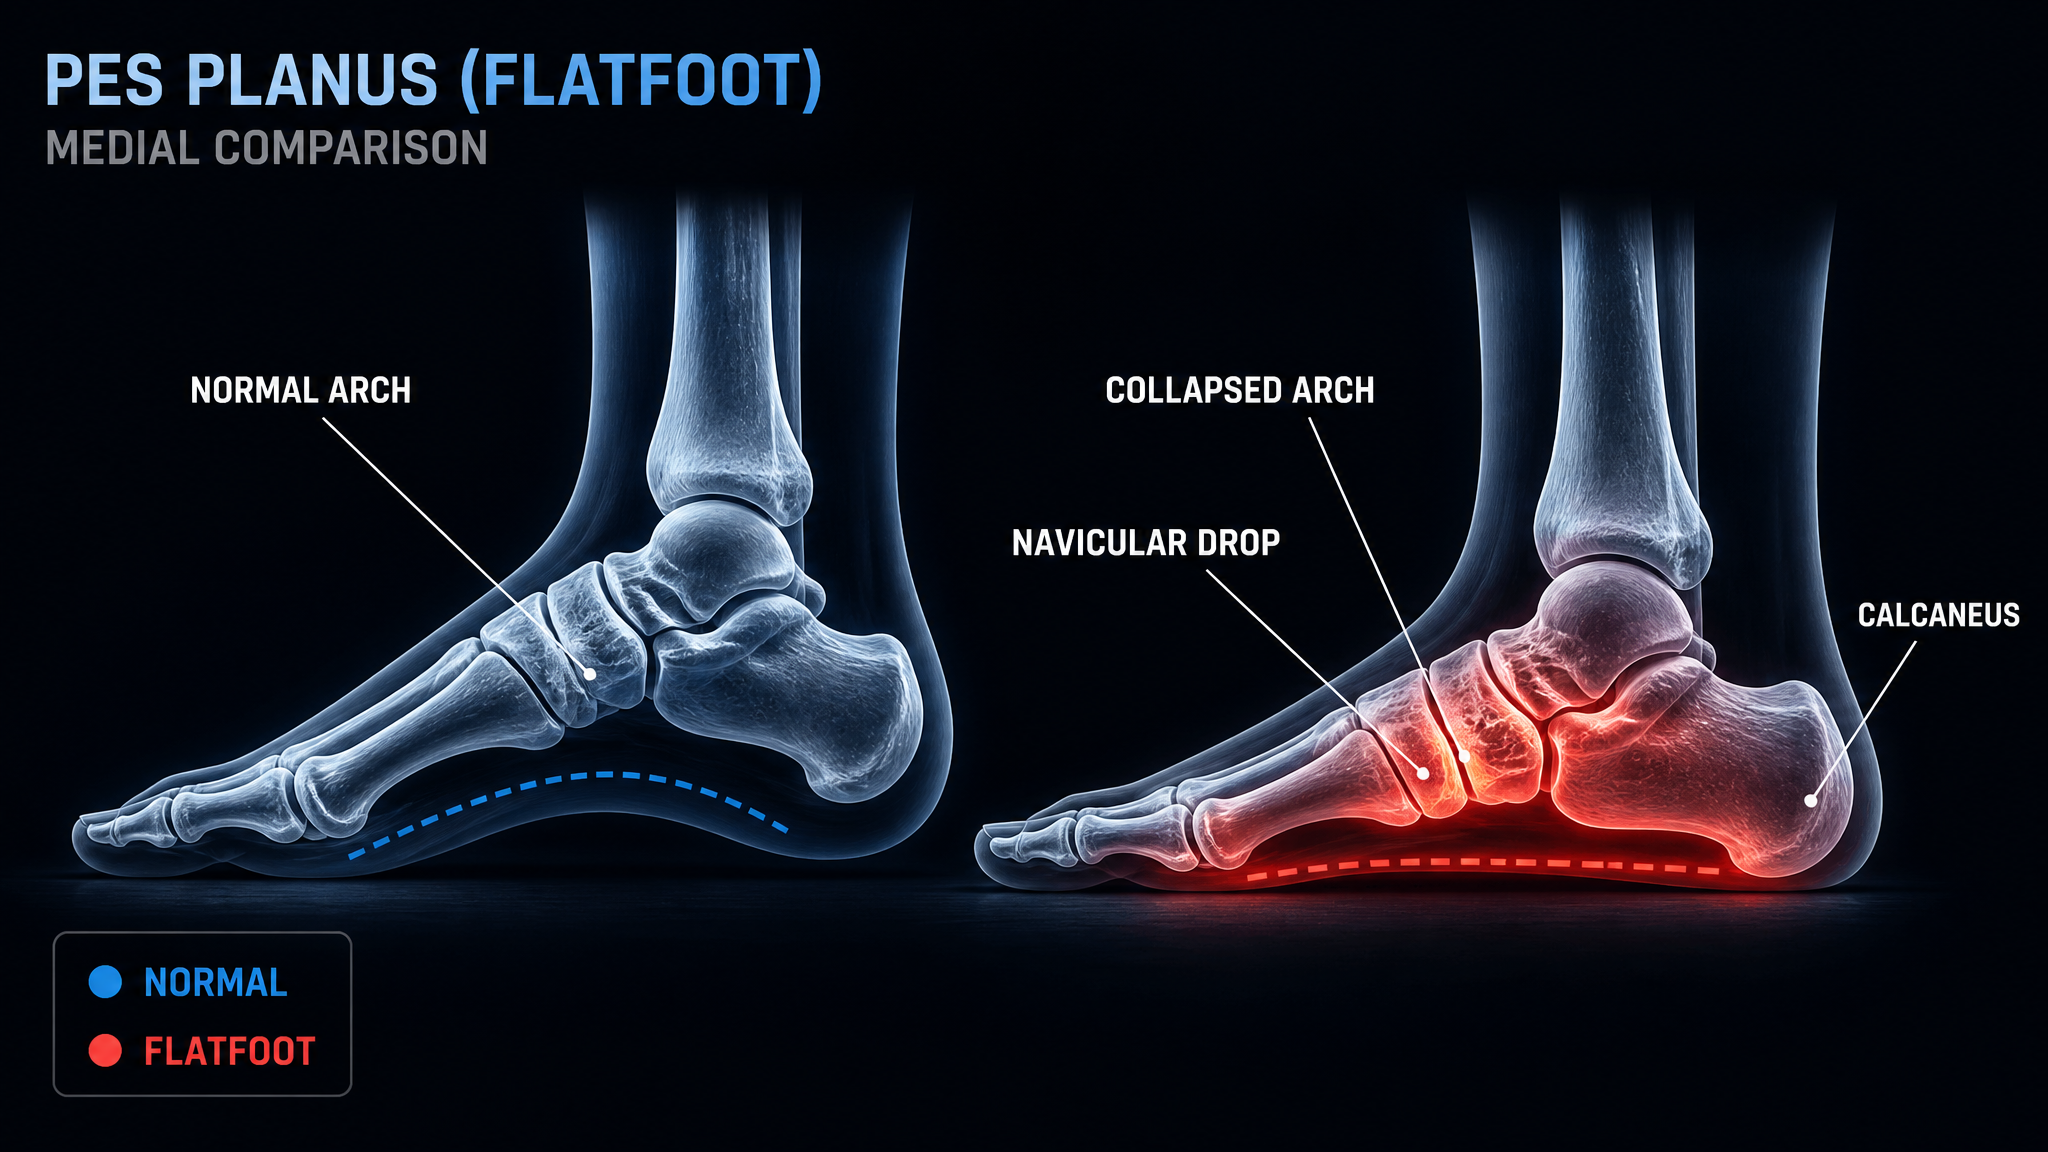
DC 5276
Pes Planus (Flatfoot)
Collapsed arches that leave the feet aching, rolling inward and giving out after standing or walking.
Read the full Pes Planus / Flatfoot (DC 5276) page
What Foot Conditions Really Is
Foot disability is flatfoot, plantar fasciitis, hallux valgus, and the residuals of fractures and nerve damage that make standing and walking a daily calculation. The VA rates most of it under 38 C.F.R. §4.71a, and whether one foot or both are involved changes which criteria apply. Your part: write down how long you can stand, how far you can walk, and what the inserts and shoes actually do for you.

What it actually means
Foot disability is flatfoot, plantar fasciitis, hallux valgus, and the residuals of fractures and nerve damage that make standing and walking a daily calculation. The VA rates most of it under 38 C.F.R. §4.71a, and whether one foot or both are involved changes which criteria apply. Your part: write down how long you can stand, how far you can walk, and what the inserts and shoes actually do for you.

What the VA measures
Acquired flatfoot under DC 5276 by symptom severity, plantar fasciitis under DC 5269, and the catch-all "foot injuries, other" under DC 5284 rated moderate, moderately severe, or severe, all in 38 CFR §4.71a.

Why claims get missed
Bilateral involvement is rated as one foot. Flatfoot and plantar fasciitis both have separate unilateral and bilateral criteria, and the bilateral factor under §4.26 applies on top.
What in Your Service Causes Foot Conditions
Service connection is not a feeling, it is a chain of evidence. These are the pathways the VA already recognises. Find yours, then make sure your file says it out loud.
Marching, running, and boots
Years in unsupportive boots on hard surfaces under load is the documented mechanism for acquired flatfoot and plantar fasciitis. Sick-call visits for foot pain are direct evidence.
Stress fractures and march injuries
Metatarsal stress fractures during training leave post-traumatic changes even when the note says healed.
Cold and immersion injury
Cold weather and prolonged wet-foot exposure produce lasting neurovascular damage rated under DC 7122.
Plantar Fasciitis Now Has Its Own Code
The VA added an express diagnostic code for plantar fasciitis (5269), ending years of forcing it into analogous ratings. Acquired flatfoot (pes planus, Code 5276), hallux valgus (5280), hammertoes (5282), and other foot injuries (5284) each have their own criteria under §4.71a.

The Bilateral Factor
When a condition affects both feet, §4.26 adds a bilateral factor, an extra 10 percent of the combined value of the paired disabilities before combining with the rest of your ratings. Veterans and even some representatives forget to confirm the bilateral factor was applied.

Secondary Chain Reactions
A bad foot rarely stays a foot problem. Years of walking around pain change your gait, and that strain travels up into the knees, hips, and back. Under §3.310, each of those conditions can be service-connected as secondary, but only if you claim it and back it with a medical opinion. The VA will not connect the dots for you. Here is where the chain usually goes.

Altered gait causing knee, hip, or back strain (§3.310)

Flatfoot secondary to an ankle or knee injury

Chronic pain contributing to a mental health claim
Establishing Service Connection
To establish service connection for a musculoskeletal condition, veterans must meet three criteria. First, there must be a current diagnosis. Second, there must be evidence of an in-service injury, repetitive strain, or the physical demands of your duties that could have caused or aggravated it. Third, a nexus, a medical link, must connect the in-service event to the current condition.

Current diagnosis of the joint or spine condition

In-service injury, repetitive strain, or documented physical demands

Medical nexus linking the condition to service ("at least as likely as not")

Imaging (X-ray or MRI) showing arthritis, disc disease, or joint damage
Lay statements describing onset and continuity of pain since service
Why Work With an Accredited Advocate
Veterans should seek the assistance of an Accredited VA Disability Advocate because we guide you through the complex claims process and ensure all necessary evidence is gathered and presented effectively. Our advocates are trained to identify and link service-related conditions, increasing the likelihood of a successful claim. We also provide personalized representation, helping veterans navigate appeals and secure the benefits they deserve. As a VA-Accredited Claims Agent, our fees are regulated under 38 CFR §14.636, and there are no fees unless we win your appeal.

The Rating Schedule, Spelled Out
Foot conditions are rated under 38 CFR §4.71a. Plantar fasciitis has carried its own code, 5269, since 2021; flatfoot, weak foot, claw foot, metatarsalgia, hallux valgus, hallux rigidus, hammer toe, tarsal and metatarsal malunion, and other foot injuries run from 5276 through 5284. Every code in that range is reproduced below, exactly as the rating schedule reads.
Plantar fasciitis, unilateral or bilateral, that does not meet the criteria below.
No relief from both non-surgical and surgical treatment, unilateral.
No relief from both non-surgical and surgical treatment, bilateral.
Notes: with actual loss of use of the foot, rate 40 percent. If you have been recommended for surgery but are not a surgical candidate, you are evaluated under the 20% or 30% criteria, whichever applies.
Mild; symptoms relieved by a built-up shoe or arch support.
Moderate; weight-bearing line over or medial to the great toe, inward bowing of the tendo Achillis, pain on manipulation and use of the feet, bilateral or unilateral.
Severe; objective evidence of marked deformity (pronation, abduction), pain on manipulation and use accentuated, indication of swelling on use, characteristic callosities, 20% unilateral, 30% bilateral.
Pronounced; marked pronation, extreme tenderness of the plantar surfaces, marked inward displacement and severe spasm of the tendo Achillis on manipulation, not improved by orthopedic shoes or appliances, 30% unilateral, 50% bilateral.
A symptomatic condition secondary to many constitutional conditions, characterized by atrophy of the musculature, disturbed circulation and weakness. Rate the underlying condition, minimum rating 10 percent.
Slight.
Great toe dorsiflexed, some limitation of dorsiflexion at the ankle, definite tenderness under the metatarsal heads, bilateral or unilateral.
All toes tending to dorsiflexion, limitation of dorsiflexion at the ankle to a right angle, shortened plantar fascia, marked tenderness under the metatarsal heads, 20% unilateral, 30% bilateral.
Marked contraction of the plantar fascia with dropped forefoot, all toes hammer toes, very painful callosities, marked varus deformity, 30% unilateral, 50% bilateral.
Anterior metatarsalgia, unilateral or bilateral.
Operated with resection of the metatarsal head; or severe, if equivalent to amputation of the great toe.
Rated as severe hallux valgus. Note: not to be combined with claw foot ratings.
Single toes.
All toes, unilateral, without claw foot.
Moderate.
Moderately severe.
Severe. Note: with actual loss of use of the foot, rate 40 percent.
Moderate foot injury.
Moderately severe foot injury.
Severe foot injury. Note: with actual loss of use of the foot, rate 40 percent.
Key Points to Remember
These are the rules the rating board applies to this condition, stripped down to what you can act on. Read each one and ask a single question: does my file prove it? If the answer is no, that is your homework, not the VA's. The VA has a duty to assist under 38 CFR 3.159, but it has no duty to build your argument for you.

Rated under 38 CFR §4.71a, plantar fasciitis (DC 5269), flatfoot (DC 5276), other foot injuries (DC 5284)

Severity of pain, deformity, and impact on weight-bearing drive the rating

Bilateral involvement can raise the evaluation and adds the bilateral factor

Document pain on manipulation, use of orthotics, and functional loss
What to Expect at Your Foot C&P Examination
A foot exam that is done sitting down is an inadequate foot exam. Nearly every criterion in the foot codes turns on what happens when you put weight on it, arch collapse on standing, whether the deformity corrects, tenderness under load, and whether orthotics or arch supports actually relieve it. Plantar fasciitis now has its own Diagnostic Code 5269, rated on whether the condition responds to treatment and whether one foot or both are involved.

Examination in the standing, weight-bearing position, not only on the exam table.

Documentation of arch height on and off weight-bearing, and whether any pes planus deformity is correctable by manipulation.

Palpation for tenderness under the plantar surface and the medial calcaneal tubercle, and for characteristic callosities.

Whether the Achilles tendon is in the correct alignment and whether any deviation improves with manipulation, the marked inward displacement and spasm findings are what separate the 30% and 50% flatfoot levels.

A specific record of what treatment has been tried and whether it worked: arch supports, custom orthotics, injections, night splints, physical therapy and surgery. Under DC 5269 that treatment history IS the rating criterion.
Range of motion of the great toe and the mid-foot, plus examination for hammer toes, hallux valgus, hallux rigidus, claw foot and metatarsalgia, several of which rate separately.

Gait observation over distance, and documentation of how far you can stand and walk before the pain stops you.
What Happens Once the C&P Exam Is Complete
The examiner compiles a detailed report, your medical history, physical findings, and diagnostic results, and assesses the severity, symptoms, and impact of your condition. That report is sent to the VA Regional Office handling your claim and becomes part of your official file, reviewed alongside your other evidence.
The VA may send the report back for corrections, clarification, or a second opinion if it finds it incomplete or unclear. This can delay your claim, because the VA requires thorough and accurate information to decide. Your claim only moves to the decision phase once the VA is satisfied with the evidence, which is exactly why the quality of the file we build for you matters so much. Once decided, your effective date controls how far back your back pay reaches, and any denial can be challenged through a Supplemental Claim, Higher-Level Review, or Board appeal.

The Advocate’s Take
Two bad feet are worth more than the sum of one plus one, the bilateral factor exists for a reason. Confirm it was applied.
Every Level the VA Can Assign You
These percentages come straight out of the rating schedule that governs foot conditions, Diagnostic Code 5269. Read them slowly. If your current rating does not match what your records actually show, that gap is exactly what an appeal exists to correct.
10%
Plantar fasciitis, unilateral or bilateral, that does not meet the criteria below.
20%
No relief from **both** non-surgical and surgical treatment, unilateral.
30%
No relief from **both** non-surgical and surgical treatment, bilateral.
Note
Notes: with actual loss of use of the foot, rate 40 percent.
Secondary Claims, Both Directions
Under 38 CFR §3.310, a condition caused or made worse by an already service-connected condition is itself service connected. That runs in both directions, and it is the single largest pool of unclaimed compensation in the system.
What can cause foot conditions
If one of these is already service connected, this condition can be claimed as secondary to it.
Knee, hip, or spine condition
Altered gait from a service-connected condition above the foot is a recognized cause of secondary foot disability.
Diabetes mellitus
Diabetic peripheral neuropathy of the feet is a standard secondary condition under §3.310.
What foot conditions can cause
If this condition is already service connected, each of these is a separate claim you may be owed.
Knee, hip, and lumbar spine disability
Chronic foot pain changes how you walk and is an accepted cause of secondary disability up the chain.
Plantar and tarsal nerve impairment
Neuropathic foot pain is separately ratable under §4.124a.
Depression from loss of mobility
Losing the ability to stand or walk without pain supports a secondary mental health claim.
A secondary claim still needs two things: a current diagnosis of the secondary condition, and a medical opinion saying it is at least as likely as not caused or aggravated by the service-connected condition. You do not have to prove it happened in service.
Building a Foot Conditions Claim That Wins
Every claim stands on three legs. Knock one out and the claim falls over, no matter how bad your symptoms are. Before you file, look at your file and find all three.
 01
A current diagnosis
A doctor has to say you have it, now, in writing. Not "reports symptoms of", a diagnosis. Without this leg, nothing else in the file matters.
 02
A link to your service
An event, an injury, an exposure, or an already service-connected condition. Service records, unit records, buddy statements, and your own account all count as evidence.
 03
A nexus that ties the two together
A medical opinion stating it is at least as likely as not that your service caused or aggravated the condition. That phrase is a legal standard: 50 percent or better. It is the leg most denials break.
Document the problem before you file
• Keep a dated symptom log for at least 30 days. Frequency, severity, and what it stopped you from doing.
• Get statements from people who see it, a spouse, a coworker, a battle buddy. Lay evidence is legal evidence.
• Pull your private treatment records. The VA only has to help; it does not have to go find everything.
• Write down what you have stopped doing. Lost work, lost sleep, lost activities. That is what impairment looks like on paper.
Your Rights in This Process
Most veterans walk into this system without knowing the rules the VA itself has to follow. That is how claims get denied for missing evidence the VA was supposed to help you find, and how exams get done by the wrong clinician. These six rights are written into federal regulation. Know them before you file, and make the VA honor every one of them when it decides your claim.

It costs nothing to file
Filing a VA claim is free. Accredited representatives may only charge for work on an appeal after an initial decision, and those fees are capped by 38 CFR §14.636.

The VA has a Duty to Assist you
Under 38 CFR §3.159 the VA must help you get the evidence it needs, and it must tell you what is missing before it denies you for missing it.

You can ask for a different examiner
You may request a trauma-informed clinician, or a clinician of a specific gender, for a C&P examination. Ask before the exam is scheduled.
You can claim every condition you have
There is no limit and no penalty. Primary conditions, secondary conditions, and conditions made worse by service all get filed.

You can appeal and be re-evaluated
A denial is not the end. You may submit new evidence, request a higher-level review, appeal to the Board, and ask for re-evaluation when your condition worsens.

You must be considered for TDIU
If your service-connected conditions keep you from holding substantially gainful employment, you may be paid at the 100 percent rate without a 100 percent rating.
Questions Veterans Ask About Foot Conditions Claims
What is plantar fasciitis worth?
Diagnostic Code 5269 was added in 2021: 10 percent when it fails to improve with non-surgical treatment, 20 percent for bilateral involvement, and 30 percent when it is bilateral and actual loss of use of the foot is present. Veterans rated before 2021 under a different code should have the newer criteria considered.
How is flatfoot rated?
Under DC 5276 by severity and by whether it is unilateral or bilateral, pronounced bilateral flatfoot with marked pronation and characteristic callosities not improved by orthopedic shoes is 50 percent. Severe bilateral is 30 percent. The bilateral criteria are higher than most veterans are told.
Can I claim both feet?
Yes, and you must claim both for the bilateral factor under §4.26 to be applied. Many decisions rate one foot when the records document both.
When You Are Ready to File
Talk to an accredited representative before you file. It costs nothing to ask, and the order you file in changes what the VA is allowed to award you. Albert L. Thombs Jr. is VA-Accredited Claims Agent #45147.
The application itself
This is the form that opens a disability compensation claim. List every condition you are claiming, and name the secondary conditions explicitly.
Release for private records
Authorises the VA to request records from your private doctors. Without it, treatment outside the VA may never reach your file.
Lay or buddy statement
The official form for your own statement and for statements from people who witnessed the event or the change in you.
What This Rating Is Worth (2026)
| 10% | $180.42/mo |
| 20% | $356.66/mo |
| 30% | $552.47/mo |
| 40% | $795.84/mo |
| 50% | $1,132.90/mo |
| 60% | $1,435.02/mo |
| 70% | $1,808.45/mo |
| 80% | $2,102.15/mo |
| 90% | $2,362.30/mo |
| 100% | $3,938.58/mo |
Rates shown are the veteran-alone amounts effective December 1, 2025. A spouse, children, or dependent parents increase your payment at 30% and above. Every 10% you are under-rated can cost you thousands of dollars a year for the rest of your life.
Estimate Your Exact Pay Veteran Representation
Your VA Claim Exam: What to Expect
This official VBA video walks you through the entire C&P exam process. Understanding what happens in that room is the difference between a rating that reflects your true condition and one that undervalues you.
 Veteran Representation
What It Takes to Win These Benefits
Winning is not about how bad the condition is. It is about what your file proves. The rating board checks three things, and if one is missing the claim stalls no matter how much you hurt. Line up the evidence below before you file, not after the denial. The VA must help you gather records, but you are the one who knows where they are.
The Three-Part Test
Service connection under 38 CFR §3.303 requires all three:
- 1A current, diagnosed disability
- 2An in-service event, injury, or exposure
- 3A medical nexus linking the two
 Veteran Representation
The medical evidence the VA is actually looking for:
VA Claim Exams: Musculoskeletal / Rheumatological
This exam is specific to your body system. The examiner uses a specialized DBQ for this category of conditions, and the tests they perform determine your exact rating level. Watch this before your appointment.
What to Expect at Your C&P Exam
Your Compensation & Pension (C&P) exam is not treatment. It is a rating tool. The examiner will not fix anything, they complete a Disability Benefits Questionnaire (DBQ) and check the boxes that decide your rating. What happens in that room can move your rating an entire level, so walk in prepared.
 Veteran Representation
The Forms You File, We Prepare Them For You
These are the forms that drive this claim. Start any of them on our site and an accredited agent prepares and files it for you, correctly, the first time.
Application for Disability Compensation
The core application that opens or reopens your claim.
Start this with usStatement in Support of Claim
Your own account and buddy/lay statements that fill the gaps in your record.
Start this with usAppoint Us as Your Representative
Authorizes our accredited agent to act on your behalf with the VA.
Start this with usUnemployability (TDIU) Application
Claims 100% pay when your conditions keep you from working, even below 100%.
Start this with usDisability Benefits Questionnaire
The exam form that captures the severity criteria for this specific condition.
Start this with usSMC & TDIU, When Your Rating Isn't the Whole Story
TDIU, Paid at 100% Without a 100% Rating
Total Disability based on Individual Unemployability (38 CFR §4.16) pays you at the 100% rate when your service-connected conditions prevent substantially gainful employment, even if your combined rating is lower. You may qualify if:
- One condition is rated 60% or higher, or
- Two+ conditions combine to 70% with at least one rated 40%, and
- Those conditions keep you from holding steady, gainful work.
- Cannot meet the numbers? Extraschedular TDIU under §4.16(b) may still apply.
Special Monthly Compensation (SMC)
SMC (38 CFR §3.350) pays above the normal schedule for especially serious losses, loss or loss of use of a body part, being housebound, or needing the aid and attendance of another person. Common levels:
- SMC-K, Loss / loss of use, Add-on for loss or loss of use of a specific body part (hand, foot, eye, reproductive organ, or certain other losses). Paid on top of your regular compensation. Can stack (up to the statutory cap).
- SMC-S, Housebound, Statutory housebound: a single 100% disability plus additional disabilities of 60%+, or substantially confined to your home. Veteran-alone rate shown.
- SMC-L, Aid & Attendance, You need the regular aid and attendance of another person, or have anatomical loss/loss of use of both feet, one hand and one foot, blindness, or are permanently bedridden. Veteran-alone rate shown.
- SMC-M, Higher Aid & Attendance, A higher level of aid and attendance (e.g., loss of use of both hands, or loss of use of both legs at a higher level). Veteran-alone rate shown.
These are the benefits veterans most often leave on the table because no one told them they qualified. If any of this sounds like your situation, call an accredited agent at 702-992-4883, we screen for SMC and TDIU on every case.
Keep Reading
One page never tells the whole story of a claim. The VA rates every condition on its own evidence, its own exam and its own diagnostic code, and the pieces connect in ways most veterans never see until a decision letter lands. These are the pages that pick up where this one stops. Read them before you file, not after a denial, because the cheapest fix in this process is the mistake you never make.



