

Reproductive and Gynecological Claims: What the Rating Schedule Owes You
Pregnancy, fertility, birth control, and every gynecological condition the VA tends to rate at zero. Here is how each one gets service connected and rated, and where the VA shortchanges women.
Pregnant and Enrolled: The VA Covers the Whole Pregnancy, and Your Newborn Too
I talk to women veterans who paid for a pregnancy out of pocket, or ran it through a spouse’s plan, because they assumed the VA does not do babies. It does. If you are enrolled in VA health care, maternity care is part of your medical benefits package, from the first positive test through the postpartum months. Most VA medical centers do not run labor and delivery units, so the VA pays for that care in the community through community care, with an OB you see close to home.
What that covers is broader than most women expect: prenatal visits, lab work, ultrasounds, genetic testing, prenatal vitamins and medications, labor and delivery including a C-section, postpartum visits, mental health care during and after the pregnancy, and miscarriage and stillbirth care. Supplies count too, things like a breast pump, nursing bras, and maternity and postpartum support belts. Ask for them six to eight weeks before your due date, not the week the baby comes. And the baby is covered. Under 38 U.S.C. §1786, the VA pays for your newborn’s care on the date of birth and the seven days after, and that window can be extended when the baby medically needs it.
Every VA facility assigns a Maternity Care Coordinator, and she stays with you from that first positive test through twelve months postpartum. She tracks the referral, lines up the newborn’s pediatric care before you leave the hospital, and helps you through the postpartum year. A few things fall outside the coverage so nobody surprises you later: home births, doula services, deliveries by a lay midwife who is not a registered nurse, and experimental procedures.
Here is the trap: community care runs on authorization. A woman sees an outside OB before the VA referral is approved, or goes into labor and never lets the VA know, and the bill comes to her. If you deliver in an emergency at a hospital the VA did not arrange, the VA has to be notified, and the window for that notice is short, generally within 72 hours. Do not let a paperwork gap turn covered care into a collection notice.
Your part: the day the test is positive, tell your VA primary care provider or the Women Veterans Program Manager at your medical center, and ask that a Maternity Care Coordinator be assigned to you by name. Keep a copy of every community care authorization, and make sure whoever is with you at delivery knows to notify the VA if you land somewhere unplanned.

Fertility, IVF, Adoption, and the Claim Underneath All of It
Fertility help at the VA comes in two tiers, and the line between them is the part nobody explains. Basic fertility care is open to any enrolled veteran, no rating required. IVF and adoption reimbursement are not. Those are tied to a service-connected condition that causes the infertility. So the claim decision you make, or never make, decides which doors open.
Here is the trap: women assume fertility help requires a rating and never ask for the basic care they already have, or they get the infertility treated for years and never claim the underlying condition that caused it. Without that service-connected finding on paper, the IVF and adoption benefits stay locked no matter how clear the medical picture is.
Your part: start the fertility evaluation through VA primary care now, and at the same time look hard at whether the cause traces to service. If it does, protect your date with an Intent to File on VA Form 21-0966, then claim the condition on the 21-526EZ.

Basic Fertility Care, No Rating Needed
Any enrolled veteran can get a fertility evaluation, lab work and imaging, genetic counseling, hormone therapy and fertility medications, surgical correction including tubal ligation reversal, intrauterine insemination, and egg, sperm, or embryo freezing. Marital status does not matter. When a service is not available inside the VA, ask for a community care referral to a fertility specialist.

IVF Runs Through a Service-Connected Condition
IVF requires a service-connected disability that leaves you unable to conceive without treatment. On March 28, 2024, the VA dropped the marriage requirement, so unmarried veterans and women in same-sex marriages now qualify, and donor eggs, sperm, and embryos can be used, though the VA does not pay to obtain them. The benefit has lifetime limits on attempts, and surrogacy is still not covered.

Adoption Reimbursement
If your service-connected condition causes infertility, the VA can reimburse qualifying adoption expenses for a child under eighteen. It is the same gate as IVF, which is one more reason the underlying claim matters. Keep every receipt and agency invoice from the start, and ask your Women Veterans Program Manager how to submit them before you file anything.

The Compensation Side
Pregnancy itself is not a disability, but a complication caused or worsened by service, or by a service-connected condition, is claimable. Gynecological conditions and surgical losses are rated under 38 CFR §4.116, and perinatal depression or anxiety tied to service is rated under §4.130. Loss or loss of use of a creative organ can also carry special monthly compensation under 38 CFR §3.350(a). Claim it by name, because raters miss it.
Birth Control, Menopause, and the Service History Behind Both
Your reproductive health care does not stop at pregnancy and fertility. If you are enrolled, the VA covers every FDA-approved form of birth control, the pill, patch, ring, shot, implant, hormonal and copper IUDs, emergency contraception, and permanent tubal procedures after real informed-consent counseling. The choice is yours and stays between you and your provider. The same enrollment covers menopause care: hormone therapy for the women it fits, sleep and mood support, and the bone-density and heart screening that matter more once menopause arrives, especially when it arrives early.
Now the part that turns care into a claim. A lot of women were put on continuous hormonal birth control in uniform to suppress a period in the field, on deployment, or aboard ship, where privacy and supplies were scarce. Years of that can leave marks that surface long after discharge, in bone density, mood, clotting, and fertility. If a provider ties a condition you have now to birth control you were directed to take in service, that is a direct service connection argument under 38 CFR §3.303. And if a service-connected condition led to removal of your ovaries, the sudden early menopause that follows, and what it does to your bones and heart, can be claimed as secondary under 38 CFR §3.310.
Here is the trap: women treat all of this as routine care. The visits happen, the prescriptions get filled, and nobody ever writes down where it started. Ten years of gynecological notes that never mention service are ten years of evidence working half as hard as they should.
Your part: at your next women’s health visit, give your provider the full history, the birth control you were placed on in service, how long, and why, plus any early or surgical menopause. Ask that it go into your chart. Every documented visit becomes evidence of chronicity, and a condition with years of treatment notes behind it is far harder for a rater to brush aside.

Four Rules That Decide What a Gynecological Claim Is Worth
Gynecological conditions are rated under 38 CFR §4.116, and that corner of the rating schedule is counterintuitive. The everyday percentages are small. The surgical codes are large. And some of the real value sits outside the percentage entirely, in special monthly compensation and in the cancers the PACT Act made presumptive.
Here is the trap: a woman with a genuinely disabling condition lands at 10 percent, decides that is the ceiling, and stops. Meanwhile the surgery she had, the organ she lost, or the cancer she was treated for never made it onto the claim by name, so the rater never weighed it.
Your part: list every gynecological condition and every surgery on the 21-526EZ, attach the operative and pathology reports, and ask your provider to complete the Gynecological Conditions DBQ. If a nexus opinion is needed, it should say the condition is at least as likely as not related to service, the standard under 38 U.S.C. §5107(b).

The Small Ladder, and How to Climb It
Most gynecological codes use one formula: 0 percent when symptoms do not need continuous treatment, 10 percent when they do, and 30 percent when they are not controlled by continuous treatment. Endometriosis under diagnostic code 7629 can reach 50 percent when laparoscopy confirms lesions involving the bowel or bladder. The word that moves you up the ladder is “uncontrolled,” so keep a symptom log that shows it.

Surgery Changes the Math
When service-connected disease leads to removal of the uterus or ovaries, §4.116 assigns a temporary 100 percent rating for three months after the surgery. After that, the permanent level depends on what was removed: 30 percent for the uterus, 50 percent for the uterus and both ovaries. Those levels sit well above the 10 and 30 percent ceilings most women assume they are stuck with.

SMC-K Rides on Top of the Rating
Loss or loss of use of a creative organ, including after a hysterectomy or removal of an ovary, triggers special monthly compensation under 38 U.S.C. §1114(k) and 38 CFR §3.350(a). It is paid in addition to your combined rating and does not depend on it. Raters miss it on women’s claims all the time, so name it on the claim and check every decision letter for it.

Reproductive Cancers and the PACT Act
The PACT Act made reproductive cancer of any type, and breast cancer, presumptive for veterans with covered Gulf War and post-9/11 service, so you do not have to prove the exposure caused it. A gynecological cancer is rated 100 percent during treatment and for six months after it ends, then a VA exam rates what remains. Make sure the residuals get rated, not just the cancer.
They Called It Hormonal and Handed You Birth Control. That Was Treatment, and It Counts.
Recurrent ovarian cysts, polycystic ovary syndrome, and ovarian adhesions are some of the most common conditions women carry out of the military, and some of the least claimed. In uniform, the pain and the irregular cycles were waved off as normal. You were put on the pill and sent back to work. That pill was a treatment decision, it is in your service record, and it is evidence that something was wrong while you were serving.
The VA rates disease, injury, or adhesions of the ovary under 38 CFR §4.116, diagnostic code 7615, using the general formula for the female reproductive organs. 0 percent when symptoms do not require continuous treatment. 10 percent when they require continuous treatment. 30 percent when they are not controlled by continuous treatment. The whole ladder turns on two words: continuous and controlled.
Here is the trap: if your condition was not noted on your entrance exam, the law presumes you were sound when you went in. Under 38 U.S.C. §1111 and 38 CFR §3.304(b), the VA can only defeat that by clear and unmistakable evidence that the condition existed before service and was not aggravated by it. Raters skip the second half all the time and deny a PCOS claim with one line saying it is congenital or started before you enlisted. That denial is legally wrong, and it can be challenged.
Your part: find every in-service visit for pelvic pain, irregular bleeding, or a cyst on imaging, and every prescription for hormonal control. Then ask your provider to state in writing whether your symptoms are still breaking through the treatment. That one sentence is the difference between 10 and 30.

Four Rules That Decide an Ovarian Claim
An ovarian claim is rarely just one rating. The condition itself, the surgery that may follow, and the metabolic damage PCOS does to the rest of your body can each carry their own number, and each one has to be claimed by name.
Here is the trap: the VA rates what you list and stops. It will not go looking for the diabetes, the blood pressure, or the special monthly compensation you never asked about.
PCOS Has No Code of Its Own, So Watch Which One They Borrow
Polycystic ovary syndrome is not named anywhere in the rating schedule. Under 38 CFR §4.20 the VA rates it by analogy to the closest code, and under §4.27 it shows on your code sheet as a built-up code such as 7699-7615. That choice matters. Rated against the ovarian formula, the question becomes whether your symptoms need continuous treatment and whether that treatment controls them. Read your code sheet. If the analogy ignores what PCOS actually does to you, that is an error you can raise.

Medication That Works Still Pays 10 Percent
Raters see that your symptoms are controlled and assign 0 percent. That is backwards. Under the general formula in 38 CFR §4.116, symptoms that require continuous treatment rate 10 percent even when the treatment works, and symptoms that break through continuous treatment rate 30. Hormonal therapy, daily pain medication, and scheduled imaging to watch recurring cysts are all treatment. Make sure the record says it is continuous, and say plainly when the cysts or the pain keep coming back anyway.

Losing an Ovary Opens Special Monthly Compensation
Removal of an ovary is rated under diagnostic code 7619: 100 percent for three months after the surgery, then 30 percent for complete removal of both ovaries, and 0 percent for one. Here is what the 0 hides. Under 38 U.S.C. §1114(k) and 38 CFR §3.350(a), the loss of even one ovary is the loss of a creative organ, and it pays special monthly compensation on top of your combined rating. Complete atrophy of both ovaries has its own code, 7620. Put the surgery on the claim and ask for the SMC by name.

The Damage PCOS Does to the Rest of Your Body
Diabetes rated under 38 CFR §4.119, diagnostic code 7913, and high blood pressure rated under §4.104, diagnostic code 7101, can each be service connected as secondary to PCOS under §3.310, and each gets its own rating. Weight gain is not a disability on its own, but VA General Counsel opinion VAOPGCPREC 1-2017 lets obesity serve as the middle link in the chain. Depression and anxiety from chronic pelvic pain count too, folded into one mental health rating under §4.130. Claim each condition by name.
Endometriosis and Fibroids: The Whole Fight Is Over the Word “Controlled”
Endometriosis and uterine fibroids put women through years of pain, heavy bleeding, and missed work, and in uniform most of it was charted as cramps. You took the ibuprofen, you went on the pill, and you kept going. Every one of those visits is evidence that the condition started while you were serving, and under 38 CFR §3.303 that is what direct service connection is built on.
Fibroids are rated as disease of the uterus under 38 CFR §4.116, diagnostic code 7613, on the general formula: 10 percent when symptoms require continuous treatment, 30 percent when they are not controlled by continuous treatment. Endometriosis has its own code, 7629, with the same 10 and 30 percent steps and a 50 percent level when laparoscopy confirms lesions on the bowel or bladder, the pain or bleeding is not controlled, and you have bowel or bladder symptoms.
Here is the trap: the rater reads one line in your chart that says “improved on hormonal therapy” and assigns 10 percent, or 0. Improved is not controlled. If you still bleed through, still lose days to pain, still need iron, the treatment is not controlling the condition, and the rating has to say 30.
Your part: stop letting “better” stand in your record as if it meant “fixed.” At every gynecology visit, tell your provider what still breaks through and ask her to write it down in those words. Your claim lives or dies on that sentence.

Four Moves That Win an Endometriosis or Fibroid Claim
These claims are lost on paperwork, not on medicine. The diagnosis needs the right test behind it, the symptoms need a record that shows they are not controlled, and the timing of your claim decides how much of the surgery rating you are paid.
Here is the trap: each of these four is a place where the VA denies or underrates quietly, with one sentence in the decision letter, and most women never notice it.

Endometriosis Needs a Laparoscopy Behind It
The note under diagnostic code 7629 in 38 CFR §4.116 says the diagnosis of endometriosis must be substantiated by laparoscopy. Symptoms, an ultrasound, or a doctor’s strong suspicion are not enough on their own, and raters deny on that note without explaining it. If you had a laparoscopy in service or after, get the operative report and the pathology into your file. If you never had one, ask your gynecologist whether it is medically indicated. The 50 percent level also depends on it, because it requires laparoscopy to confirm the lesions on your bowel or bladder.

Your Bleeding Calendar Is the Evidence
Heavy or irregular bleeding and pelvic pain that are not controlled by treatment move both endometriosis and fibroids to 30 percent. A rater will not know they are uncontrolled unless something in the record says so. Mark every day of bleeding, every day of pain that stopped you, every pad or product change in an hour, and every day of work you lost. Take the calendar to each appointment and ask your provider to note in the chart that the symptoms are breaking through the treatment. A provider’s note with your calendar behind it is hard to argue with.
Anemia Proves the Bleeding Is Not Controlled
Women expect a separate rating for the anemia that heavy bleeding causes. The note under diagnostic code 7720 in 38 CFR §4.117 says iron deficiency anemia due to blood loss is not rated under that code. It is rated under the criteria for the condition causing the blood loss. That does not make the lab work worthless. A low hemoglobin, low ferritin, or a prescription for iron while you are on hormonal therapy is objective proof that the bleeding is not controlled, which is the 30 percent question. Get every blood count into the record.

File Before the Hysterectomy, Not After
If surgery is coming, get the claim in now. Under 38 CFR §3.155 an intent to file holds your date for one year, and under §3.400 the effective date follows the date of claim. Once the condition is service connected, the surgery rates under its own code: diagnostic code 7618 for removal of the uterus, 100 percent for three months and then 30 percent, or 7617 for the uterus and both ovaries, 100 percent for three months and then 50 percent. Removal of the uterus also opens special monthly compensation under 38 CFR §3.350(a). Women who wait until after surgery lose months of that.
They Never Found a Cause. That Does Not Mean You Have No Claim.
Chronic pelvic pain is pain in the lower abdomen and pelvis that lasts six months or longer. In women veterans it grows out of endometriosis, scar tissue from surgery, infections, nerve damage, injuries in training, and military sexual trauma, and many women have more than one cause at once. Just as many were told it was cramps, stress, or all in their head, and they never filed because nobody could name it.
The law does not wait for a perfect label. In Saunders v. Wilkie, 886 F.3d 1356 (Fed. Cir. 2018), the Federal Circuit held that pain alone can be a disability under 38 U.S.C. §1110 when it causes functional impairment, even without a diagnosed underlying condition. There is no code named chronic pelvic pain, so the VA rates it by analogy under 38 CFR §4.20, usually against the gynecological formula in §4.116 or a nerve code in §4.124a.
Here is the trap: the analogy the rater picks sets your ceiling. Put everything under one gynecological code and the claim tops out at 30 percent, while your bladder symptoms, your nerve damage, and your depression never get looked at. Each cause that can be pulled out and rated under its own code should be.
Your part: stop waiting for a diagnosis before you file. Put in an intent to file, get a gynecology and pain workup, and get a nexus opinion that names the most likely cause, the in-service event, and exactly what the pain stops you from doing.

Four Ways to Break Pelvic Pain Into the Ratings It Deserves
Pelvic pain is rarely one thing, and it should rarely be one rating. Nerves, the pelvic floor, the bladder, and your mental health each sit in a different part of the rating schedule, with different formulas and different ceilings.
Here is the trap: the VA will not split the claim for you. List every symptom and every condition by name on the claim, or it gets rated as one lump.

Nerve Pain Has Its Own Codes, and a Low Floor
When the pain comes from a damaged or trapped nerve, it is rated under the neurological schedule in 38 CFR §4.124a. The ilio-inguinal nerve, the one most often injured in pelvic and abdominal surgery, is diagnostic code 8530, and it pays 0 percent for mild or moderate paralysis and 10 percent only when it is severe to complete. The pudendal nerve is not listed at all, so it has to be rated by analogy under §4.20. Know the ceiling before the exam, and make sure the examiner records how severe the nerve damage actually is.

The Pelvic Floor Leaves a Record
Pelvic floor physical therapy, nerve blocks, trigger point injections, and pain management visits are all treatment, and every one of them goes into the record with a description of what you cannot do. Ask for a pelvic health referral if you have never had one. When the cause is a vulvar condition such as vulvodynia, it is rated as disease of the vulva under diagnostic code 7610 on the same general formula as the rest of §4.116, so continuous treatment that is not controlling the pain points to 30 percent.

Your Bladder Is a Separate Claim
Pelvic pain with urgency, frequency, and painful voiding is often interstitial cystitis, and that is rated through the genitourinary schedule, not the gynecological one. Chronic cystitis under 38 CFR §4.115b, diagnostic code 7512, is rated as voiding dysfunction or urinary tract infection, whichever is worse, and the voiding dysfunction formula in §4.115a runs much higher than the gynecological ceiling when you need absorbent pads changed through the day or you wake to void again and again. Count the trips, day and night, and get a urology workup.

What Pain Does to Your Mind Counts Too
Years of pain wear you down, and depression, anxiety, and broken sleep caused by a service-connected pain condition can be service connected under 38 CFR §3.310. If you already have a mental health rating, they fold into that one evaluation under §4.130 and §4.14 rather than stacking, but they still raise its level. Keep a pain diary with the score, the trigger, what you canceled, and how you slept. That diary feeds both claims, and it is what you hand the examiner so she describes your worst days instead of the good one she happened to see.
The 100 Percent Does Not Just Stop. Here Is What the VA Has to Do First.
An active gynecological cancer, whether cervical, uterine, ovarian, vulvar, or vaginal, is rated under diagnostic code 7627 in 38 CFR §4.116 at 100 percent. Most women know that part. What they do not know is what happens after the last treatment, and that is where the VA takes the most away.
The note to code 7627 says the 100 percent continues past the end of surgery, radiation, or chemotherapy. Six months after treatment stops, the VA has to give you a mandatory examination, and any change based on that exam is subject to 38 CFR §3.105(e): a written proposal, your chance to answer, and only then a final decision. If there is no local recurrence or spread, the rating moves to your residuals, every lasting effect the cancer and its treatment left behind.
Here is the trap: the exam gets written up as no evidence of disease, and the proposal drops you from 100 percent to zero as if being cancer free means being whole. The swollen arm, the nerve damage, the lost organs, and the early menopause never get rated, because nobody listed them.
Your part: before that exam, make your own list of every residual and get each one in your treatment records. When the proposal comes, answer it inside the deadline with that evidence instead of letting the 100 percent fall to nothing.

Four Things That Keep a Cancer Rating From Collapsing
Beating the cancer should not cost you the compensation for what it did to your body. The rules give you deadlines, separate codes for residuals, and more than one path to service connection, and you have to use all three.
Here is the trap: the VA rates only what is in front of it. A residual that is not named in the record is a residual you are not paid for.

The Reduction Letter Starts Two Clocks
A proposed reduction under 38 CFR §3.105(e) gives you 60 days to send evidence showing why the rating should stay. Inside that, §3.105(i) gives you 30 days to ask for a predetermination hearing, and if you ask in time your payments stay at the current level until the hearing is held and decided. Miss the 30 days and you lose that protection. Mark both dates the day the letter arrives, ask for the hearing in writing, and use the full 60 days to build your residuals record.
Lymphedema and Neuropathy Are Ratings, Not Side Notes
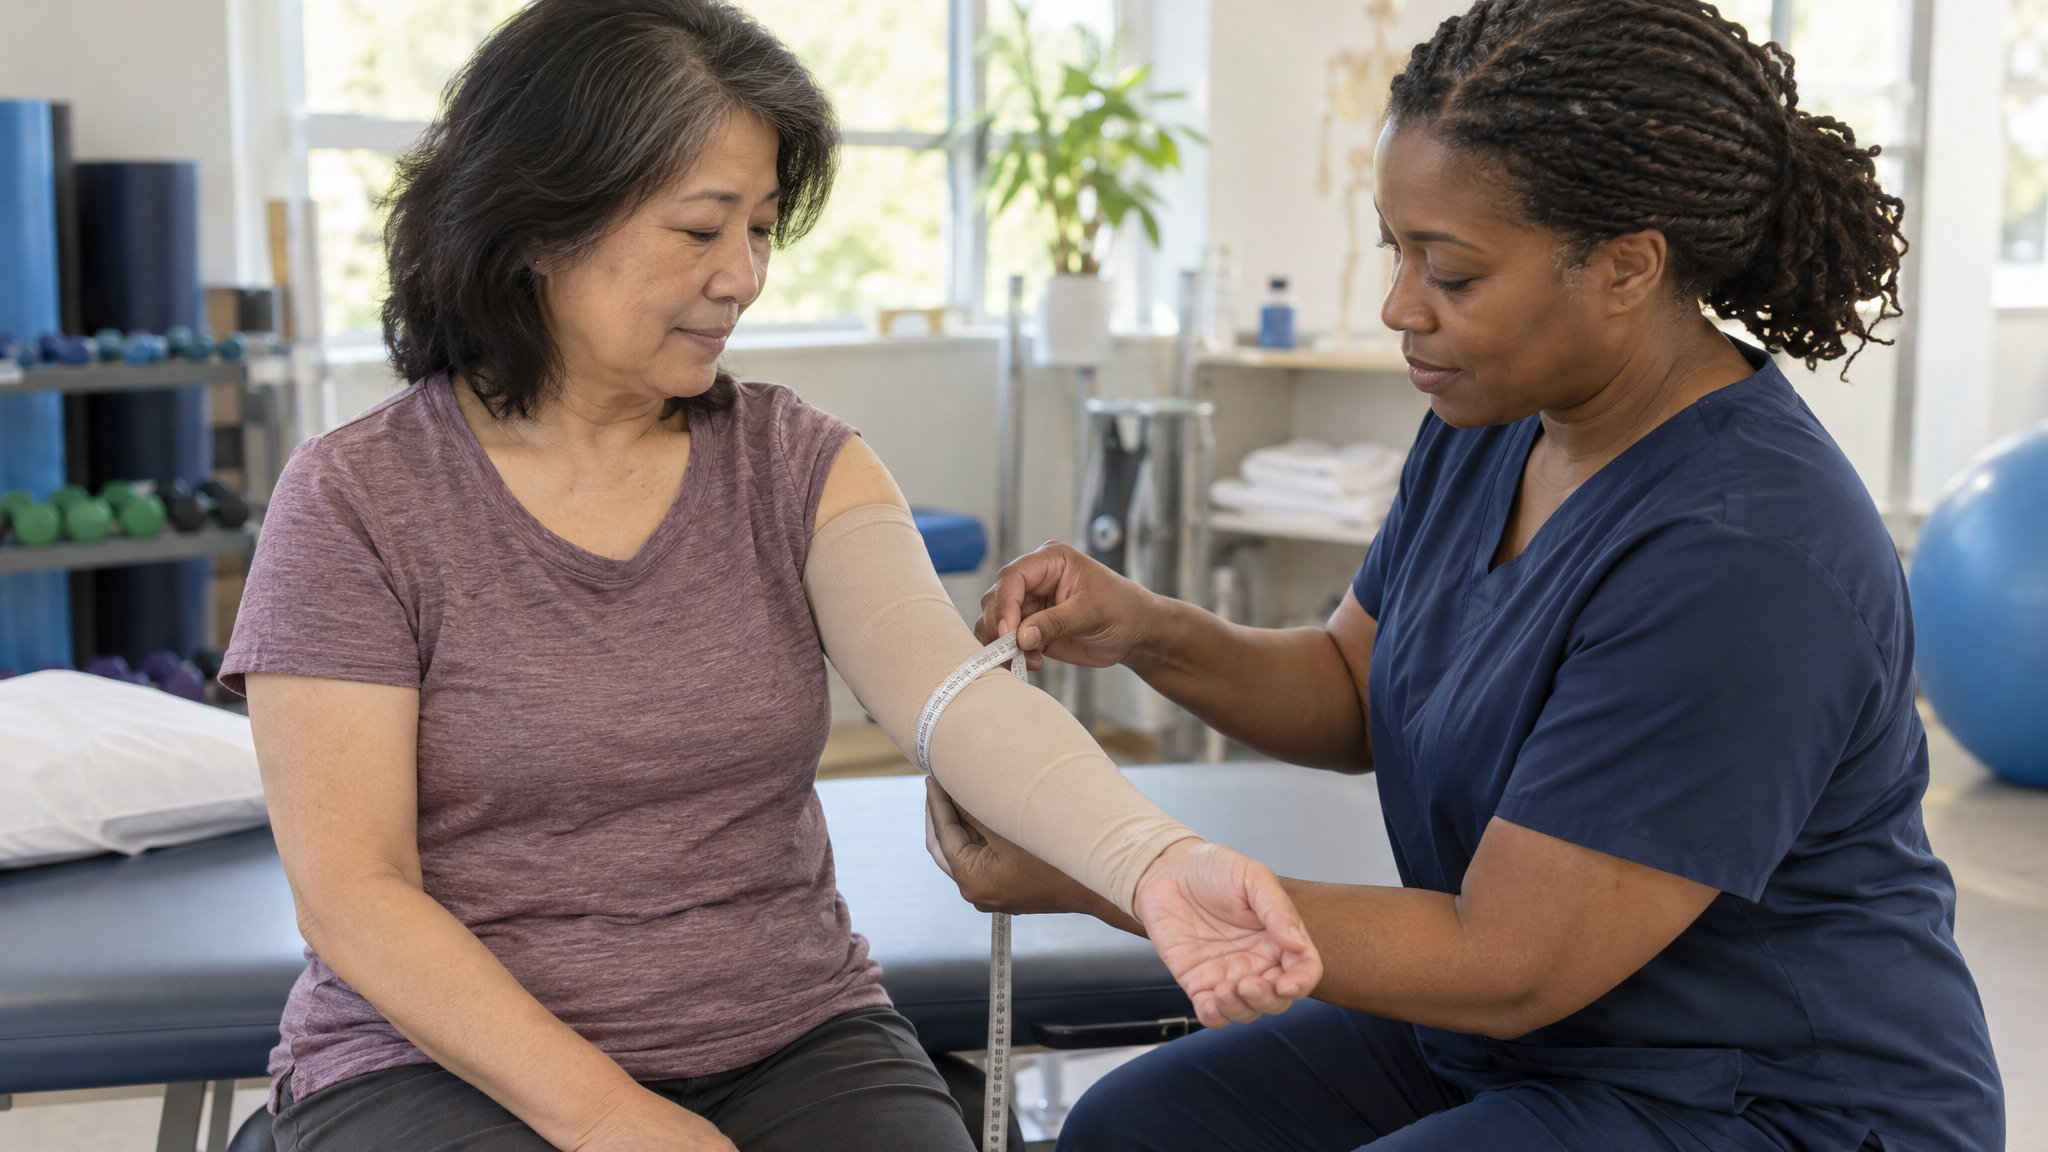
Lymph node removal and radiation can leave a limb that swells for life. There is no code named lymphedema, so it is rated by analogy under 38 CFR §4.20, and each affected limb is its own rating. Numbness, burning, and weakness in the hands or feet from chemotherapy are rated under the nerve codes in §4.124a, one rating for each nerve and each side. These are residuals of a service-connected cancer, so they come in with it. Get the swelling measured and the nerve damage tested, because a note that just says neuropathy rates low.

Early Menopause Is a Residual Too
Removing the uterus or ovaries to treat cancer is rated under its own gynecological codes in 38 CFR §4.116, and the loss of a creative organ supports special monthly compensation under §3.350(a), paid on top of the schedular rating. Treatment-driven menopause also brings bone loss, sleep problems, and depression. Bone loss can be claimed secondary under §3.310. Depression and anxiety from the cancer and what it took fold into one mental health evaluation under §4.130 and §4.14, and that single rating should reflect all of it.

Know Which Door Your Cancer Comes Through
Under the PACT Act, 38 U.S.C. §1120 makes reproductive cancer of any type and breast cancer presumptive for veterans with covered service in the Southwest Asia theater on or after August 2, 1990, or in Afghanistan and the other listed locations on or after September 11, 2001. The Camp Lejeune list in 38 CFR §3.309(f) does not include breast or gynecologic cancers. With no presumption, the claim goes direct under §3.303, and that takes a medical opinion tying the cancer to a specific exposure or event in service.
The Hysterectomy Code Rates What Was Removed. It Does Not Rate What the Surgery Left Behind.
When a service-connected gynecological condition ends in surgery, the VA moves you to a surgical code under 38 CFR §4.116: 7617, 7618, or 7619, with 100 percent for three months and then a settled rating based on the organs taken. Most women stop reading there, and so do most raters. That code pays for the loss of the organ. It says nothing about the hernia at the incision, the scar that still hurts, the nerve that went numb, or the bladder that has not worked right since.
Those are separate disabilities, and each one is rated under its own part of the schedule as a result of the service-connected surgery under §3.310. An incisional hernia rates under diagnostic code 7339 in §4.114. Adhesions inside the abdomen rate under 7301. A painful or unstable scar rates under 7804 in §4.118. Damage to the ilioinguinal nerve rates under 8530, and bladder injury under the voiding rules in §4.115a. The rule against pyramiding in §4.14 only bars rating the same symptom twice. Different symptoms get different ratings.
Here is the trap: the decision letter assigns the surgical code, the three months run out, and nobody ever asks what the operation did to you. The complications never get claimed, so they never get paid.
Your part: get the operative report and every follow-up note. Write down each problem that started after the surgery, in your own words, and claim each one by name as secondary to the surgery.

Four Things to Check After a Service-Connected Gynecological Surgery
The surgery is the most documented moment in your whole medical history. The operative report says exactly what was removed, what went wrong, and why. That makes it the best evidence you will ever have, and the easiest place to catch the VA getting it wrong.
Here is the trap: special monthly compensation for the lost organ and the surgical code are where most guidance ends. These four checks are where the rest of the money is.

Check the Code Against the Operative Report
Under 38 CFR §4.116, diagnostic code 7618 is removal of the uterus and settles at 30 percent. Code 7617 is removal of the uterus and both ovaries and settles at 50 percent. Raters mix them up. Put your decision letter next to the operative report and the pathology report and read what was actually removed. If both ovaries came out and the letter says 7618, file a Higher-Level Review inside the one year window. If the year has passed and the error was plain on the record the VA had, that is clear and unmistakable error under §3.105(a). If an ovary comes out later, file for the increase.

Not Healed at Three Months? Ask for More Time
The 100 percent period after surgery is three months, but bodies do not read the rating schedule. Under 38 CFR §4.30(b), the VA can extend a convalescence rating by one, two, or three more months, and then by up to six more with the approval of the service center manager, when recovery is still going on. The Court read convalescence to include the time you cannot get back to work in Felden v. West, 11 Vet. App. 427 (1998). Ask your surgeon to write down your restrictions and the expected recovery time, and ask for the extension before the three months end.

When VA Surgery Itself Caused the Harm
If the VA did the operation and you came out with a new injury, a cut bladder, a damaged nerve, an infection that should have been caught, 38 U.S.C. §1151 pays compensation as if that injury were service connected. Under 38 CFR §3.361, you have to show the VA care caused the added disability and that it came from carelessness, negligence, lack of proper skill, error in judgment, or similar fault, or from an event nobody could reasonably foresee. Treating you without informed consent under §17.32 counts as fault. Here is the trap: a known risk listed on the consent form is not automatically fault. You need a medical opinion that says what went wrong.

The Years Before the Surgery Still Pay
The hysterectomy code starts on the date of surgery. The fibroids, endometriosis, or bleeding that drove you there were disabling long before that. When the underlying condition was claimed earlier, the VA can assign different ratings for different periods, called staged ratings, under Fenderson v. West, 12 Vet. App. 119 (1999), and Hart v. Mansfield, 21 Vet. App. 505 (2007). That means the earlier years get rated on what your symptoms actually were, not lumped into the surgical code. Keep a binder of treatment dates so every stage has its proof.
More Women Veteran Guides
Each guide below covers one part of a woman veteran's claim in depth, with the regulations, the traps, and your part spelled out.
You are hereReproductive and Gynecological Claims
Maternity and fertility care, gynecological rating rules, ovarian conditions, endometriosis and fibroids, pelvic pain, reproductive cancers, and what gynecological surgery leaves behind.
You are reading this guide





