

When It Changed You: The Mental Health Claim the VA Owes Women Who Served
What grows out of military sexual trauma, how mental health conditions are rated, the discharge that followed the trauma, and who can see your claim. The law is more protective than the process admits.
The PTSD Is Not Where MST Stops, and Your Rating Should Not Stop There Either
When the VA finally connects your MST to PTSD or depression, most women think the claim is finished. It is not. Trauma does not stay in one lane. It wrecks your sleep, tightens your gut, follows you into the bedroom, and the medication that keeps you going brings its own damage. Every one of those downstream conditions can be service connected, and most women never claim a single one because nobody told them they could.
The rule is 38 CFR §3.310, and it has two doors. Under §3.310(a), a condition caused by your service-connected PTSD is service connected too, even if it started twenty years after you got out. Under §3.310(b), a condition your PTSD made worse is service connected for the amount of the worsening. That second door has a catch: the VA will not concede aggravation unless medical evidence shows how bad the condition was before the worsening, or the earliest record of it after. Your old treatment records are that baseline. Do not throw them away.
Here is the trap: the examiner writes that your condition is less likely than not caused by your PTSD and stops there. Caused and aggravated are two separate questions. In El-Amin v. Shinseki, 26 Vet. App. 136 (2013), the Court held that an opinion which never addresses aggravation is inadequate. A denial built on half an opinion is a duty to assist error, and it can be sent back.
Your part: list every condition you live with on the claim by name, and ask your provider to answer both questions in writing: did my PTSD cause this, and did my PTSD or its medication make it worse. The legal standard is at least as likely as not, not certainty.

Four Things to Know Before You Claim the Conditions That Grew Out of MST
A secondary condition rated under its own diagnostic code is combined with your PTSD rating under 38 CFR §4.25. VA math is not addition, so 50 and 30 do not make 80, but every properly connected secondary moves you up the table, and the steps from 70 to 90 to 100 are where the real money and the real access to care live.
Here is the trap: not every secondary gets its own number. Some are folded into the mental health rating, and some digestive codes cannot be stacked on each other. Knowing which is which keeps you from expecting a rating that the schedule will never give, and from missing one it will.
Your part: read these four before you file, so each condition goes in under the right theory.

Sleep Apnea and Migraines Get Their Own Ratings
Obstructive sleep apnea is an airway disease rated under the respiratory schedule at 38 CFR §4.97, diagnostic code 6847, and migraine is rated under §4.124a, diagnostic code 8100. Neither one is a PTSD symptom, so neither one is pyramiding. Each is rated on its own and combined. The link usually runs through a chain: hyperarousal and broken sleep, medication weight gain, chronic stress. Your doctor has to explain that chain, step by step, in the opinion.

Your Gut Counts, With One Stacking Rule
IBS and reflux are among the best documented consequences of chronic trauma, and both are rated under the digestive schedule at 38 CFR §4.114. Know this before you file: §4.114 bars combining certain digestive codes with each other, and the VA assigns one rating for the predominant condition instead. Claim every digestive condition anyway, because the combined picture decides which one is predominant and how high it goes.

Sexual Dysfunction Is Ratable, and It Can Pay SMC
Female sexual arousal disorder is in the rating schedule at 38 CFR §4.116, diagnostic code 7632. It is rated 0 percent, and the schedule directs the VA to review it for special monthly compensation under §3.350. It can be secondary to the PTSD itself or to the antidepressants you take for it, because a side effect of medication for a service-connected condition counts under §3.310. Women are almost never asked about this. Tell your provider, and name it on the claim.
What Gets Folded Into One Mental Health Rating
Depression, anxiety, and eating disorders that grow out of MST are mental disorders under 38 CFR §4.130. Under the anti-pyramiding rule in §4.14, they do not get a second percentage on top of PTSD. They are rated together as one evaluation. That does not make them worthless. Every symptom they add counts toward the level of occupational and social impairment, and that is often what moves a woman from 50 to 70 percent. Get each diagnosis into the record.
Eating Disorders Are Ratable, and the Weigh-Ins Are Part of the Story
Anorexia nervosa, bulimia nervosa, and binge eating disorder show up more often in women veterans than in the general population, and they are among the least claimed conditions in the entire system. Service builds the risk in: rigid weight and body-composition standards, public weigh-ins and tape tests, crash dieting to make weight before a board or a deployment, and the total loss of control over your own body that follows military sexual trauma. Restricting, bingeing, and purging are what a lot of women did to survive that environment. That is a clinical response, not a character flaw, and the VA treats it as a disability.
Start with care, because the care is the evidence. If you are enrolled, the VA provides individual and group therapy, nutrition counseling, medical monitoring, and medication for binge eating and the depression that often travels with it, and some VA facilities run specialized eating disorder programs. Anorexia and bulimia are listed in the rating schedule at 38 CFR §4.130 under diagnostic codes 9520 and 9521. Binge eating disorder is not named, so it is rated by analogy under 38 CFR §4.20 to the closest fit.
Here is the trap: most women never call it what it is. They see a habit, a diet, or a private shame, never a diagnosis, so it never reaches a chart, and a condition that is not in the chart does not exist to a rater.
Your part: tell a VA or private provider what is really happening and ask for a written diagnosis that names the type. Then request your service personnel records and look for the weigh-ins, the body-composition or weight-control program enrollments, and the counseling statements about your weight. Those pages put the start of the story in uniform.

Four Things That Decide an Eating Disorder Claim
An eating disorder claim wins or loses on four questions: how the condition connects to service, which rating formula applies, what it has done to the rest of your body, and what the examiner actually hears in the room.
Here is the trap: a lot of guidance tells women eating disorders are rated exactly like PTSD. They are not. Anorexia and bulimia have their own rating formula built on weight loss and incapacitating episodes, and a claim built around the wrong formula gathers the wrong evidence.
Your part: file an Intent to File on VA Form 21-0966 to protect your effective date, name the eating disorder and every physical complication on the 21-526EZ, and get a nexus opinion that explains the mechanism and says the condition is at least as likely as not related to service under 38 U.S.C. §5107(b).

Three Roads to Service Connection
Direct service connection under 38 CFR §3.303 covers an eating disorder that began in uniform under weight standards or after trauma. Secondary service connection under §3.310 covers one caused or worsened by service-connected PTSD, depression, or another condition. Aggravation under §3.306 covers one that existed before service and got worse. If nothing was noted at your entrance exam, 38 U.S.C. §1111 presumes you entered sound, and the VA must overcome that with clear and unmistakable evidence.

The Formula Counts Weight and Incapacitating Episodes
Under the Rating Formula for Eating Disorders in §4.130: 0 percent with a diagnosis but no incapacitating episodes, 10 percent with episodes up to two weeks a year, 30 percent with weight at or below 85 percent of expected minimum and more than two but under six weeks of episodes, 60 percent below 85 percent with six weeks or more, and 100 percent below 80 percent with six weeks or more plus hospitalization more than twice a year for tube or IV feeding. An episode means doctor-ordered bed rest and treatment, so keep every weight record and admission.

The Body Keeps Its Own Claims
Physical damage from an eating disorder can be claimed as secondary conditions: reflux and other digestive disease, heart rhythm problems, and bone loss from malnutrition are rated under their own codes. Obesity is not a disability by itself, but VA General Counsel Precedent Opinion 1-2017 lets it serve as the link when weight gain from binge eating causes sleep apnea, diabetes, or joint disease. Dental erosion from purging can be service connected for VA dental treatment, though the schedule pays a percentage for teeth only in narrow cases.

Tell the Examiner Everything
The exam is not the place to protect your pride. Describe how often you restrict, binge, or purge, your lowest weight, every hospitalization, and what it costs you at work and at home, and ask that the Eating Disorders DBQ be used. If you are already service connected for PTSD or depression, the VA rates your mental conditions as one evaluation rather than stacking them under §4.14, so the eating disorder adds weight to that single rating. Hiding it only lowers it.
You Served Alongside Women. You Do Not Have to Recover Without Them.
A lot of the women I work with spent their whole service as the only woman in the room, and they carried that into civilian life. They do not go to the veterans post because it feels like a men's club, they do not talk to civilian friends about what happened because it takes too long to explain, and the isolation does its own damage. The VA has an answer for that, and most women never hear about it: peer support. A VA peer specialist is a veteran who has lived through mental health struggles, substance use, or homelessness, recovered, and been trained and certified to help other veterans do the same. She is not your therapist. She is the woman who sits across from you and says, I have been there, here is what helped me.
Peer specialists work inside VA medical centers, community clinics, and housing programs, and the VA MISSION Act of 2018 pushed them into primary care teams so you do not have to be in a mental health program to meet one. Many VA medical centers and Vet Centers also run women-only groups for MST recovery, combat stress, transition, parenting, and relationships. Every VA medical center has a Women Veterans Program Manager, and she knows which groups meet locally and can often start one where none exists. The Vet Centers themselves, and the way their records are kept apart from your claim file, are covered on the mental health claims page of this site.
Here is the trap: nobody signs you up. Peer support is offered, not assigned, and a woman who waits for the VA to notice she is isolated will wait forever. The second trap is quieter: women find their people and stop there. Connection does not fix an unfiled claim or a rating that should be higher, and it does not put a single page of evidence in your file.
Your part: at your next VA visit, say the sentence out loud: I want a peer specialist added to my care plan, and ask for the Women Veterans Program Manager by name. Then work through the four cards below, because the same community that helps you heal can help you prove your claim.

Four Ways the Women Around You Strengthen Your Claim
Peer support is care first. But a VA claim is decided on the record, and the people in your corner can put things in that record that no examiner will ever see in a thirty-minute appointment: how you function week after week, and what happened back then from someone who was there.
Here is the trap: women assume a peer group or a friend's word does not count because it is not a doctor's note. Under 38 CFR §3.159(a)(2), competent lay evidence is evidence, and under 38 U.S.C. §5107(b) the VA has to weigh it, with the benefit of the doubt going to you when the evidence is evenly balanced.
Your part: pick the card that fits where you are today and take its one step this month.

A Peer Specialist on Your Care Team
A VA peer specialist does not diagnose, prescribe, or run therapy. She shares what worked for her, helps you get through VA systems, and can sit in on appointments with you, alongside your clinical team rather than in place of it. Because she works inside the VA, your contact with her becomes part of your VA treatment history, and steady engagement over months shows the kind of week-to-week struggle a rating under 38 CFR §4.130 is built on. Ask your mental health or primary care provider to add one, or ask the Patient Advocate.

Women-Only Groups and the Program Manager
Many women talk more openly in a room with no men in it, and many VA medical centers and Vet Centers run groups built for exactly that, on MST recovery, combat stress, transition, and parenting. If you live far from a facility, ask about groups that meet by VA Video Connect. If your facility has no women-only group, the Women Veterans Program Manager can often organize one when enough women ask. Make the call to her first. She opens every VA door at once.

Your Discharge Is Not a Wall
Women with an Other Than Honorable discharge often assume every door is closed. It is not. Under 38 U.S.C. §1720I, the VA provides mental and behavioral health care to former service members with an OTH discharge who served more than 100 days and deployed in a combat role, or who experienced military sexual trauma. That care, and the peer support that comes with it, does not wait on a discharge upgrade or a character of discharge decision. If one program turns you away over your discharge, do not assume they all will.

The Woman Who Saw It
Reconnecting with women you served with does more than heal. A woman who saw your behavior change after an assault, who knew you before the deployment and after, or who watched you skip meals to make weight can write a lay statement on VA Form 21-10210. For MST claims, 38 CFR §3.304(f)(5) lists statements from fellow service members as evidence that can corroborate what was never reported. Ask her to describe only what she saw and heard, in her own words, with dates and places as best she remembers. A statement that sounds coached is worth less than one that sounds like her.
On Your Worst Night, the Bill Is Not Yours
Women veterans stay away from VA mental health care for reasons I hear every week. They think they are not enrolled, they think their discharge shuts them out, or they are afraid of what the emergency room will cost. One law answers all three. Under 38 U.S.C. §1720J, added by the Veterans COMPACT Act of 2020 and implemented in 38 CFR Part 17 in January 2023, a veteran in an acute suicidal crisis gets emergent suicide care at no cost, at a VA facility or a hospital outside the VA, whether or not she is enrolled.
The care covers up to 30 days of inpatient or crisis residential treatment, or up to 90 days of outpatient care, and the VA can extend it when you still need it. The ambulance is covered too. It also reaches former service members with a discharge that is not dishonorable and not by court-martial who served more than 100 days and deployed to a combat theater or contingency operation, or who were the victim of a sexual assault, sexual battery, or sexual harassment while serving.
Here is the trap: the hospital outside the VA bills you because nobody told it you are a veteran, and the records from that stay never reach your claim file. A crisis that showed exactly how severe your condition is ends up as a collection notice instead of evidence.
Your part: tell the hospital you are a veteran, or have someone tell it for you, so the VA is notified. Afterward, get the discharge papers, and make sure that stay is in front of the VA the next time your mental health rating is looked at.

Four Ways Your Mental Health Care Becomes Evidence
Getting treated and getting rated are two different things, but the first one writes the record the second one is decided on. Every session, every score, and every hospital stay is either working for your claim or sitting where nobody sees it.
Here is the trap: a 30 minute exam on a good day gets weighed against years of treatment only if that treatment is actually in the file and says what your life is like.

Your Therapy Scores Are Evidence
Cognitive Processing Therapy and Prolonged Exposure run on scored checklists, usually the PCL-5 for PTSD and the PHQ-9 for depression, and those numbers go into your treatment notes session after session. Under 38 CFR §4.126(a), the VA rates a mental condition on the frequency, severity, and duration of symptoms across the whole record, not one exam. A string of high scores is hard for an examiner to wave away. Here is the trap: a note that says progressing in therapy gets read as better. Ask your therapist to record the scores and what your days actually look like.

Twenty-One Days Inpatient Pays at 100 Percent
If a service-connected mental health condition keeps you in the hospital for more than 21 days at VA expense, 38 CFR §4.29 pays the full 100 percent rate from the first day of that stay through the last day of the month you go home, no matter what your regular rating is. The VA does not always grant it on its own. Ask for the discharge summary with both dates, and send a short written request naming §4.29 and the service-connected condition that was treated.
Family Counseling Writes Down What Your Family Sees
Under 38 U.S.C. §1782, when you are being treated for a service-connected condition, the VA has to provide counseling, including marriage and family counseling, to your immediate family when it is needed for your treatment. Those sessions record what happens at home: the outbursts, the nights you do not sleep, the days you cannot leave the house. Your sister, spouse, or adult child can also write a statement, and under Layno v. Brown, 6 Vet. App. 465 (1994), she is competent to describe what she sees with her own eyes.

A Crisis Belongs in Your Claim File
Suicidal ideation is listed in the 70 percent criteria of 38 CFR §4.130, and in Bankhead v. Shulkin, 29 Vet. App. 10 (2017), the Court held that its presence alone can support that level, and that the VA cannot brush it aside because you never acted on it. Crisis care at a hospital outside the VA creates records the VA does not have until someone asks. Name every facility on your claim so the VA must try to get them under §3.159(c)(1), and keep your own copies.
They Called It a Personality Disorder and Sent You Home. That Label Can Be Undone.
I see the same file over and over. A woman serves well for years. Then something happens, often an assault or harassment she never reported or reported and regretted. Her evaluations drop, the counseling statements pile up, and she is out the door with a personality disorder or adjustment disorder on her paperwork, or a misconduct discharge that ends in Other Than Honorable. Nobody asked what changed. That label then follows her into the VA.
On the VA side, 38 CFR §3.303(c) and §4.127 say a personality disorder is not a disease or injury the VA compensates. But §4.127 also says a mental disorder superimposed on a personality disorder can be service connected, and nothing makes the label written in service binding forever. If a clinician today finds that what the military called a personality disorder was really PTSD or depression that began after the event, that is a service connection claim, and the marker rules in §3.304(f)(5) apply to it.
On the military side, the review boards must apply liberal consideration under 10 U.S.C. §1552(h) and §1553(d) when the request rests on PTSD or a brain injury tied to military sexual trauma. They can change the characterization and the narrative reason, and a personality disorder reason is often changed to Secretarial Authority. These are two separate fights. File the VA claim now, because the effective date under §3.400 runs from when the VA receives it, not from when a board rules.
Here is the trap: the rater sees personality disorder in your service records and denies under §3.303(c) without ever asking whether it was misread. Then the examiner reads the old label and repeats it.
Your part: get a current evaluation from a clinician who reads your in-service records and states, with reasons, whether those symptoms are better explained by PTSD, depression, or another acquired disorder that started after the event. One strong opinion can carry both the VA claim and the board application.

Four Questions the Board Has to Answer, and How to Win Each One
The Kurta memo of August 25, 2017 is Defense Department guidance that tells the Discharge Review Boards and the correction boards how to handle requests involving mental health conditions, sexual assault, or sexual harassment. It boils the decision down to four questions, asked in order. Lose one and you usually lose the case.
Here is the trap: most applications tell the story and ask for an upgrade. They never answer the four questions. Build your statement and your evidence around them, one heading for each.
Question One: Was There a Condition or an Experience?
The board first asks whether you had a condition or an experience that may excuse or mitigate the discharge. Read that again: an experience counts. Under the Kurta memo, sexual assault and sexual harassment qualify on their own, with or without a diagnosis, and your own testimony, written or spoken, may be enough to establish it. Here is the trap: women write two careful paragraphs and leave out the event because it is painful. Your part: name what happened, when, and who you told, in your own words. The board cannot weigh what you never put in front of it.

Question Two: Did It Happen During Service?
Most assaults were never reported, so the proof is rarely a report. Kurta tells boards that evidence may come from sources outside your service record and that changes in conduct can themselves show the event happened. These are the same markers the VA must consider under 38 CFR §3.304(f)(5): a transfer request, falling evaluations, sick call visits, pregnancy or disease testing, a sudden run of counseling statements, leave you suddenly needed. A diagnosis made years later is fine. Your part: build a dated timeline that shows the line where your record changed.
Question Three: Does It Explain the Conduct?
Now the board asks whether the condition or experience actually excuses or mitigates what you were discharged for. Missed formations from avoidance, drinking to sleep, a blowup at the person they kept assigning near your attacker: those connect. Kurta is honest that premeditated misconduct is not generally excused, so do not argue that everything is. Here is the trap: a general letter that says you have PTSD does not answer this question. Your part: ask a clinician to tie specific symptoms to the specific write-ups, one by one.

Question Four: Does It Outweigh the Discharge?
Last, the board weighs the whole person. The Wilkie memo of July 25, 2018, tells boards to look at the quality of your service before the decline, how serious the misconduct really was, and what you have done with your life since: work, school, treatment, caregiving. Show all of it. If the answer is no, it is not the end. You can ask the same board to reconsider with new evidence, move from the Discharge Review Board to the correction board under 10 U.S.C. §1552, and after that seek review in federal court. Read the decision itself, because it tells you which question you lost on.
If the Trauma Is What Ended Your Service, the Law Sets a Floor Under Your Rating
I talk to women every week whose careers ended a few months after the assault. The evaluations dropped, the lateness started, the counseling statements piled up, and then came the separation paperwork. Nobody in the chain of command called it what it was. The VA does not always call it what it is either. But there is a regulation written for exactly this story, and I almost never see it applied without someone asking for it.
It is 38 CFR §4.129. When a mental disorder that develops in service as a result of a highly stressful event is severe enough to bring about your release from active service, the VA must assign no less than 50 percent and schedule an examination within six months of your discharge to decide whether a change is warranted. Military sexual trauma is a highly stressful event. PTSD, depression, and anxiety that grew out of it all qualify as the disorder. The rule does not say the release had to be a medical discharge.
Here is the trap: the rater sees a separation for misconduct or a personality disorder, rates the PTSD at 10 or 30 percent from day one, and never asks why you were separated. The floor is mandatory, but only if the record shows the disorder is what sent you home.
Your part: know that this floor covers the stretch right after discharge. It matters most to women who separated within the last year, and to women whose first rating covered that period and came in low. If you left decades ago and are filing for the first time now, the floor will not reach back, and your rating turns on the §4.130 formula. The four steps below show how to make it count.

Four Steps to Make the 50 Percent Floor Hold
The floor is not automatic in practice. It depends on proof of why you left, when you filed, whether you showed up for the follow-up exam, and whether you fought a reduction the right way. Miss any one of those and the 50 percent can disappear on paper even though the regulation never changed.
Here is the trap: each of these steps has its own deadline, and the VA will not remind you of any of them. Write them down.

Prove the Disorder Is What Sent You Home
The floor only applies when the trauma disorder was severe enough to bring about your release. The VA will not connect those dots for you, so you connect them on paper. Pull the narrative reason and separation code on your DD 214, your separation physical, any counseling statements, any medical or physical evaluation board records, and the mental health notes from your last months in uniform. A discharge for misconduct, a pattern of minor offenses, or a personality or adjustment disorder can still be the trauma talking, the same marker logic §3.304(f)(5) uses to prove the event. Here is the trap: the rater reads the stated reason and stops there. Your part: lay out the timeline from the event, to the change in you, to the separation, in one short written statement, and ask your provider to say in a medical opinion that the disorder drove the discharge.

The Window Is the Year After Discharge
Under 38 CFR §3.400(b)(2)(i), a claim received within one year of separation is paid from the day after you left the service. That is the only way the §4.129 period lines up with your pay. If you file years later, your effective date is your claim date, and the floor has nothing left to cover. Here is the trap: women who separated recently wait until they feel ready, and the year runs out. File inside that year, even with a short statement, and build the rest later. If you were already rated inside that window and got less than 50 percent for those first months, the Court in Fenderson v. West, 12 Vet. App. 119 (1999), requires staged ratings that fit each period. If the decision is still open, that is a Higher-Level Review. If it went final and the rater ignored a release the record plainly showed, that can be clear and unmistakable error under §3.105(a).

Do Not Miss the Six Month Exam
Section 4.129 tells the VA to schedule an examination within six months of your discharge. That exam decides what happens after the floor, so treat it like the most important appointment of the year. Under 38 CFR §3.655, if you fail to report for a scheduled exam on a running award without good cause, the VA can move to reduce or stop that award. Good cause includes things like illness or hospitalization, and you have to tell the VA, in writing, before or right after the date. Here is the trap: the letter goes to an old address, nobody reschedules, and the rating drops on a no show. Your part: keep your address current with the VA, bring your treatment records and a written list of your worst symptoms, and describe your worst days, not your best hour.

A Cut After the Floor Is Still a Reduction
If that exam leads the VA to lower your rating and your monthly payment, 38 CFR §3.105(e) controls. The VA must first propose the reduction in writing, explain why, and give you 60 days to send evidence. Under §3.105(i), if you ask for a hearing within 30 days of that notice, your payment stays at the current level until the hearing is held and decided. Then the rating moves to the §4.130 formula, where the question is your occupational and social impairment, with symptoms judged by frequency, severity, and duration under §4.126(a). Here is the trap: women read the proposal, assume it is final, and let both deadlines pass. Your part: mark both dates the day the letter arrives, ask for the hearing in writing, and send current treatment notes that show how you are actually living.
“Will This Follow Me?” The Fear That Keeps Women From Filing, and the Facts
The question I hear most from women before a mental health or MST claim is not about evidence. It is who is going to find out. Will my boss see it. Will it cost me my clearance. Will they take my guns. Will my family read what I wrote. Those fears are reasonable after what the system already did to you, and they keep a lot of women from ever filing a claim they would win.
So here are the facts, plainly. A VA claim is confidential by federal statute. Your statement, your exam, and your treatment records go into your claims file, where they are read by the people deciding the claim: the rater, the examiner, a senior reviewer, and if you appeal, the Board. A claim does not change your military record or your discharge, and it is not posted anywhere. You have the right to see everything in that file yourself, and you should.
Here is the trap: the rumors are worse than the rules. Women skip the claim to protect a job or a clearance that the claim was never going to touch, and they lose years of compensation and care for nothing.
Your part: put your specific worry on the table with your representative before you file. Most of the time the answer is in the four rules below, and you can file knowing exactly where your information goes.

Four Rules That Decide Who Sees Your Mental Health Claim
Each of these answers one of the fears I hear every week. None of them is a promise that nothing can ever be disclosed. They are the actual rules, with the actual exceptions, so you can decide with your eyes open.
Here is the trap: anyone who tells you a claim is completely secret, or that it will ruin your life, is guessing. Go by the rule.

Your Employer Does Not Get Your Claim File
Under 38 U.S.C. §5701 and the VA's rules at 38 CFR §1.500 through §1.527, the files, records, names, and addresses in a VA claim are confidential. The VA does not send your claim, your diagnosis, or your statement to an employer, a landlord, or a private background check company, and those parties cannot get it without your written consent. The statute does list narrow exceptions, such as a federal court order or a request from another federal agency, so I will not tell you the file is sealed from everyone forever. Here is the trap: women assume a mental health claim becomes public. It does not. Your part: never sign a blanket release for an employer or insurer without reading exactly which records it covers.

Counseling Is Not a Clearance Killer
Women who hold or want a federal security clearance worry the most, and they put off care and claims because of it. The federal adjudicative guidelines, Security Executive Agent Directive 4, Guideline I, say that seeking mental health care is not, by itself, a reason to deny or revoke a clearance. The current mental health question on the SF 86 asks about specific things, like court ordered or involuntary hospital commitments, findings by a court or agency, and certain serious diagnoses, not routine counseling for PTSD, depression, or anxiety. Here is the trap: staying untreated is what actually damages judgment and reliability, the very things the guidelines weigh. Your part: read the current question on the form itself, answer it truthfully, and get treated.

A Rating Is Not an Incompetency Finding
The VA reports a veteran to the federal background check system for firearm purchases when it has found her unable to manage her own VA benefits under 38 CFR §3.353, which leads to a fiduciary. A PTSD or depression rating does not do that, not at 30 percent and not at 100 percent. The percentage measures impairment. Incompetency is a separate finding, and the VA has to propose it first, tell you why, and give you the chance to send evidence and ask for a hearing under §3.103 before it becomes final. Here is the trap: women hear a rumor and never file. Your part: if a proposed incompetency letter ever arrives, it has a deadline, and you answer it with medical evidence that you handle your own money.

Substance Use Records Need Your Signature
Many survivors drank or used to get through it, and that shows up in treatment notes. Under 38 U.S.C. §7332, VA records about drug or alcohol treatment, along with HIV and sickle cell records, get extra protection, and the VA will not release them even to your own representative unless you specifically authorize it. The appointment form for an accredited agent, VA Form 21-22a, has its own box for that authorization. Here is the trap: leave it blank and your representative argues your case without seeing the records that prove how bad it got. Primary alcohol abuse is not paid on its own under §3.301, but in Allen v. Principi, 237 F.3d 1368 (Fed. Cir. 2001), the Federal Circuit held that substance use caused by a service connected condition counts toward that condition's rating. Your part: decide that box on purpose.
You Clench Your Jaw in Your Sleep. The Trauma Put It There, and the VA Rates the Damage.
Ask a survivor how she sleeps and she will tell you about nightmares. Ask her about her jaw and she often goes quiet, then admits it aches every morning, clicks when she chews, and locks when she yawns. Hypervigilance does not turn off at night. Years of clenching and grinding wear down teeth and damage the joint where the jaw meets the skull. That is temporomandibular disorder, and it is a physical condition with its own rating code.
It is claimed as a secondary condition under 38 CFR §3.310: a disability caused or made worse by a condition the VA has already service connected. It is rated under the dental and oral schedule, 38 CFR §4.150, diagnostic code 9905, on measured jaw motion and on any physician-prescribed diet restriction. Because it rates jaw function, not your mental health symptoms, it is a separate rating from your PTSD rating, not a duplicate of it.
Here is the trap: nobody connects the jaw to the trauma. The dentist treats your teeth, the mental health provider treats your sleep, and neither one writes the sentence that links them. The VA will not write it for you.
Your part: tell your mental health provider about the grinding and the jaw pain at your next visit so it lands in your VA record, and work through the four cards below before you file.

Four Things That Decide a Jaw Disorder Rating
Code 9905 is a numbers code. The rater does not weigh how much it hurts in the abstract. She reads millimeters off the exam report and checks whether a physician restricted your diet. Get those two things into the record and the rating follows the chart.
Here is the trap: a quick exam on a good day. Under 38 CFR §4.7, when your condition falls between two levels, the higher one is assigned if your disability more nearly approximates it, but only if the measurements show it.
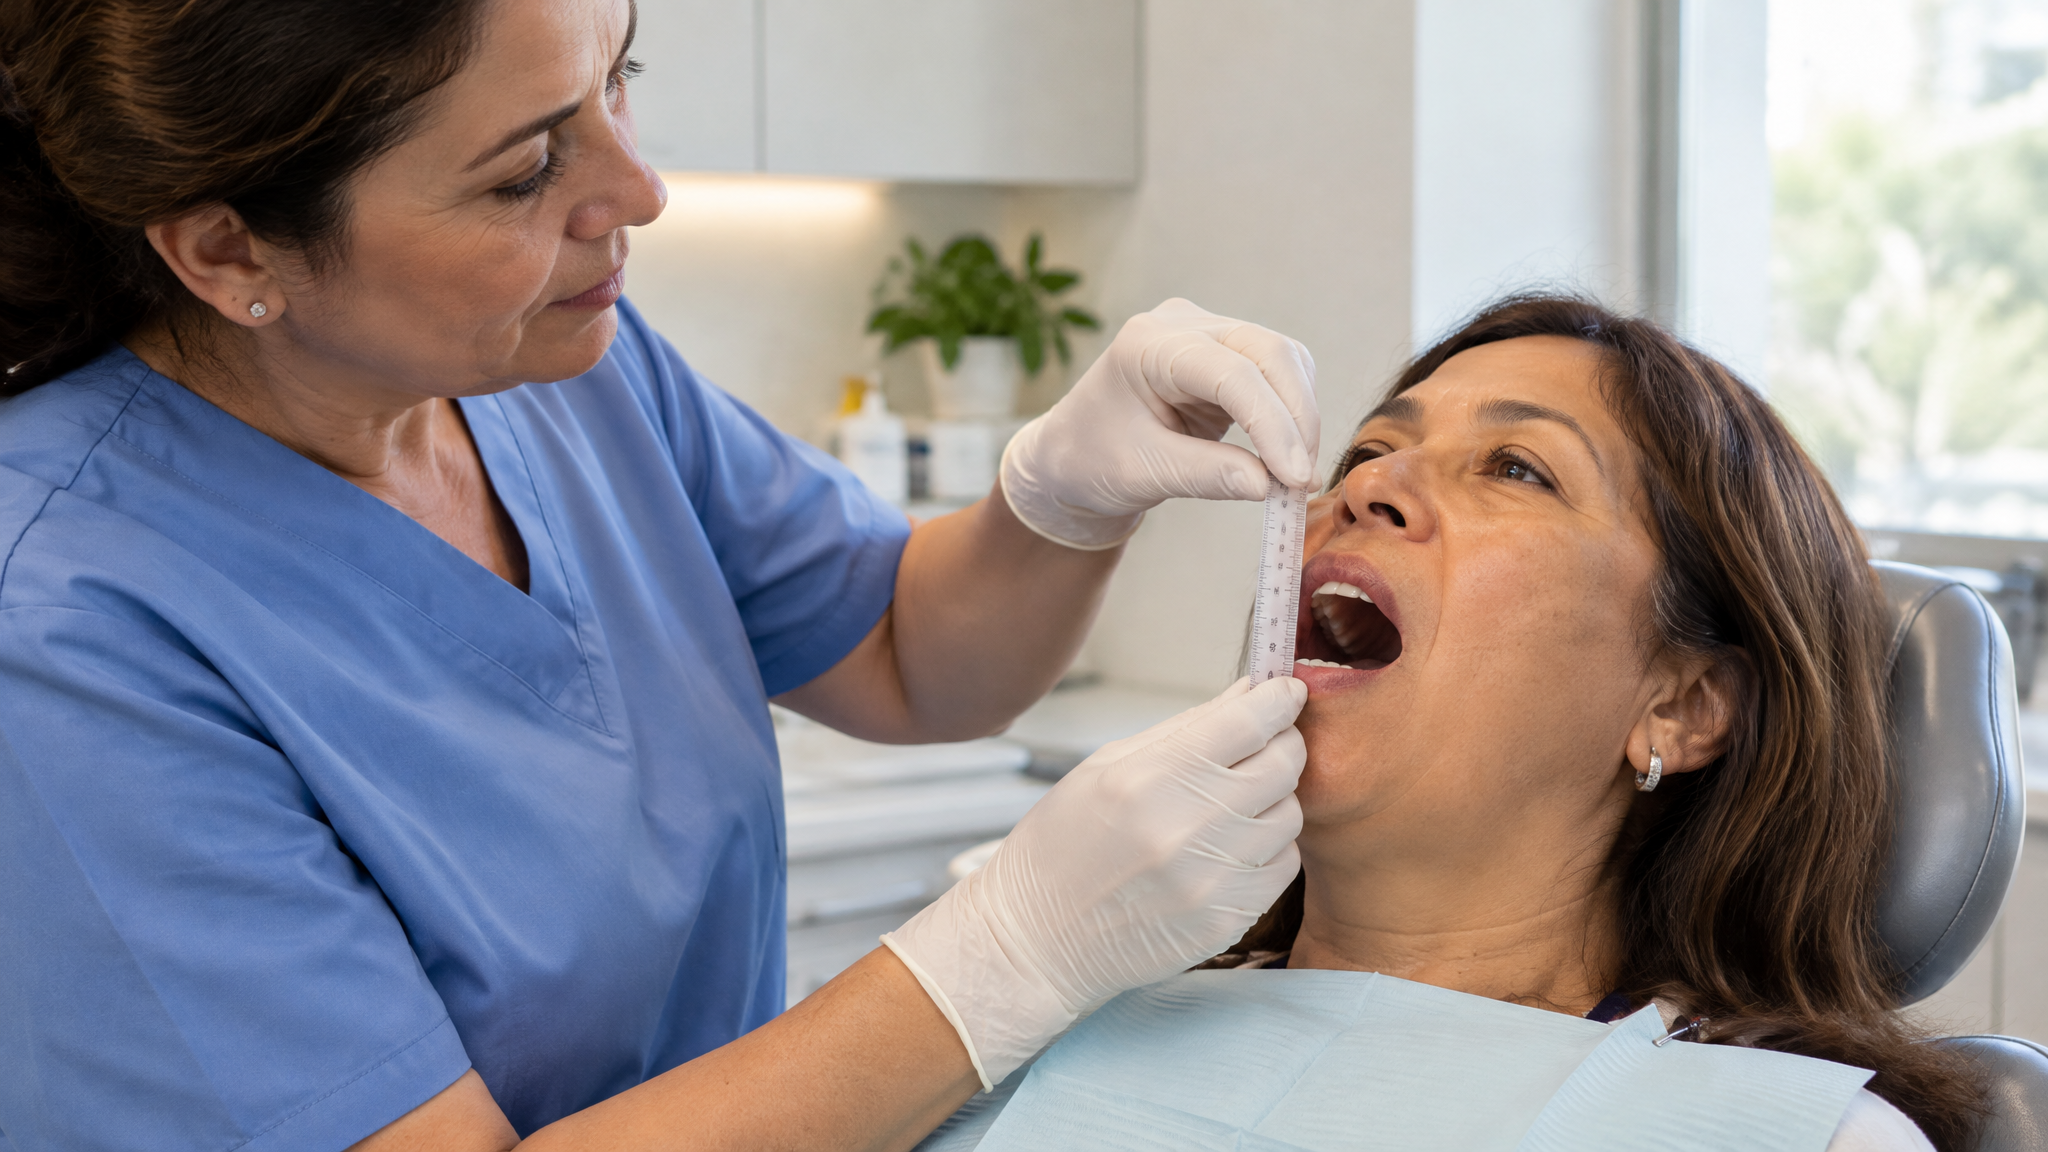
Get the Opening Measured in Millimeters
Under 38 CFR §4.150, diagnostic code 9905, the rating is driven by your maximum unassisted vertical opening, measured between the upper and lower front teeth. Normal is 35 to 50 millimeters. From 30 to 34 millimeters the base rating is 10 percent, from 21 to 29 it is 20 percent, from 11 to 20 it is 30 percent, and from 0 to 10 it is 40 percent, before any diet restriction is counted. Here is the trap: an examiner who writes limited opening without a number has given the rater nothing to rate. Your part: make sure the exam records the opening in millimeters, and tell the examiner when your jaw is at its worst.

Your Diet Can Raise the Rating, If a Doctor Writes It Down
The same code raises the rating when you are restricted to mechanically altered foods, meaning food that has been blended, chopped, ground, or mashed. The schedule recognizes four levels: full liquid, puree, soft, and semi-solid. With 30 to 34 millimeters of opening, a soft and semi-solid diet rates 20 percent and a full liquid and puree diet rates 30 percent. At the far end, 0 to 10 millimeters with restriction to all mechanically altered foods rates 50 percent. Here is the trap: the rule requires the restricted diet to be prescribed or verified by a physician. Eating soup because it hurts is not enough on your word alone. Your part: ask your provider to put the diet in your treatment notes.
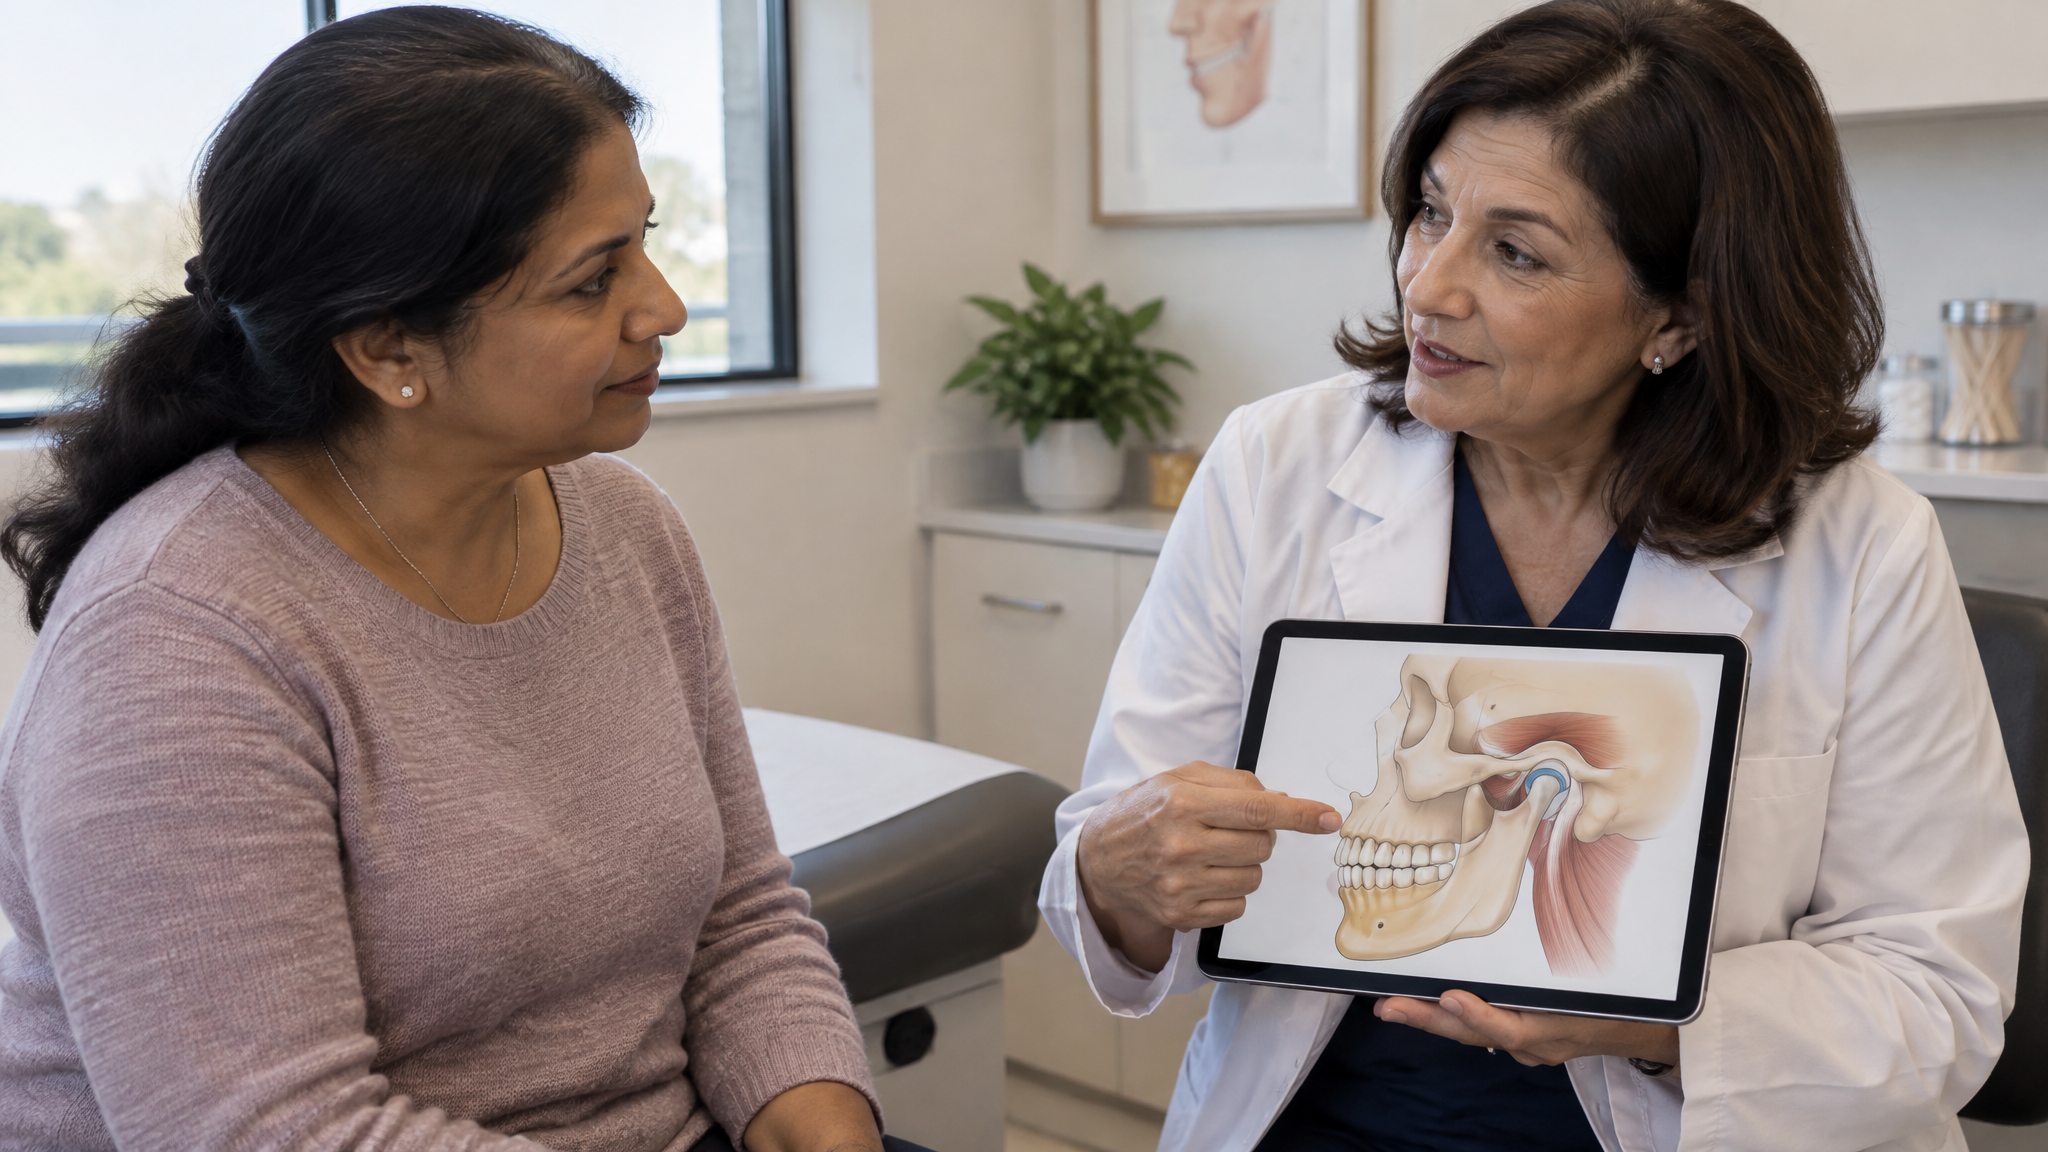
Side to Side Is a Separate Measurement, Not an Extra Rating
Code 9905 also rates lateral excursion, how far the jaw slides side to side. From 0 to 4 millimeters it rates 10 percent. A note in §4.150 says the rating for limited opening and the rating for limited lateral excursion are not combined, so you get the higher of the two, not both. Here is the trap: if your opening is near normal but your jaw barely moves sideways, the lateral number is your rating, and an exam that skipped it leaves you at zero. Your part: ask that both measurements be taken. Because the jaw is a joint, painful motion counts too under 38 CFR §4.59, and Burton v. Shinseki, 25 Vet. App. 1 (2011), held that rule is not limited to arthritis.

The Night Guard Is Evidence
A dentist who fits you for a night guard has documented grinding. Cracked or worn teeth, jaw pain on waking, and headaches at the temples tell the same story. Here is the trap: those notes live in a private dental office, and the VA rater will never see them unless you send them or identify the dentist so the VA can request them under 38 CFR §3.159(c)(1). The claim itself is secondary under 38 CFR §3.310: your service-connected PTSD, anxiety, or depression caused or worsened the clenching and grinding that damaged the joint. Your part: get the dental records, then ask a provider for a nexus opinion that explains that pathway in plain words, at least as likely as not.
More Women Veteran Guides
Each guide below covers one part of a woman veteran's claim in depth, with the regulations, the traps, and your part spelled out.
 You are here
When It Changed You: Her Mental Health Claim
MST secondary conditions, eating disorders, peer support, mental health care as evidence, discharge after MST, the 50 percent floor, and who sees your claim.
You are reading this guide




