

Special Monthly Compensation, Loss of Use, Aid & Attendance, Housebound
Compensation beyond the rating schedule for severe losses, daily-help needs, and confinement to home, the most under-claimed benefit in the system
Special Monthly Compensation exists because some disabilities are more than a percentage can capture. It pays above and beyond the regular rating schedule, on top of 100%, on top of TDIU, for losses like anatomical loss or loss of use of a hand or foot, for needing someone to help you get through the day, or for being confined to your home. The problem is that SMC is not a checkbox on the standard application. It arises from the combination and severity of conditions you already have, and the VA is supposed to infer it but frequently does not. Reviewing an existing award for missed SMC is one of the highest-value things an advocate can do.
The Diagnostic Codes
Conditions Rated In Special Monthly Compensation (SMC)
These are the codes the VA will actually stamp on a decision in this group. The code you are granted under decides which formula is used, and that decides your percentage. Special Monthly Compensation (SMC) is highlighted below.

Before Anything Gets Rated
What The VA Is Actually Looking For, And What Service Connection Really Means
Before the VA ever opens the rating schedule, it asks one question: is this disability the government’s responsibility? That is what “service connection” means. It is not a diagnosis, it is not sympathy, and it is not a reward for having served. It is a legal finding that a current, diagnosed disability is linked to something that happened to you in uniform. Percentages come later. If service connection is not established, there is nothing to rate and the claim is denied, no matter how bad the special monthly compensation (smc) is.

For Special Monthly Compensation (SMC) Specifically
SMC is not on the rating schedule, so the VA is looking for specific qualifying losses, not percentages: loss or loss of use of a hand, foot or creative organ (SMC-K), a single 100% disability plus another 60% (housebound, SMC-S), or the need for the regular aid and attendance of another person (SMC-L), evaluated against the daily-function tests in §3.352(a). The catch is that the VA almost never develops SMC on its own, the qualifying loss has to be named and the math has to be run. A review of existing ratings for missed SMC is one of the highest-value things an advocate does.
The three elements the VA must find. All three. Every time.
These come out of Caluza v. Brown and Shedden v. Principi, and they are the checklist a rating officer works through on your file. Miss one and the claim fails on that element alone.
A current, diagnosed disability
A doctor has to have written a diagnosis in a medical record, A veteran rated 100% for PTSD plus 40% for a right knee with severe limitation of flexion and 20% for left knee finds that the right knee has deteriorated to the point where he cannot bear weight or maintain balance, effective loss of propulsion. Under §3.350(a)(2), the remaining function is no better than a prosthesis. The advocate files for SMC-L for loss of use of a foot, and the veteran also qualifies for SMC-S (housebound) because he has a single 100% rating plus 60% additional, an entitlement the VA should have inferred years ago.. Symptoms by themselves are not a disability the VA can rate. Saunders v. Wilkie held that pain causing functional impairment can be a disability, but you still need a clinician to document it as diagnosed and impairing. The diagnosis must exist now, during the claim period, not only years ago.
An in-service event, injury, illness or aggravation
Something in service had to have happened, an injury, an exposure, a documented sick call, or steady wear over a career. It does not have to be one dramatic moment and it does not have to be spelled out in your service treatment records: buddy statements, unit records, performance evaluations and your own competent lay testimony can establish it.
A medical nexus linking the two
A qualified medical opinion that says the current diagnosis is at least as likely as not related to the in-service event. That phrase matters: at least as likely as not means 50 percent or better. Under 38 C.F.R. §3.102, when the evidence is evenly balanced, the benefit of the doubt goes to you and the claim must be granted.
The five ways service connection is established
Most veterans only know the first one. The other routes are lower-effort paths to the same grant, and the secondary route is the one most often left on the table.
Direct, 38 C.F.R. §3.303(a)
The injury or disease began in service and never went away. The classic route: three elements, one nexus opinion.
Chronicity and continuity, §3.303(b)
A chronic condition shown in service, plus continuity of the same symptoms from separation to now, can establish the link without a formal nexus opinion. Your own testimony about symptoms you can observe is competent evidence.
Presumptive, §3.307 and §3.309
Certain chronic diseases are presumed service connected if they manifest to a compensable degree within a set window after separation. You do not have to prove causation at all.
Secondary, §3.310(a) and (b)
A disability proximately due to, or aggravated by, an already service-connected condition is itself service connected. This is how A veteran service-connected for bilateral peripheral neuropathy develops such severe loss of sensation and motor function in both feet that balance and propulsion are effectively gone. The neuropathy is already service-connected, the loss of use is a natural progression, not a new condition. Filing for SMC-L based on loss of use of both feet requires only documenting that the §3.350(a)(2) prosthetic-comparison standard is met. get on the rating sheet.
Aggravation of a pre-service condition, §3.306
If you entered service with a condition and service made it permanently worse, the increase is compensable. The VA must rebut the presumption of soundness by clear and unmistakable evidence, a bar it frequently fails to meet.
VA medical care, 38 U.S.C. §1151
An additional disability caused by VA treatment, surgery, or a failure to diagnose is compensated as if it were service connected.
The bottom line, there is no way around this
No diagnosis, no rating. It has to be chronic. It has to cause impairment.
Without a diagnosis, the VA will not rate your claim.
SMC does not have a single diagnostic code the way a musculoskeletal condition does, the VA needs a documented functional finding in the record that maps to a specific §3.350 threshold, such as a physician's statement that the veteran cannot perform the prosthetic-equivalent function of a hand or foot, or cannot perform activities of daily living without regular assistance. Veterans lose this element because their records show a diagnosis and a schedular rating but no clinician has ever written the functional language the statute actually requires, 'loss of use,' 'need for aid and attendance,' or 'substantially confined to home and immediate premises.' Without that language tied to service-connected disabilities, the VA has no hook to hang the SMC finding on.
The condition must be chronic.
SMC eligibility based on aid and attendance or housebound status requires that the functional limitations be shown as a continuing, not episodic, condition, a single hospitalization note or one bad day in the record is not enough to establish the ongoing need the statute contemplates. The record needs to show a documented history of persistent inability to perform daily functions or persistent confinement, ideally through recurring treatment notes, home health records, caregiver statements, or a VA examination that addresses the longitudinal picture. A veteran whose file shows only acute episodes without a chronic pattern will lose the SMC analysis even if the underlying disabilities are severe.
It must cause actual impairment.
SMC impairment is not measured on the 0-to-100 schedular scale, it is a binary threshold determination: either the functional loss meets the statutory standard or it does not, and there is no partial credit. Under §4.1 and §4.10, the rating must reflect the actual functional impairment, but for SMC the question is whether the veteran crosses the specific line drawn by §1114 and §3.350, such as whether the hand is effectively as useless as if it had been amputated at the wrist. The zero-percent trap here is a veteran who has a service-connected condition that causes qualifying functional loss but whose C&P examiner never applied the prosthetic-comparison standard or the aid-and-attendance criteria, leaving the record silent on the threshold question and the SMC tier unawarded.
What this means for you before you file: Before you file or request a review, get a physician's statement that uses the exact statutory language, loss of use, need for aid and attendance, or substantially housebound, tied explicitly to your service-connected disabilities, and pull your existing rating decision to check whether the VA ever ran the SMC analysis at all. Mauerhan v. Principi confirms the symptom lists in §4.130 are examples, not requirements, you do not need every listed symptom, and unlisted symptoms showing equivalent impairment support a higher rating. Clemons v. Shinseki requires the VA to consider all mental diagnoses the evidence raises, not just the one you named on the form.
The Percentages
SMC Rate Levels, 38 U.S.C. §1114 / 38 CFR §3.350
SMC is paid at statutory fixed rates, not as a percentage. Each level represents a specific type and severity of loss, and multiple levels can apply simultaneously.

SMC-K
Loss of use of a creative organ, one hand, or one foot: a flat additional monthly payment on top of existing compensation. Includes erectile dysfunction, anatomical loss, blindness in one eye (light perception only), and deafness in both ears. Multiple SMC-K awards can stack.
SMC-L
Aid and attendance or loss of use of both feet, or one hand and one foot, paid when the veteran needs regular help from another person for daily living, is permanently bedridden, or has anatomical loss/loss of use of two extremities. Also covers blindness in both eyes with 5/200 visual acuity or less.
SMC-M/N
Higher-level combinations: progressively higher rates for more severe losses, such as loss of use of both hands, or blindness plus loss of use of a hand or foot. Each additional qualifying loss moves the veteran to a higher level.
SMC-O/R
The highest levels: multiple anatomical losses, or the need for regular aid and attendance at the R.1 rate, with an even higher R.2 rate for veterans requiring a higher level of skilled personal care. These represent the most severe disability combinations.
SMC-S
Housebound: either substantially confined to the home due to service-connected disability, OR a single service-connected disability rated 100% (or TDIU based on one disability) plus additional disabilities independently rated 60% or more. The second path is purely arithmetic and frequently missed.
Service Connection
Advice from the Advocate
This is where I stop explaining the rules and tell you how I would build your Special Monthly Compensation (SMC) claim if you were sitting across my desk. Read the causation notes below twice. The VA will not connect the dots for you, even though 38 CFR 3.159 says it has a duty to assist. Your job is to put the in-service event, the current diagnosis and the medical link on paper, then make the examiner deal with all three.
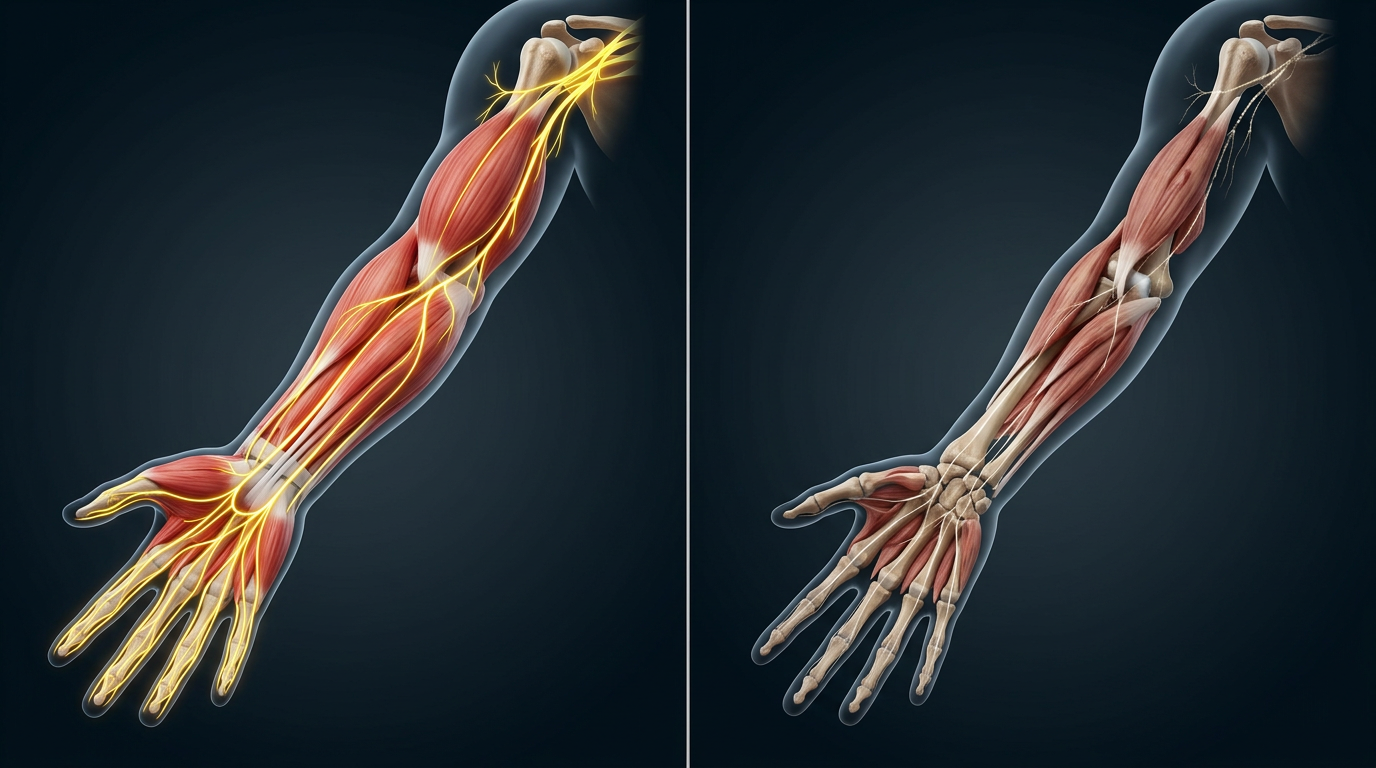
The advocate's notes on causation, Special Monthly Compensation (SMC)
The separate arguments that decide this code: where the VA will attack, the regulation that answers it, and the evidence that closes the gap.
1Entitlement based on existing ratings
Many SMC entitlements arise automatically from existing service-connected conditions, the veteran does not need a new nexus, just a review of what is already in the file. SMC-K for erectile dysfunction secondary to a prostate condition, SMC-S from rating arithmetic, and aid and attendance from the combined effect of multiple service-connected disabilities are all examples of SMC that should have been inferred but was not.
2Loss of use as secondary progression
When a service-connected condition progresses to loss of use under the §3.350(a)(2) standard, function no more useful than a prosthesis, the SMC entitlement is secondary to the already-established condition under §3.310. No new nexus is needed beyond documenting that the loss of use arose from the service-connected disability.
3Aid and attendance from combined disabilities
Aid and attendance needs arising from the combined effect of multiple service-connected conditions are evaluated under §3.352(a). A physician statement documenting the specific daily-help needs, dressing, hygiene, feeding, toileting, hazard protection, and attributing them to service-connected disabilities establishes the entitlement.
Exposure & Aggravation
Who Qualifies for SMC, It Is Not Just Amputees

The VA wants an in-service event, and most veterans think that means one dramatic injury. It does not. Years of duty that wore the body down count too, and under 38 CFR 3.306 a condition service made worse can still be connected. Find yourself in the list below, then put that duty in writing with dates, units and names. The board only weighs what you put on paper.
How veterans pick this up in uniform, Special Monthly Compensation (SMC)
Special Monthly Compensation is not limited to veterans with visible anatomical losses. The prosthetic-comparison standard under §3.350(a)(2) covers any veteran whose remaining function in an extremity is no better than a prosthesis would provide, including veterans with severe neuropathy, paralysis, contractures, or degenerative conditions. SMC-K reaches any veteran with erectile dysfunction secondary to a service-connected condition (prostate cancer treatment, spinal cord injury, medication side effects, PTSD-related sexual dysfunction). SMC-S reaches any veteran with a 100% rating plus 60% additional, a threshold many veterans cross without anyone checking the math. The common thread is not the type of injury but whether anyone has reviewed the existing file for missed entitlements.
- Combat injuries resulting in anatomical loss or severe functional loss of extremities
- Blast exposure, IED injuries, or traumatic amputations during deployment
- Service-connected conditions whose combined effect confines the veteran to the home
- Progressive neurological or musculoskeletal conditions originating in service that eventually produce loss of use
- Service-connected conditions causing erectile dysfunction or loss of reproductive function
Who is most prone to it
Any veteran with severe service-connected disabilities, particularly those at or near 100%, those with TDIU, and those with conditions causing loss of function in extremities or organs, is a candidate for SMC review. The benefit is under-claimed not because veterans do not qualify, but because the VA does not infer it and most representatives do not look for it.
The Symptoms
What Special Monthly Compensation (SMC) Actually Feels Like
Read this list the way the examiner will. Every symptom you live with but never report is a symptom the VA treats as if it does not exist. The rating schedule pays for how Special Monthly Compensation (SMC) affects your daily life and your work, so the details matter. Check off what matches your day, tell your doctor in those words, and make sure it lands in your treatment record before the exam.

- Inability to grasp objects or manipulate with the hand, loss of use measured against the prosthetic-comparison standard
- Loss of balance and propulsion in the foot, foot drop, inability to bear weight, or effective loss of walking ability
- Erectile dysfunction or loss of reproductive function (loss of use of a creative organ qualifying for SMC-K)
- Need for daily personal assistance, bathing, dressing, eating, toileting, or protection from environmental hazards
- Substantial confinement to the home and immediate premises due to service-connected disabilities
- Blindness, near-blindness, or deafness meeting specific statutory thresholds
- Multiple anatomical losses or losses of use across extremities qualifying for higher SMC levels
How this one is rated
Special Monthly Compensation is not rated on a percentage schedule. It is paid at statutory fixed rates under 38 U.S.C. §1114 and 38 CFR §3.350 for specific severe losses. SMC-K is a flat additional amount for loss of use of a creative organ, one hand, or one foot. SMC-L is paid for aid and attendance or loss of use of multiple extremities. SMC-S is paid for housebound status or specific rating combinations. Higher levels (M through R) apply for progressively more severe combinations of losses. The amounts exceed the 100% schedular rate and can be paid on top of any existing rating.
What you are measured against
Loss of use is measured against the prosthetic-comparison standard of §3.350(a)(2): whether the remaining function is no more useful than that which would be provided by an amputation stump with a suitable prosthesis. Aid and attendance is measured against the §3.352(a) factors: ability to dress, maintain hygiene, feed oneself, attend to nature, and avoid environmental hazards. Housebound status is measured as substantial confinement to the dwelling.
Each One On Its Own Page
Secondary Conditions, Aggravated or Caused by a Current Service-Connected Condition
Under 38 CFR §3.310(a), a disability that is proximately due to a service-connected condition is service-connected in its own right, and under §3.310(b), so is any additional disability caused when a service-connected condition aggravates a problem you already had. Each condition below is a separate evaluation with its own diagnostic code and its own percentage. They do not fold into the special monthly compensation (smc) rating, they stack on top of it. A veteran who claims only the primary condition leaves these ratings on the table.

Depression & Mental Health from Loss of Independence
The psychological impact of losing the ability to care for yourself, losing mobility, or being confined to your home is profound and separately ratable under §4.130 (DC 9434 for major depressive disorder, DC 9400 for generalized anxiety). Loss of independence, role identity, and social participation are well-documented pathways to psychiatric conditions. These secondary mental-health claims can significantly increase the combined rating and may themselves contribute to housebound or aid-and-attendance qualification.

Daily Assistance & Service Animal Support
The reality of aid and attendance extends beyond what the §3.352(a) factors list. Service animals, adaptive equipment, home modifications, and the constant presence of a caregiver are all part of the daily picture. Documenting the full scope of assistance needed, including tasks the veteran has given up entirely because no one is available to help, strengthens both the aid-and-attendance finding and any secondary claims for mental-health impact.

Caregiver Burden & Family Impact
The caregiver's perspective is powerful evidence for aid and attendance. A written statement from the spouse, family member, or professional caregiver describing the specific daily tasks they perform, the hours spent, and the veteran's inability to function without that help documents the §3.352(a) factors from an observer's viewpoint. Caregiver statements often capture details the veteran minimizes, difficulty with hazard awareness, medication management, and personal hygiene, and are harder for a rater to dismiss.
Accredited Claims Agent #45147
Ready To Get This Rated Correctly?
You have read how the VA rates Special Monthly Compensation (SMC). Now the question is whether your file proves it. We represent veterans on a No Win, No Fee basis: 20% Direct-Pay paid by the VA from back pay, or 30% High-Complexity, and you owe nothing for representation if your rating does not increase. If you only need the roadmap, the Mission 5 Brief is a separate $750 flat fee. You bring the records, we build the argument.
Special Monthly Compensation (SMC), In Detail
Special Monthly Compensation (SMC), Service Connection In Depth
Here is each claimable condition in this group on its own terms, what it is, what service did to it, and what the VA requires before it will connect it.

Special Monthly Compensation, Loss of Use, Aid & Attendance, Housebound
Special Monthly Compensation exists because some disabilities are more than a percentage can capture. It pays above and beyond the regular rating schedule, on top of 100%, on top of TDIU, for losses like anatomical loss or loss of use of a hand or foot, for needing someone to help you get through the day, or for being confined to your home. The problem is that SMC is not a checkbox on the standard application. It arises from the combination and severity of conditions you already have, and the VA is supposed to infer it but frequently does not. Reviewing an existing award for missed SMC is one of the highest-value things an advocate can do.
You are reading this page now
The C&P Exam
What To Expect At The Special Monthly Compensation (SMC) Exam
This is the encounter your rating is built on. The examiner has a checklist and a limited window, what follows is exactly what happens in that room, so none of it surprises you.
Clinical Section, What To Expect at the Exam
Special Monthly Compensation Examination, Loss of Use / Aid & Attendance
What the examiner must document and what the veteran must say
The SMC examination asks a fundamentally different question than a standard C&P exam. It is not asking how limited you are on a percentage scale, it is asking whether you would be equally well served by an amputation with a prosthesis (loss of use), whether you need another person to help you through the day (aid and attendance), or whether you are effectively confined to your home (housebound). These are specific legal findings with specific regulatory language, and the examiner must state them in those terms. Most do not unless the question is put to them directly.
Condition
Special Monthly Compensation (SMC), §1114 / §3.350
Governing questionnaire
Aid and Attendance / Housebound Disability Benefits Questionnaire
Click the form number to open the official questionnaire on VA.gov.
01In The Room
What happens during the exam
The tests and maneuvers for this condition
- Manual muscle testing graded 0–5 for each affected extremity, both sides
- Deep tendon reflexes graded 0–4+ in affected and unaffected limbs
- Sensory mapping: light touch, pinprick, proprioception across dermatomes
- Limb circumference measurement at standardized landmarks for atrophy documentation
- Functional testing: grip strength, pinch strength, standing balance, gait assessment
- Activities of daily living assessment: dressing, hygiene, feeding, toileting, hazard awareness
What gets measured, and to what number
Muscle strength (0–5 scale)
Manual muscle testing in every affected myotome, both sides, with comparison to document asymmetric weakness or complete loss
Limb circumference
Measured in centimeters at a fixed landmark bilaterally to document muscle atrophy, marked atrophy supports higher-level findings
Sensory testing
Light touch, pinprick, proprioception, and vibration testing to document completeness of sensory loss in the affected extremity
Functional capacity
Specific assessment of grasping, manipulation, balance, propulsion, and ability to perform activities of daily living independently
Aid and attendance checklist
Each §3.352(a) factor assessed individually: dressing, hygiene, feeding, toileting, and hazard protection
02Orientation
What to expect during this exam
What makes this exam different from every other C&P exam
1Prosthetic-comparison finding
For loss of use, the examiner must make an explicit finding on whether the remaining function of the extremity is no more useful than that which would be equally well served by an amputation stump with a suitable prosthetic appliance, this is the exact regulatory language of §3.350(a)(2), and it must appear in the report.
2Balance and propulsion (foot)
For loss of use of a foot, the examiner must document whether balance and propulsion are effectively lost, not merely reduced. Can the veteran stand without falling? Can the veteran walk without dragging or circumducting the affected leg? Is the foot functionally a dead weight?
3Grasping and manipulation (hand)
For loss of use of a hand, the examiner must document whether grasping and manipulation are effectively lost. Can the veteran pick up and hold a cup? Turn a doorknob? Button a shirt? Write with a pen? If these are functionally impossible, the prosthetic-comparison standard is met.
4Aid and attendance factors
For aid and attendance under §3.352(a), the examiner must address each factor individually: ability to dress/undress, maintain ordinary cleanliness, feed oneself, attend to wants of nature, and protect from daily hazards. A blanket statement is not sufficient, each factor must be assessed.
5Housebound confinement
For SMC-S housebound, the examiner documents either substantial confinement to the dwelling and immediate premises, or verifies that the veteran has a single 100% rating plus additional disabilities independently ratable at 60% or more, the purely arithmetic path.
See it before you sit in the room
03Preparation
Know your symptoms and secondary factors
What the report must actually say about special monthly compensation (smc), §1114 / §3.350
- I cannot grip or hold objects with my [affected] hand, the function is no better than if the hand were amputated and replaced with a prosthesis
- I cannot maintain my balance or push off with my [affected] foot, I would be equally well served by a prosthetic
- I need help every day with [bathing/dressing/eating/toileting/medications], I cannot do these safely on my own
- I am effectively confined to my home because of my service-connected disabilities
- I have erectile dysfunction caused by [service-connected condition], I am requesting SMC-K for loss of use of a creative organ
- Please document the prosthetic-comparison finding in the regulation's own language for each affected extremity
Pain level, frequency, lost work and functional loss, how to say them

Loss of Use, Hand
The prosthetic-comparison standard for a hand is loss of grasping and manipulation, this specific finding triggers SMC-L
Describe every task you cannot perform with the affected hand: gripping a cup, turning a doorknob, buttoning clothing, holding a pen, picking up coins. Demonstrate at the exam. The examiner needs to see that remaining function is no better than a prosthesis.
"I cannot close my fingers around a cup or hold it without dropping it. I cannot turn a doorknob, button my shirt, or hold a pen to write. The hand is there but it does not work, a prosthetic hand would give me the same or better function than what I have."

Loss of Use, Foot
The prosthetic-comparison standard for a foot is loss of balance and propulsion, this finding triggers SMC-L or SMC-K
Describe inability to stand without falling, inability to push off when walking, foot drop that prevents clearing the ground, and any assistive devices required. The foot does not have to be amputated, it just has to be functionally equivalent to a prosthesis.
"My foot drags on the ground when I walk. I cannot push off or maintain my balance. I have to use a brace just to keep the foot from dropping, and even with the brace I cannot walk safely without a cane or walker. A prosthetic foot would work as well or better."

Aid and Attendance Needs
Documenting each §3.352(a) factor individually builds the case for SMC-L, blanket statements are insufficient
Walk through your entire day and identify every task where you need help: getting out of bed, bathing, dressing, preparing meals, taking medications, using the bathroom, and navigating hazards. Name the person who helps you and how many hours per day they provide care.
"My wife helps me get dressed every morning because I cannot manage buttons or zippers. She prepares all my meals because I cannot safely use the stove. She manages my medications because I forget doses. She helps me in and out of the shower because I fall without support. Without her I could not get through a day."

Housebound Status
SMC-S has two paths, confinement or rating arithmetic, and the arithmetic path is missed constantly
If you are substantially confined to your home, describe why: what happens when you try to leave, how far you can go, what prevents independent mobility. If your ratings include a single 100% plus 60% additional, state that, it is a purely arithmetic qualification that the VA should infer automatically.
"I rarely leave my house because my disabilities make it unsafe. When I try to go anywhere, I need someone to drive me and stay with me. I am effectively confined to my home and the few steps of my front porch. I also have a 100% rating for [condition] plus additional ratings totaling over 60%."

Multiple Losses Combined
Higher SMC levels (M through R) apply when multiple losses combine, each additional qualifying loss increases the statutory rate
If you have loss of use or anatomical loss affecting more than one extremity, or loss of use plus blindness or deafness, describe each loss separately. Higher SMC levels are cumulative, each qualifying loss moves the veteran to a higher payment tier.
"I have loss of use of both my right hand and my left foot from [conditions]. Neither extremity functions better than a prosthesis. I also need daily help with bathing, dressing, and meals. Each of these should be evaluated for the appropriate SMC level."
Secondary conditions to raise in the same appointment
Every secondary condition laid out in the Secondary Conditions section above belongs in this same appointment. Name each one out loud, tell the examiner how the primary condition caused it or made it worse, and ask that it be noted in the report. Under 38 CFR 3.310, a secondary condition the examiner never hears about is a secondary condition the VA never rates. Bring your list on paper so nothing gets left in the parking lot.
What to expect at this specific exam
- Review your existing ratings with your advocate to identify every potential SMC entitlement before the exam
- Prepare a detailed written statement listing every daily task you need help with and who provides that help
- Document how you are confined to your home, how often you leave, why you cannot leave independently, what happens when you try
- Bring a statement from your caregiver describing the specific daily assistance they provide and how many hours per day
- If you have a treating physician, request an aid-and-attendance statement on the VA form addressing each §3.352(a) factor
- List every service-connected condition and its current rating, the advocate should verify whether SMC-S arithmetic is met
04The Protocol
What procedures are required during the exam
These are not courtesies. Each comes out of the regulation or out of binding case law. Take this list in with you and tick them off as they happen.
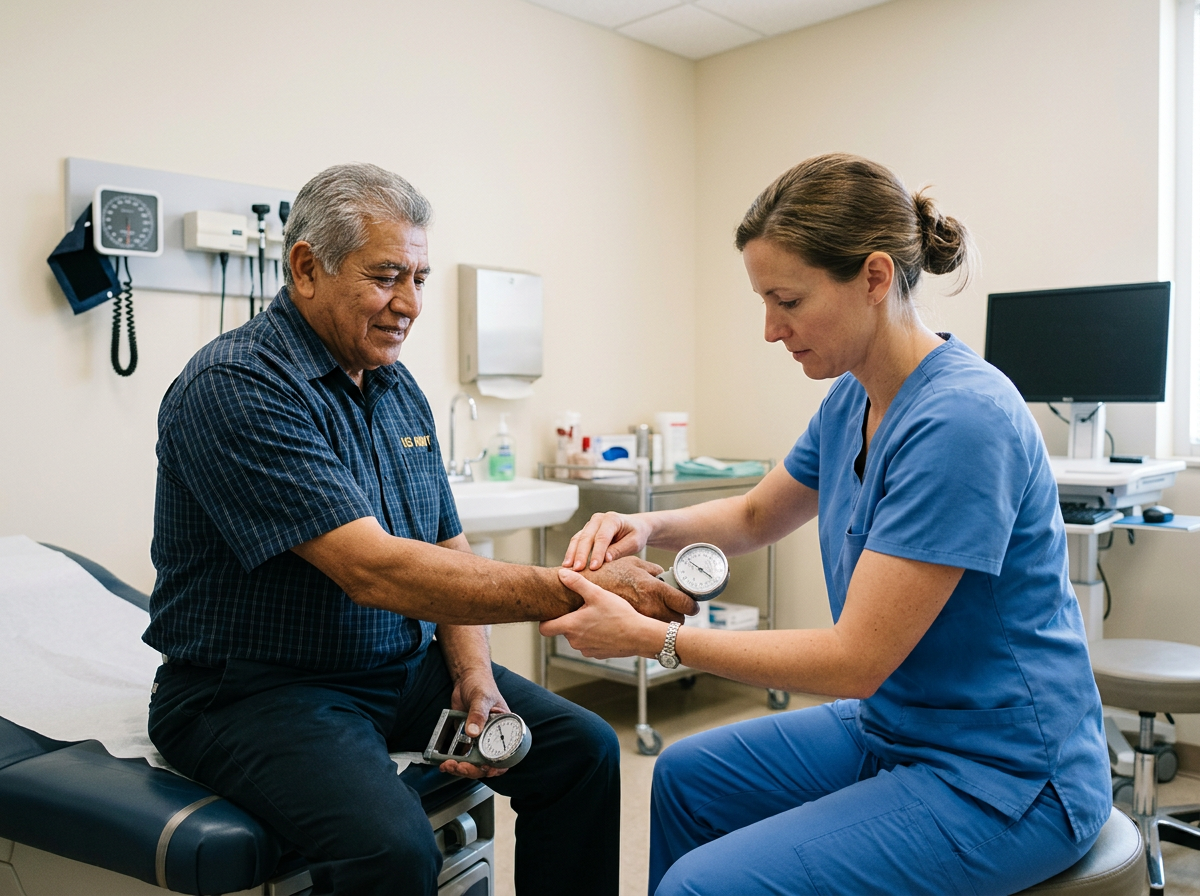
01Prosthetic-Comparison Evaluation
38 CFR §3.350(a)(2), remaining function compared to prosthetic appliance
The examiner performs a comprehensive evaluation of the affected extremity and makes the §3.350(a)(2) finding in the regulation's own language: whether remaining function is no more useful than an amputation stump with a suitable prosthetic appliance. For hands, this means testing grip strength, pinch strength, manipulation, and functional grasp. For feet, this means testing balance, propulsion, and ambulatory capacity.
This finding is the legal threshold for loss of use. Without it stated in the regulatory language, the VA rater may not make the SMC determination, even if the clinical evidence clearly supports it.
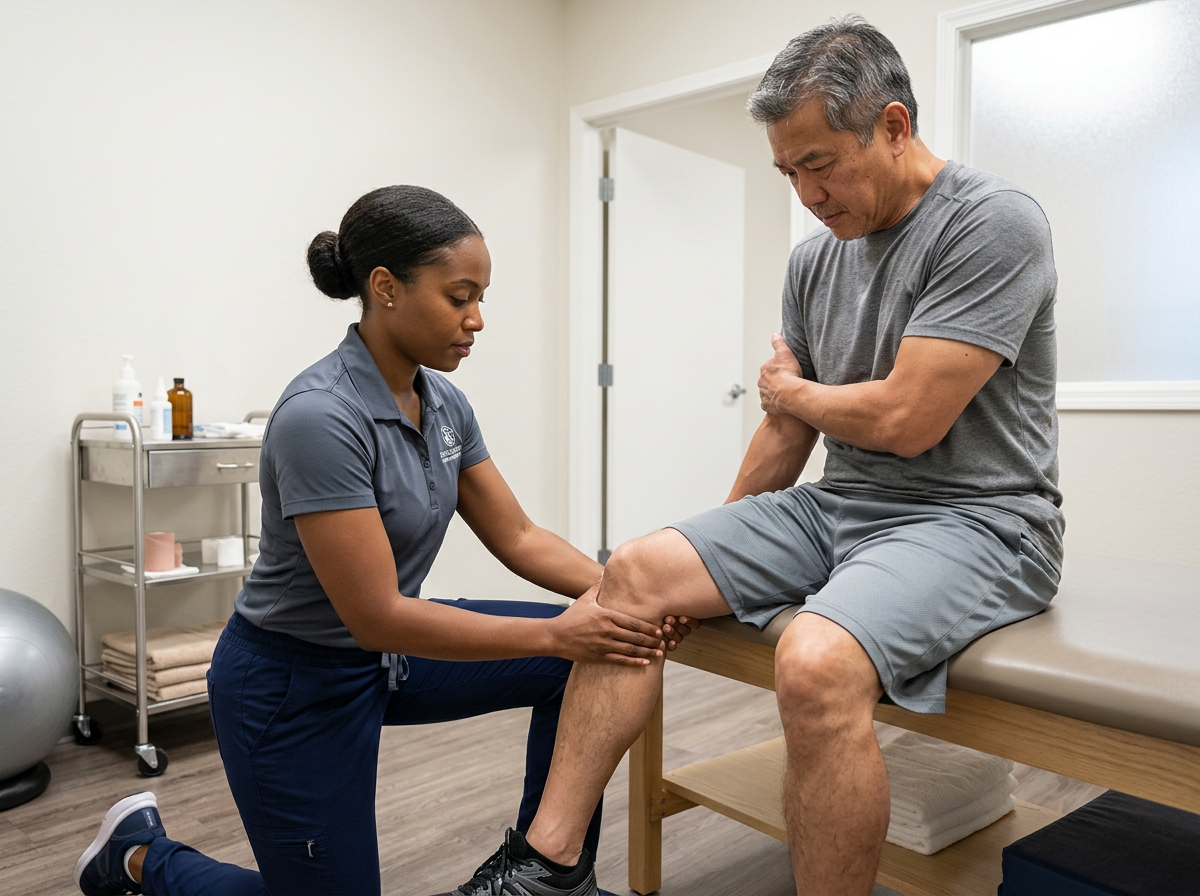
02Manual Muscle Testing & Strength Grading
38 CFR §4.124a, muscle strength and motor function assessment
The examiner grades muscle strength 0 to 5 in every affected myotome, both sides, to document the severity and symmetry of weakness. Grade 0 (no contraction) and Grade 1 (flicker only) in multiple muscle groups strongly support the loss-of-use finding. The comparison between affected and unaffected sides quantifies how much function has been lost.
Muscle strength grades provide the objective clinical evidence supporting the examiner's prosthetic-comparison finding. Severe weakness (0–2) in functional muscle groups makes the case that remaining function is no better than a prosthesis.
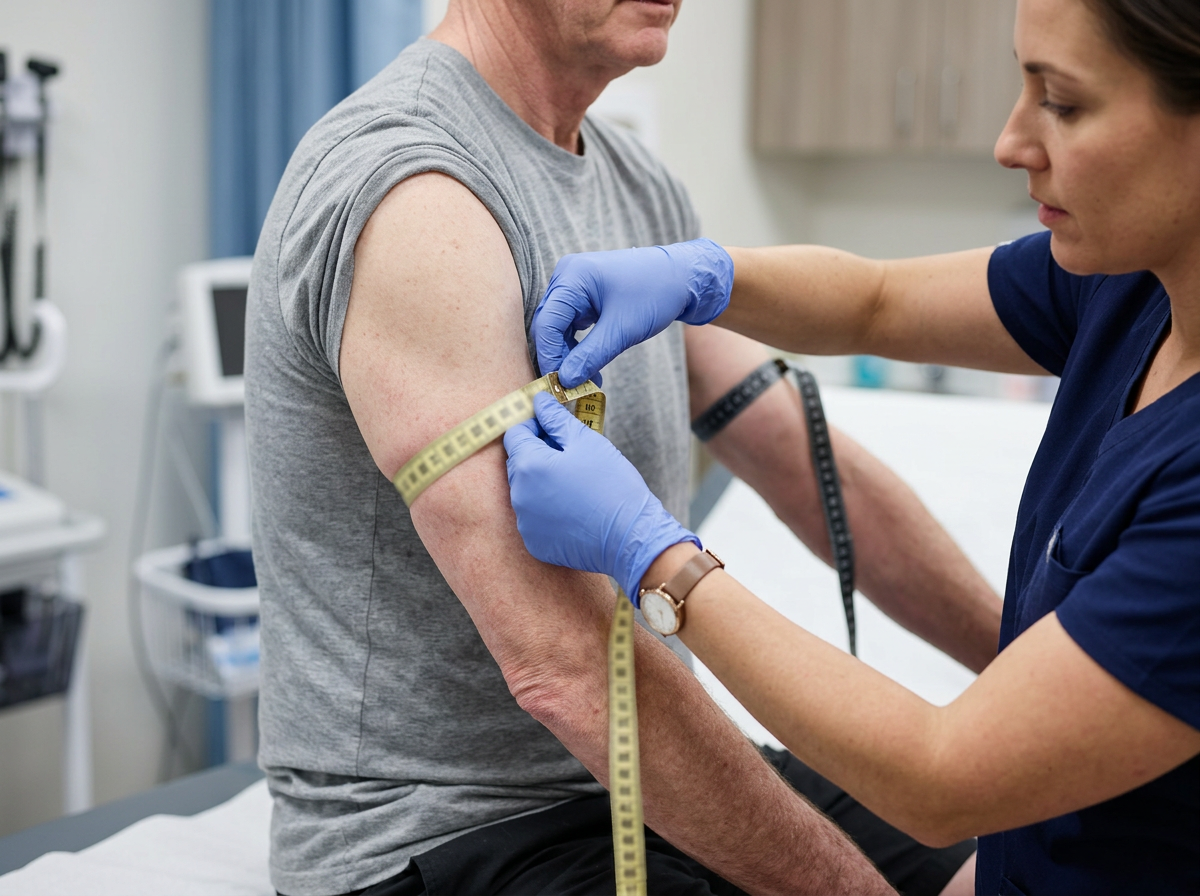
03Limb Circumference & Atrophy Documentation
38 CFR §3.350(a)(2), objective evidence supporting loss of use finding
The examiner measures limb circumference in centimeters at a standardized landmark on both sides, typically mid-thigh, mid-calf, mid-forearm, or mid-bicep. A significant difference between the affected and unaffected side documents muscle atrophy, which is the physical evidence of prolonged disuse or denervation. Marked atrophy supports higher severity findings.
Atrophy measurements provide objective, reproducible evidence of chronic functional loss. A 3+ cm difference in circumference is difficult to dispute and strongly corroborates the veteran's reported inability to use the extremity.

04Aid and Attendance Examination
38 CFR §3.352(a), aid and attendance evaluation factors
The examiner, ideally a physician who knows the veteran's daily situation, addresses each §3.352(a) factor individually: ability to dress/undress without assistance, ability to keep ordinarily clean and presentable, ability to feed oneself, ability to attend to the wants of nature, and ability to protect from hazards of the daily environment. Each factor receives a separate finding. A treating physician statement on the VA aid-and-attendance form is often more thorough than a C&P exam.
A factor-by-factor assessment is required because the VA rates aid and attendance based on the totality of limitations. A blanket statement of "needs help" is insufficient, each specific inability must be documented for the rater to make the determination.

05In-Home Housebound Assessment
38 CFR §3.350(i), housebound status: substantially confined to dwelling
For housebound claims based on substantial confinement, a VA clinician may conduct an in-home assessment to observe the veteran's actual living environment and mobility limitations. The assessment documents the veteran's ability to leave the dwelling, how far they can travel independently, what barriers exist (stairs, distance to vehicle, weather sensitivity), and whether confinement is due to service-connected disabilities.
An in-home assessment provides real-world evidence of confinement that an office-based C&P exam cannot capture. It documents the actual environment and the practical barriers that keep the veteran housebound.
05The Standard
What makes an exam adequate
Read your exam report against these. An exam that fails the standard is legally inadequate, and an inadequate exam is something you challenge rather than accept.
The range of motion has to be MEASURED, not estimated
38 CFR §4.46 states that the use of a goniometer in the measurement of limitation of motion is indispensable in examinations conducted within the Department of Veterans Affairs. An examiner who eyeballs your bend and writes a number has not complied with the regulation. This is the most common defect in a spine exam and it is the easiest one to spot from the chair.
Joints must be tested in every required condition
Under Correia v. McDonald, a joint examination for pain must, wherever possible, record active motion, passive motion, motion in weight-bearing and motion in non-weight-bearing, and where relevant, the range of the opposite undamaged joint. An exam that records one set of numbers and stops is incomplete on its face, and that incompleteness is grounds to challenge it.
Flare-ups have to be addressed, not dodged
Under Sharp v. Shulkin, when a veteran describes flare-ups, the examiner is obligated to estimate the additional loss of motion during a flare based on all the available evidence, including your own account of it. "I cannot opine without resorting to mere speculation" is not automatically acceptable; the examiner has to have actually sought the information first and explained why an estimate is impossible.
Repetitive use and functional loss must be factored in
Sections 4.40 and 4.45, and the DeLuca line of cases, require that pain, weakness, fatigability, incoordination and lack of endurance after repeated use be considered, and expressed in additional degrees of lost motion where that is feasible. Your rating is supposed to reflect what you can do on the fifth repetition and on a bad day, not just the first careful bend of the morning.
Neurological findings must be separately documented
Note (1) to the General Rating Formula requires that any associated objective neurologic abnormality be evaluated separately under an appropriate diagnostic code. If your leg symptoms were mentioned in the narrative but never tested and never assigned, the exam did not do what the schedule requires of it.
The examiner must review the record when the question requires it
Where a medical opinion on cause, aggravation or a secondary relationship was requested, the examiner is expected to review the relevant evidence and give a reasoned explanation. A bare conclusion, "less likely than not related to service" with no reasoning attached, carries little weight, and an opinion with no rationale is challengeable.
The examiner has to be qualified for the body system
The VA may use its own clinicians or a contract vendor. Either way, the examiner is expected to have the competence to evaluate the system being examined. If a spinal exam with a neurological component was performed by someone who never tested a reflex, that is a problem worth raising.
The exam has to be CURRENT
A rating is supposed to reflect your condition now. An exam performed before a documented worsening, or years before the decision, may not support the current evaluation, and you can request a new one on that basis.
06Afterward
What happens after your exam is complete
The examiner writes the report and submits it, it is reviewed for completeness, and only then does the claim move toward a rating decision. Here is what actually controls the clock.

The examiner writes and submits the report
Days 1–5 after the exam
The examiner compiles the history, the physical findings, the measurements and any testing into the questionnaire, adds any requested medical opinion, and submits it. Contract vendors typically have a turnaround requirement measured in days, not weeks.
Nothing about your claim moves while this is happening, and nothing you do speeds it up. What matters is that the report is written from notes taken in the room, which is exactly why what you said, and how the examiner recorded it, is already locked in by the time you get to your car. Request your copy now rather than later.

Quality review, and the request for clarification
Days 3–30
The report is reviewed for completeness. If it is internally inconsistent, missing a required field or missing the opinion the VA asked for, it goes back for correction or a second opinion. This is the single most common cause of a claim appearing to stall after the exam.
Understand what a finished exam actually means: it means the appointment happened, not that your claim is ready for a decision. If the reviewer finds a blank range-of-motion field, an opinion that does not answer the question that was asked, or findings that contradict each other, the file goes back out for more information. That is a normal quality control step, not a rejection of your claim, and it is not a sign that you did something wrong, but it does add weeks, and it is the reason so much of what you read online sounds like the system is broken.
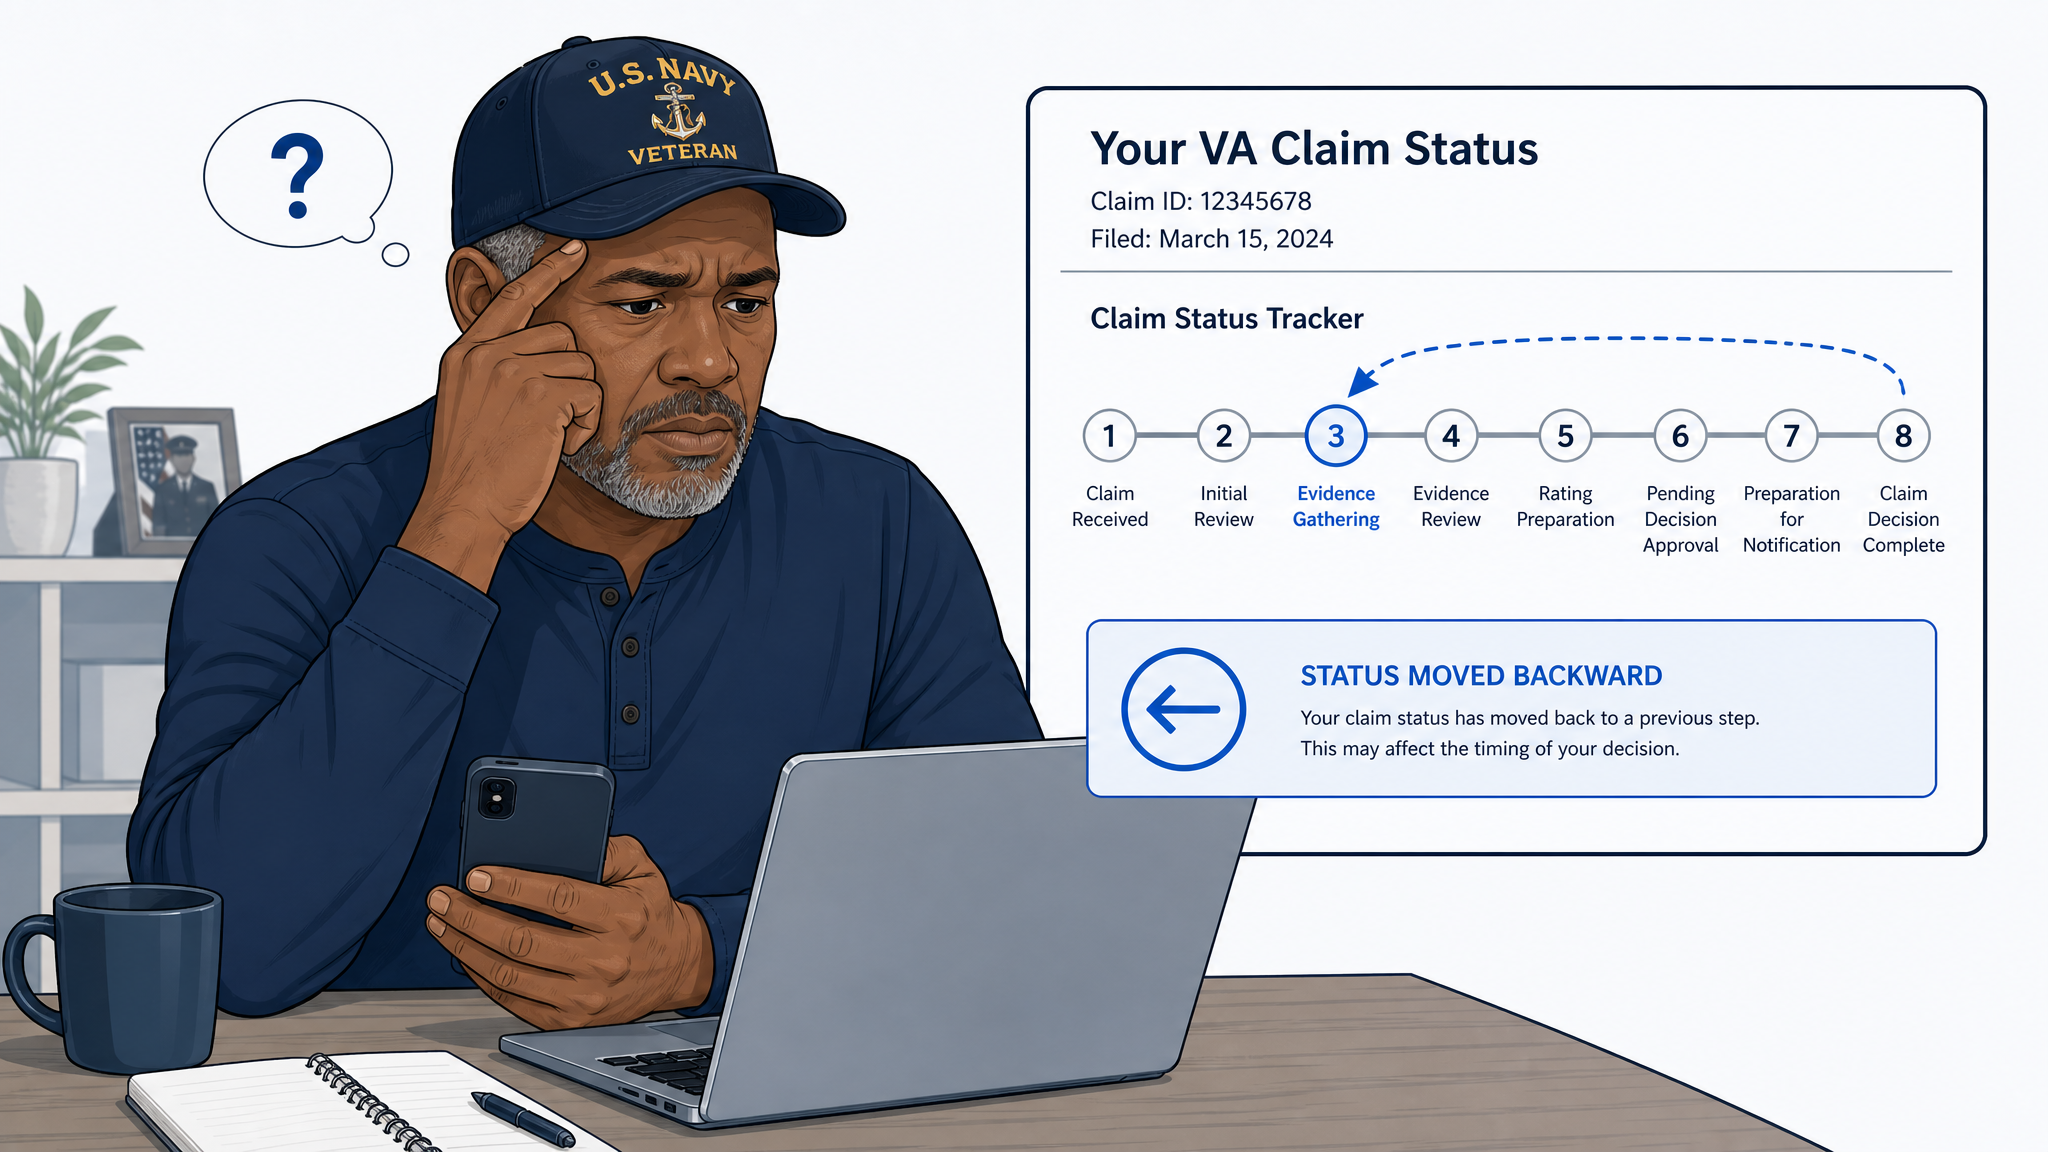
Your status tracker moves backward, and it is usually not bad news
Any time after the exam
The online tracker shows eight steps. Veterans watch it reach step 7 or 8, then find it back at step 3 or 4 a week later. That regression almost always means one thing: the file went back for additional information, most often a returned or clarified exam.
This is the number one thing veterans panic about, and it is misread constantly. The tracker is not a countdown, it is a location marker. When the VA decides it needs one more piece of evidence, a corrected exam, a clarifying medical opinion or an outstanding record, the claim is routed back to the evidence gathering step and the bar redraws itself where the file physically is. It does not mean a denial. It does not mean your case was thrown out or restarted. It does not erase anything already in the file, and it does not change your effective date. What it does mean is that something in the record was not good enough to decide on yet, which is worth knowing, because if the weak link is the exam, this is the window where a corrective statement or a private opinion from your own doctor does the most good.

Evidence gathering closes
Varies
Before anyone rates your claim, the file has to be built. This is the stretch where the Regional Office pulls together everything the decision will rest on: your service treatment records, your VA medical records, any federal records, the C&P exam report, and any private records it has requested on your behalf. The claim sits here until the VA is satisfied the record is complete enough to decide, which is exactly why a status tracker can appear to stall or slide backward at this step. You are not powerless while it sits here. Anything you put into the file yourself lands the day you send it, and every relevant record you add now is one less thing the rater can later say was missing.
A VA request to a private provider is a letter that may or may not be answered, and the VA will wait on it for weeks before moving on, sometimes without ever getting a response. A record you walk in yourself, or upload through your claim, is in the file the day you send it. So do not sit and wait to be asked. If you know a treatment record, an imaging report, a surgical note or a buddy statement exists and it matters, send it now, with a VA Form 21-4138 statement that explains in plain words what the document is and what it shows. This is also the window where a corrective statement or a private medical opinion from your own doctor does the most good, before the rater has locked in a decision, not after. Once the evidence gathering step closes, the file goes to a rating specialist, and your chance to shape the record cheaply and quickly closes with it.

Rating decision and promulgation
Typically several weeks after the last piece of evidence lands
This is the stage where your evidence finally becomes a number. A rating specialist, not the examiner, and not a doctor, takes everything in the file and applies the rating schedule to it: the exam findings, your range-of-motion measurements, your lay statements, your private records and any medical opinions. They assign a diagnostic code to each condition, pull a percentage from the schedule, set your effective date, and either grant, deny or defer each issue. The decision is then reviewed and authorized, promulgation is simply the VA’s word for making it official, and the decision letter and code sheet are generated and mailed. Where an award is made, payment follows the effective date rules, and back pay is calculated to that date.
Read the code sheet, not just the percentage. It names the diagnostic code used, the exact measurements relied on and the effective date assigned, and that is where most mistakes live. This is a human being reading a file under a production quota, and the two things that go wrong most often are a rater using the pre-repetition range-of-motion numbers instead of the worst-case figures §4.59 and §4.40 require, and a claimed condition being decided on a thin record or quietly left out. Check whether painful motion was accounted for, whether your radiculopathy was rated separately under Note (1) or folded into the spine rating, and whether every condition you claimed was actually addressed. A decision you do not read is a decision you cannot challenge, and the deadline to challenge it starts the day the letter is dated, not the day you understand it.

C&P examination is the decision letter
The day it lands in your mailbox
The envelope holds two different documents: the narrative decision letter, and the code sheet. Together they are the single most important piece of paper in your claim, because every deadline, every appeal option and every dollar of back pay is set by what is printed on them, not by what you were told at the exam.
Most veterans read one thing on that letter: the percentage. Then they either celebrate it or get angry at it, and file it in a drawer. That is the mistake. The percentage is the conclusion; the reasons section is the reasoning, and the reasoning is what you attack. It tells you which diagnostic code the rater used, which range-of-motion figures they relied on and which they ignored, whether painful motion under §4.59 was accounted for, whether your neurological findings were rated separately under Note (1) or folded into the spine rating, which conditions were decided, which were deferred, and which were never addressed at all. It also assigns your effective date, which controls back pay. A rating that looks low is very often not a disagreement about how bad your neck is, it is a rater who used the pre-repetition numbers, or missed the radiculopathy, or rated one side and not both. You cannot see any of that from the percentage. Do not go by the percentage alone, and do not decode it by yourself if you are not sure what you are looking at, have someone who reads these for a living read it with you before the clock runs out. You have one year from the date on that letter to file a Higher-Level Review (VA Form 20-0996), a Supplemental Claim (VA Form 20-0995) or a Board appeal, and the deadline runs from the date printed on the letter, not the date you opened it. Bring it to this office and we will go through it line by line, at no cost, and tell you plainly whether it is right.
What normal looks like: 30 to 60 days for a simple claim, longer for a complex one
After your exam you should expect some kind of notification from the VA, a decision, a request for more information, or a notice that another exam has been scheduled. For a straightforward, single-issue claim that often lands within 30 to 60 days. But 30 to 60 days is a rough guide, not a rule, and it is not a ceiling. A claim with several conditions, a toxic-exposure or presumptive question, a returned exam, or missing records routinely takes 90 days or more, and that alone does not mean anything is wrong, the more moving parts your case has, the longer the VA takes to work it. Inside the window that is normal for a case like yours, silence is expected and there is nothing to fix, and a tracker that jumps backward is normal too.
What matters is not a fixed number of days, it is whether the claim is still moving and whether you can get a straight answer about where it is. Once you are well past what is normal for a case like yours and the VA either goes silent or cannot tell you what the claim is waiting on, stop waiting. That is usually where the real trouble hides, an exam that came back twice, a records request that was never answered, a claimed condition that got dropped, or a file sitting in the wrong queue. Call the VA at 800-827-1000, ask specifically what the claim is waiting on and who it is assigned to, and write down the answer. If you cannot get a straight answer, or the answer tells you the exam is the problem, that is the moment to bring it to this office rather than sitting on it for another three months. Problems raised early get fixed inside the claim. Problems discovered in a denial letter get fixed on appeal, and that costs you a year.
Other things that control the clock
Six things decide how long you wait, and none of them are visible from the tracker alone.

The average is a moving number
Check it at the source, not second-hand
The VA publishes an average days-to-complete figure for disability claims that moves month to month; check the current number on the VA’s own claim status page rather than relying on any second-hand figure. In practice, most veterans see a decision somewhere between roughly three and eight months from the date the claim was filed, with the exam usually falling in the middle of that window.
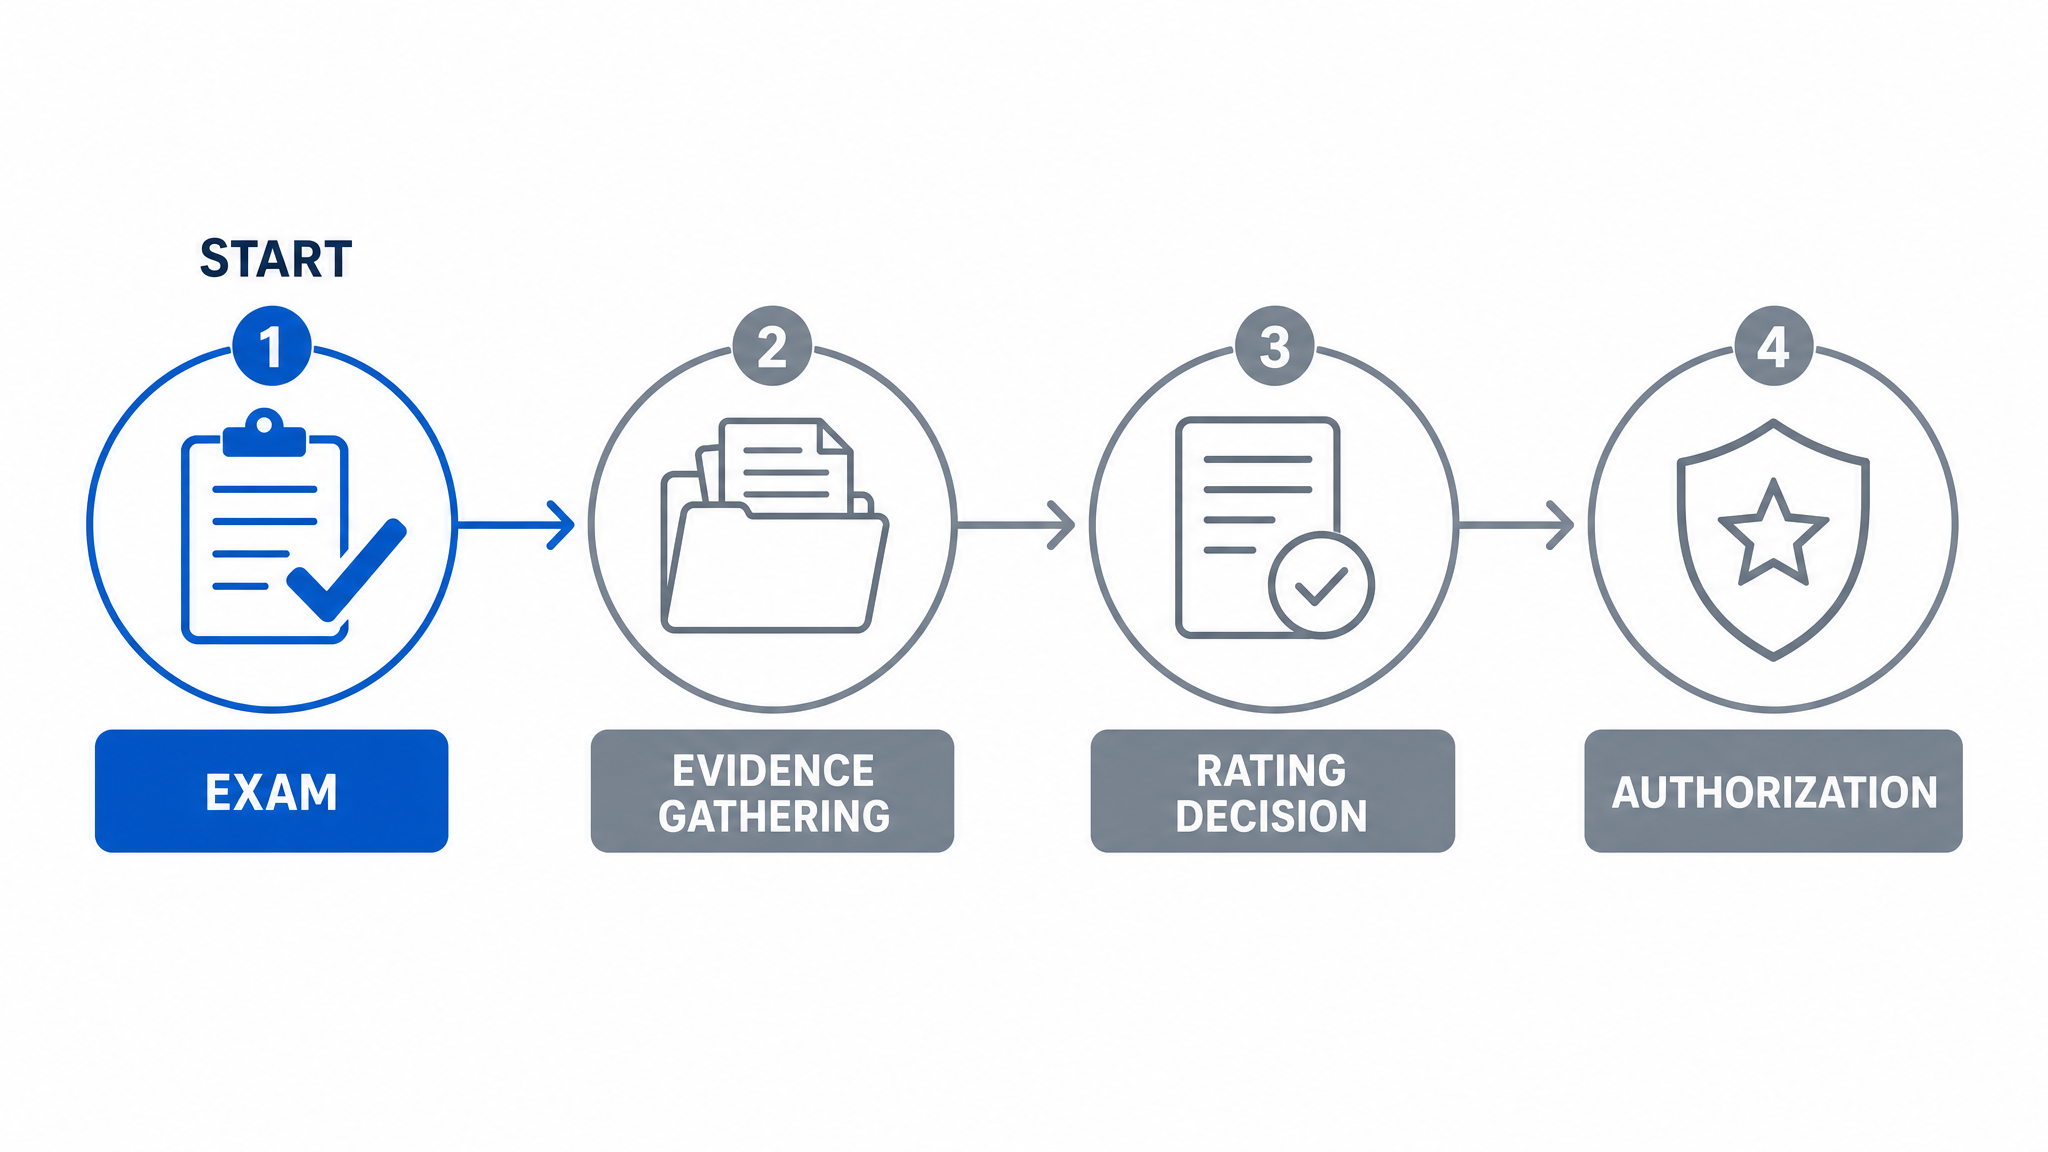
The exam is not the last step
Three stages still sit in front of you
The exam is not the last step. The clock does not start at the exam and it does not stop there either, the claim still has to clear evidence gathering, the rating decision and authorization.
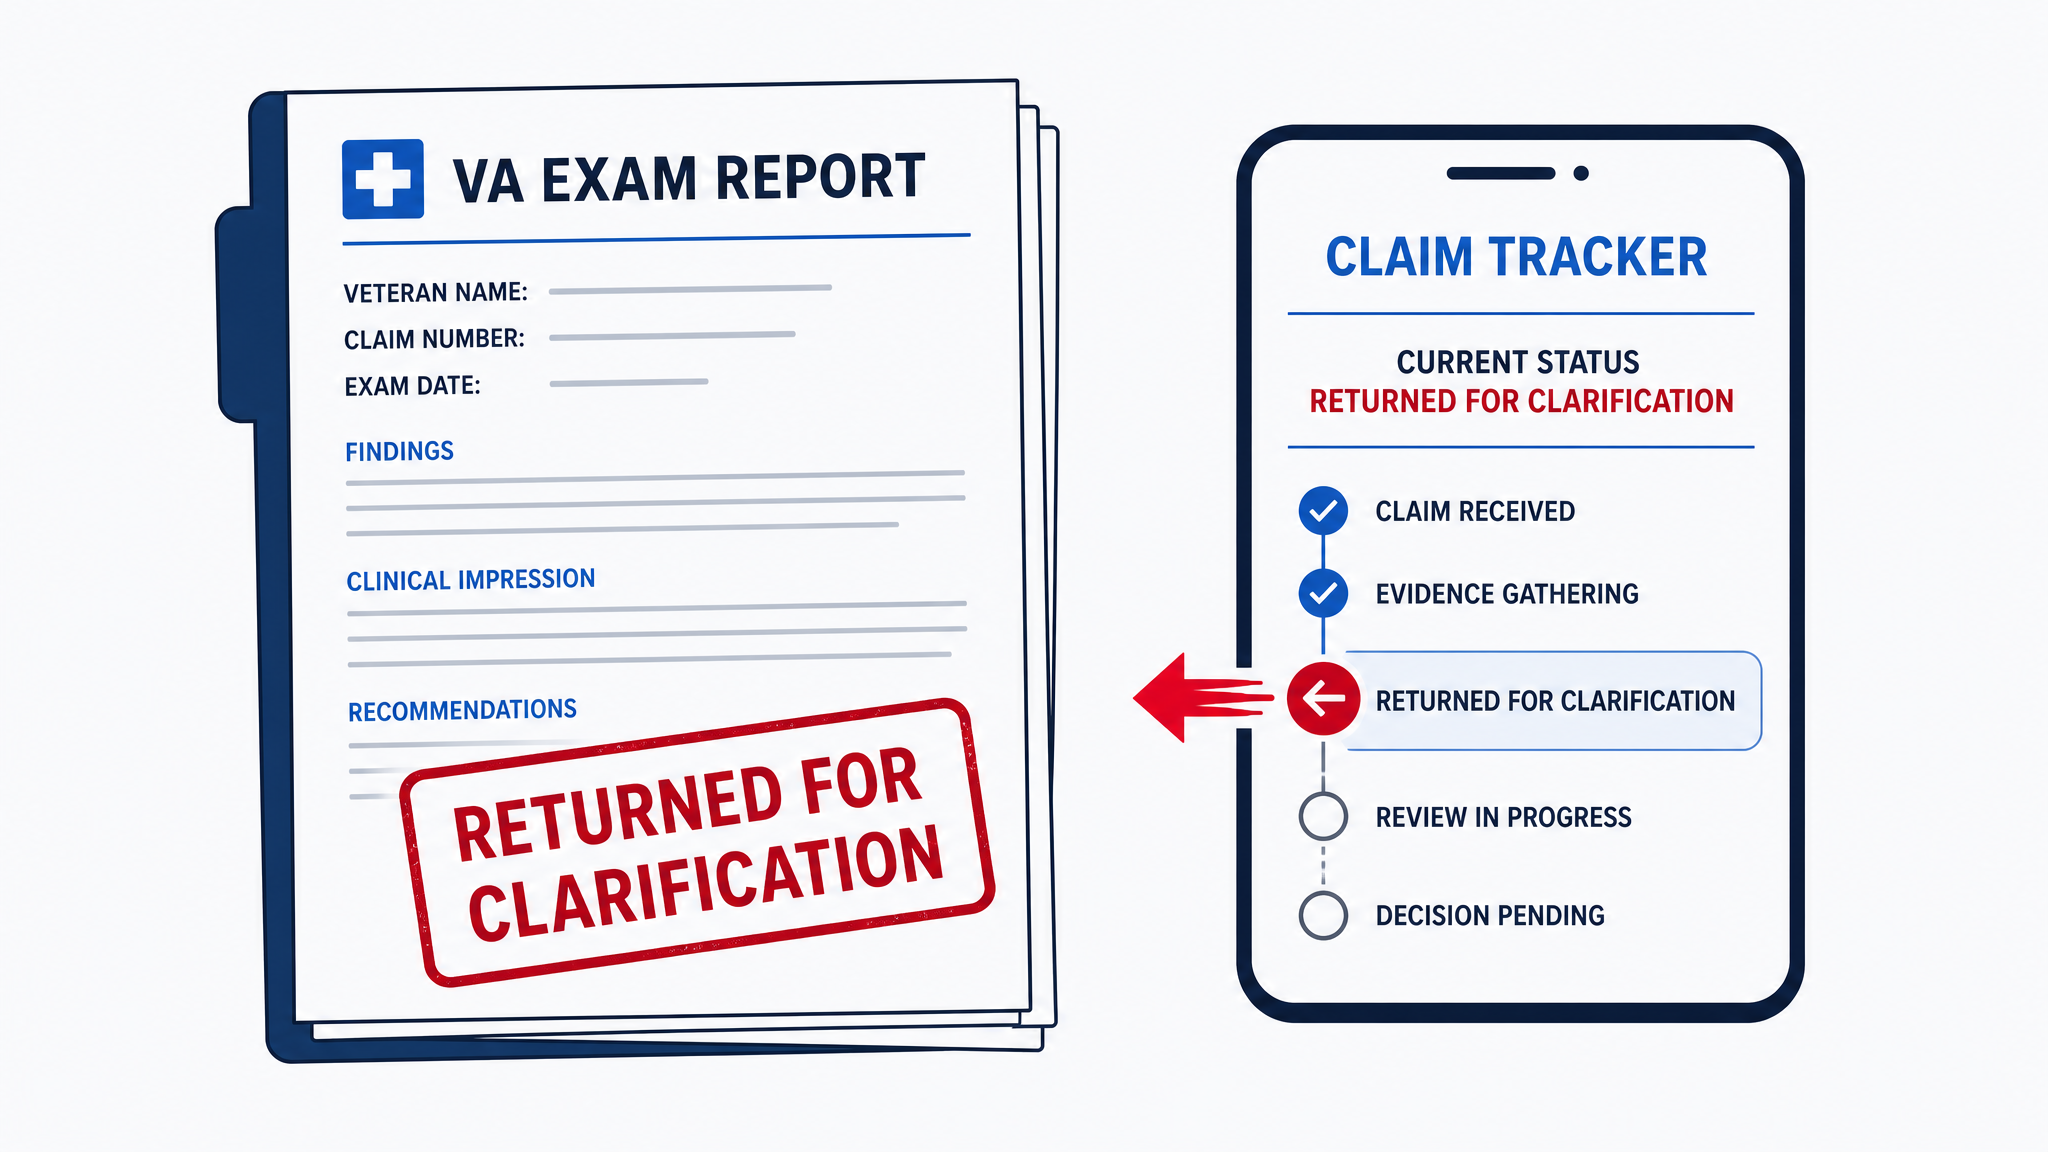
A returned exam is the invisible delay
The reason a tracker slides backward
A returned or clarified exam is the most common invisible delay, and it is why a tracker can slide backward. Expect some contact from the VA within 30 to 60 days of the exam. Past 60 days with nothing at all, call and ask specifically what the claim is waiting on.
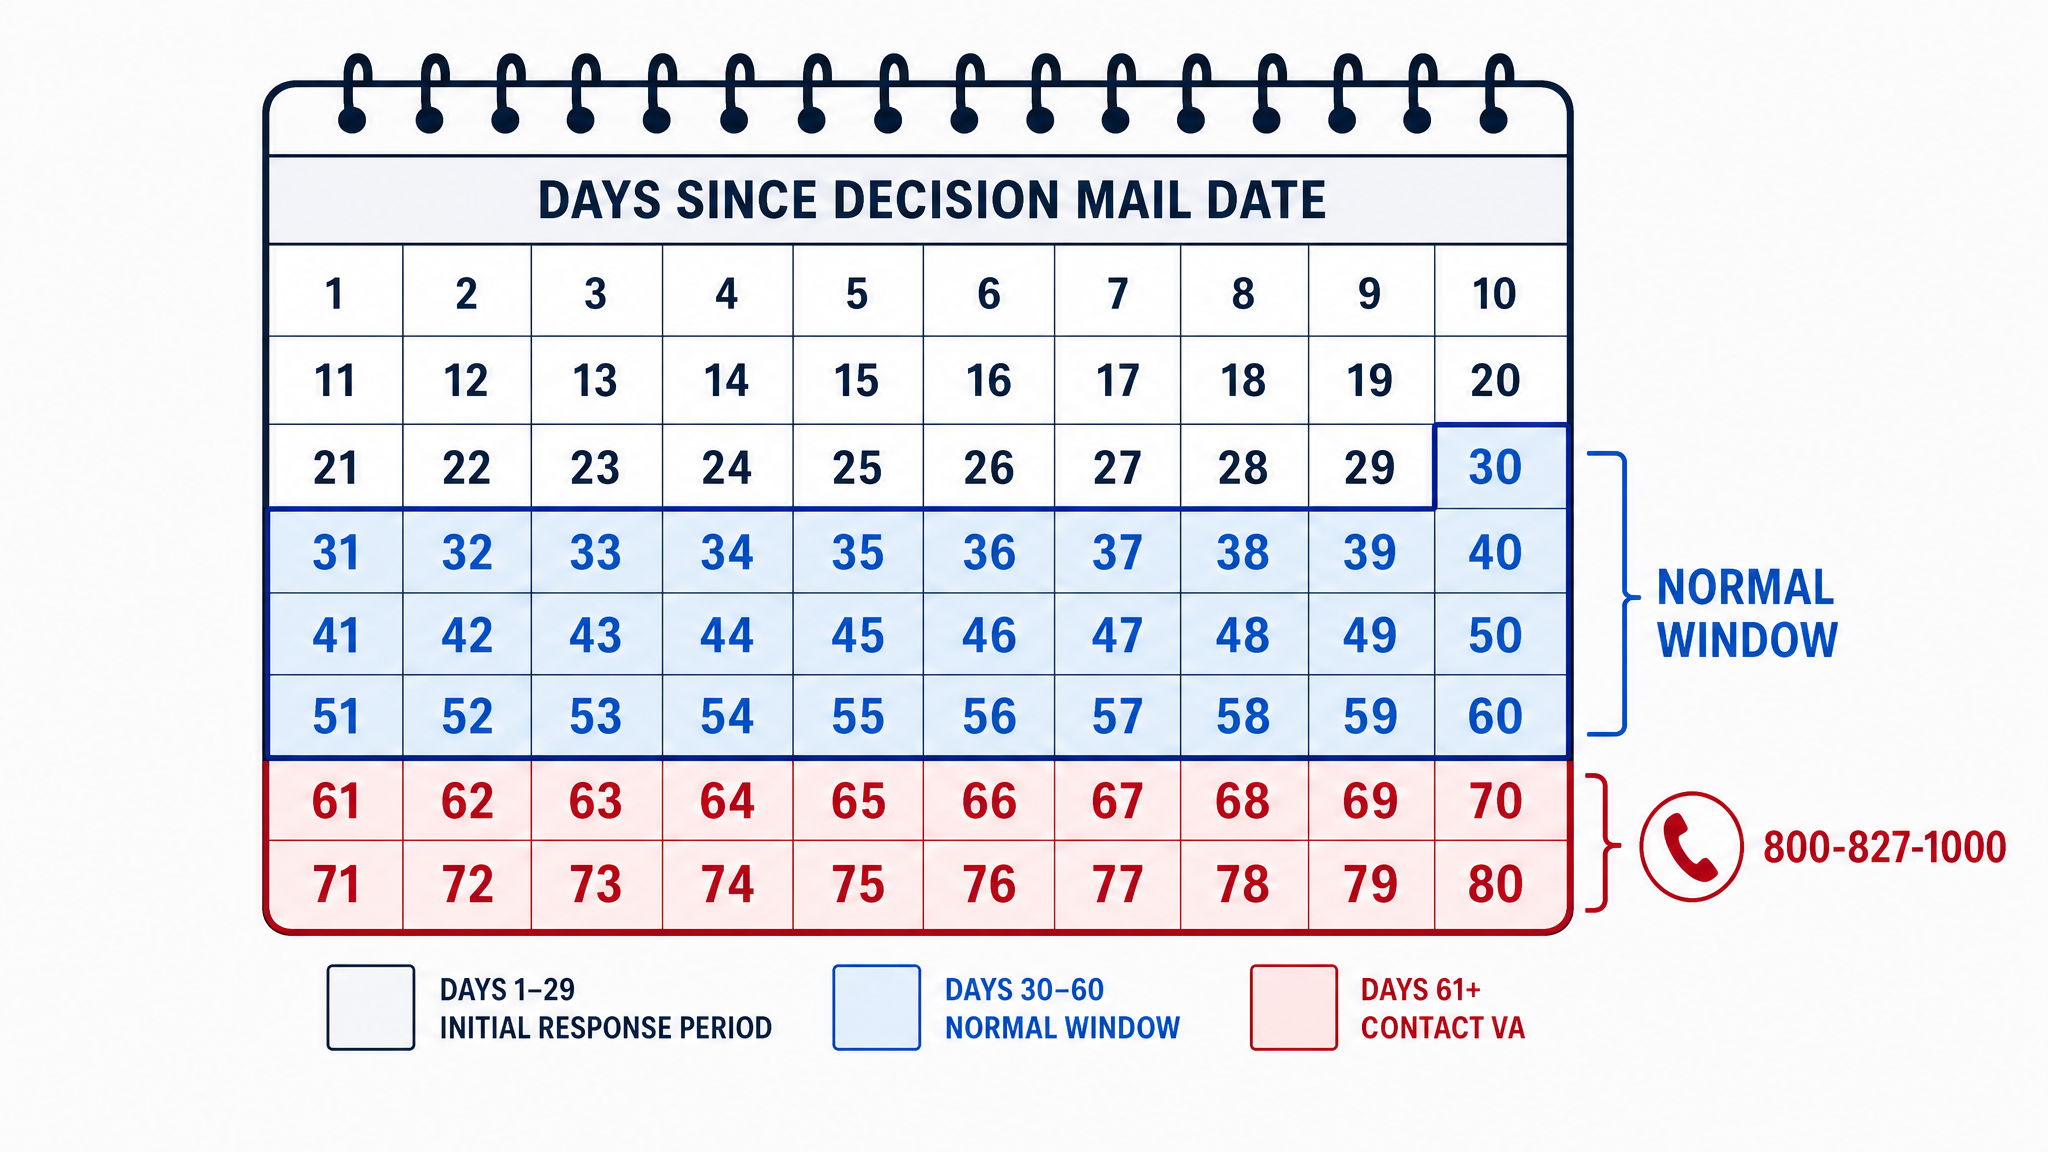
30 to 60 days is a guide, not a deadline
A complex case can take 90 days or more
Thirty to sixty days is a rough average for a simple, single-issue claim, not a hard rule and not a ceiling. A claim with several conditions, a presumptive or toxic-exposure question, a returned exam, or missing records can easily take 90 days or more, and that alone does not mean anything is wrong. Watch whether the claim is still moving, not the calendar. Only when it stalls well past what is normal for a case like yours, and no one can tell you what it is waiting on, should you stop waiting, call 800-827-1000 and ask what the claim is waiting on and who it is assigned to.
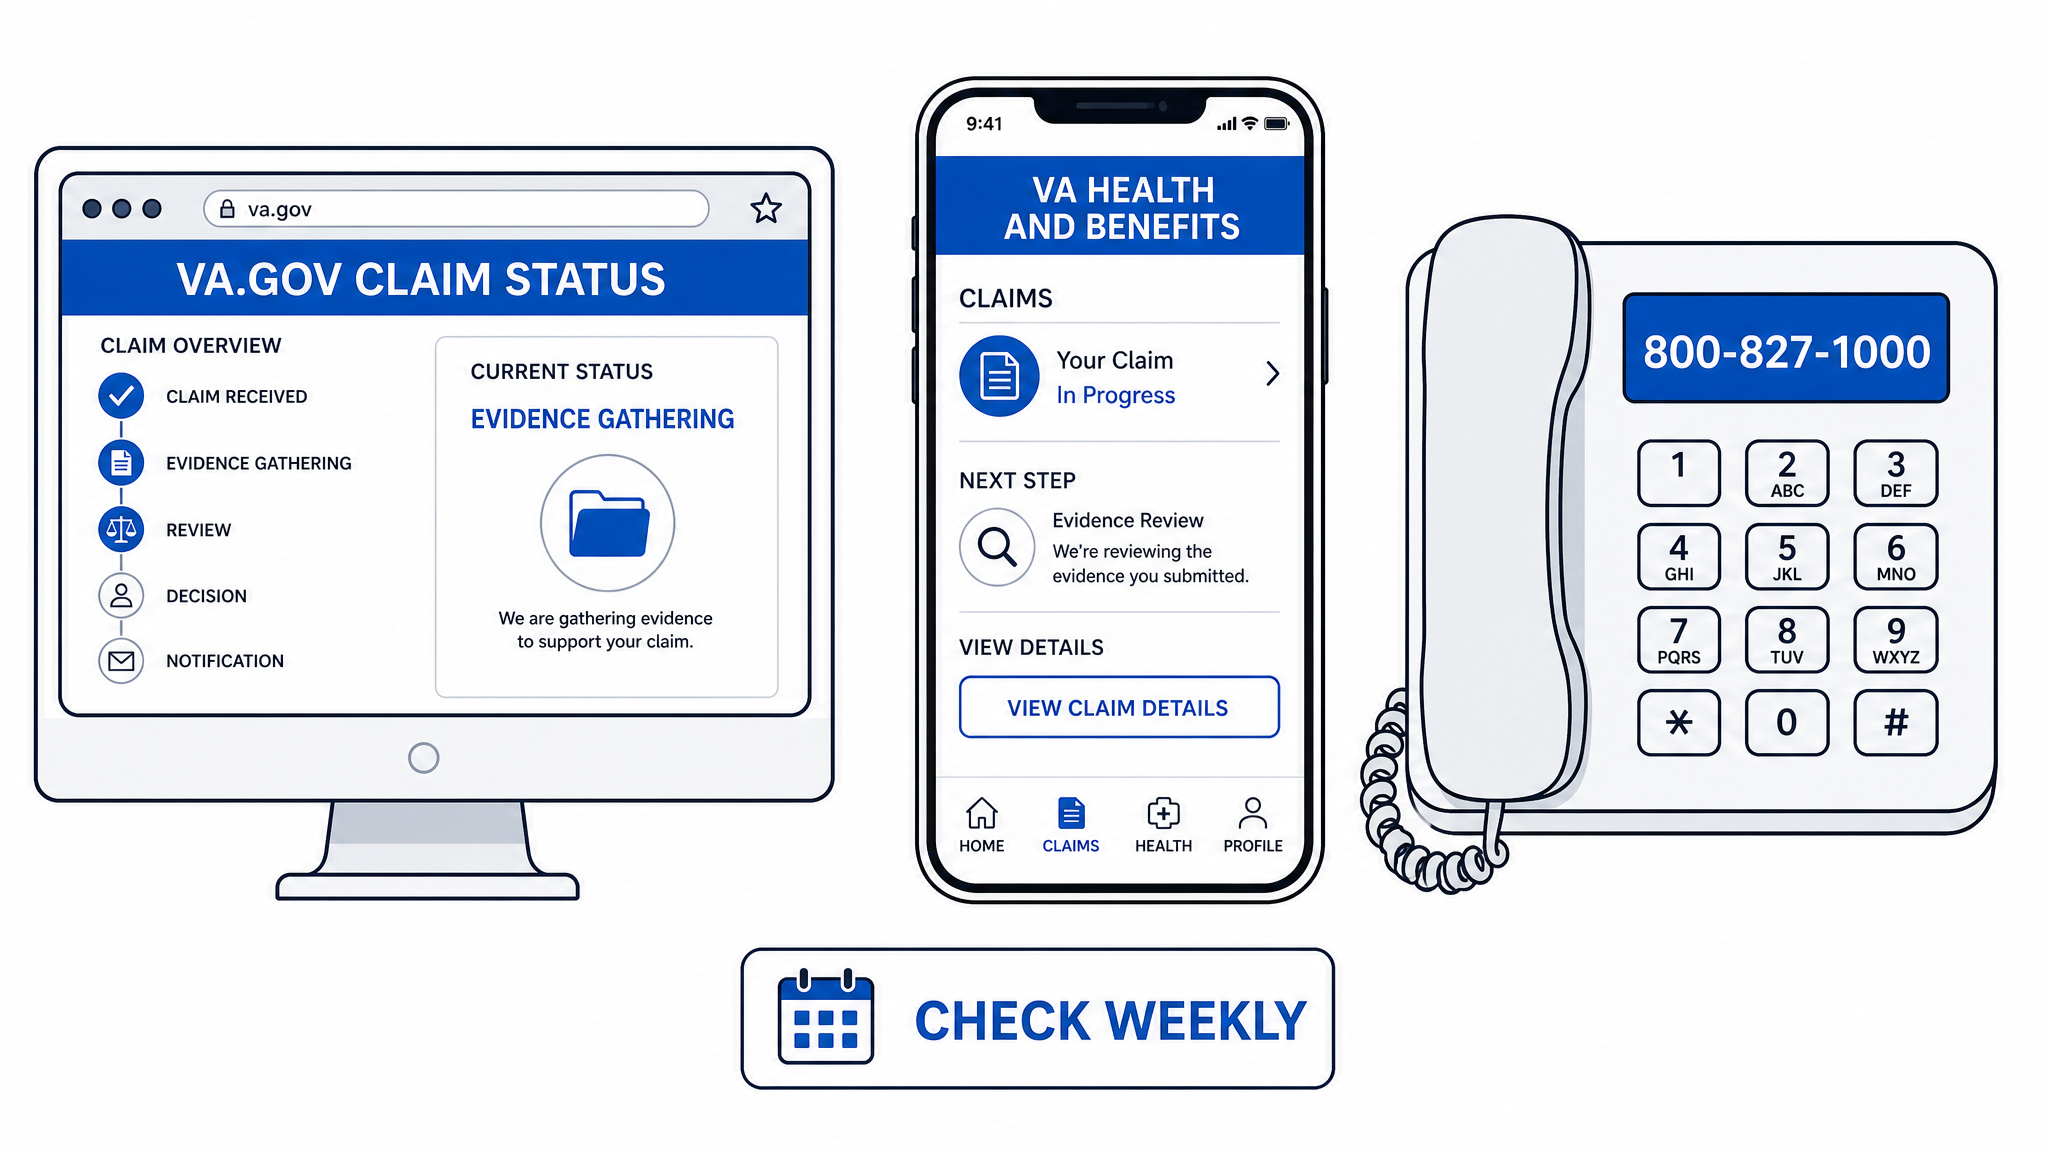
Watch your status yourself, in one of three places
Weekly, not daily
Check your own status in one of three places: your VA.gov claim status page, the VA Health and Benefits mobile app, or by calling 800-827-1000. Check it weekly, not daily. And understand exactly what a status check can tell you: if a decision is posted in your account, it is live; if it is not posted, it is not ready. That is the whole rule. This is not something your representative or your attorney can speed up, we see the same thing you see, at the same time, and calling us to ask does not move it. Calling the VA to ask for an update does not move it either. Watch it yourself, weekly, and the moment a decision posts, bring it to us.
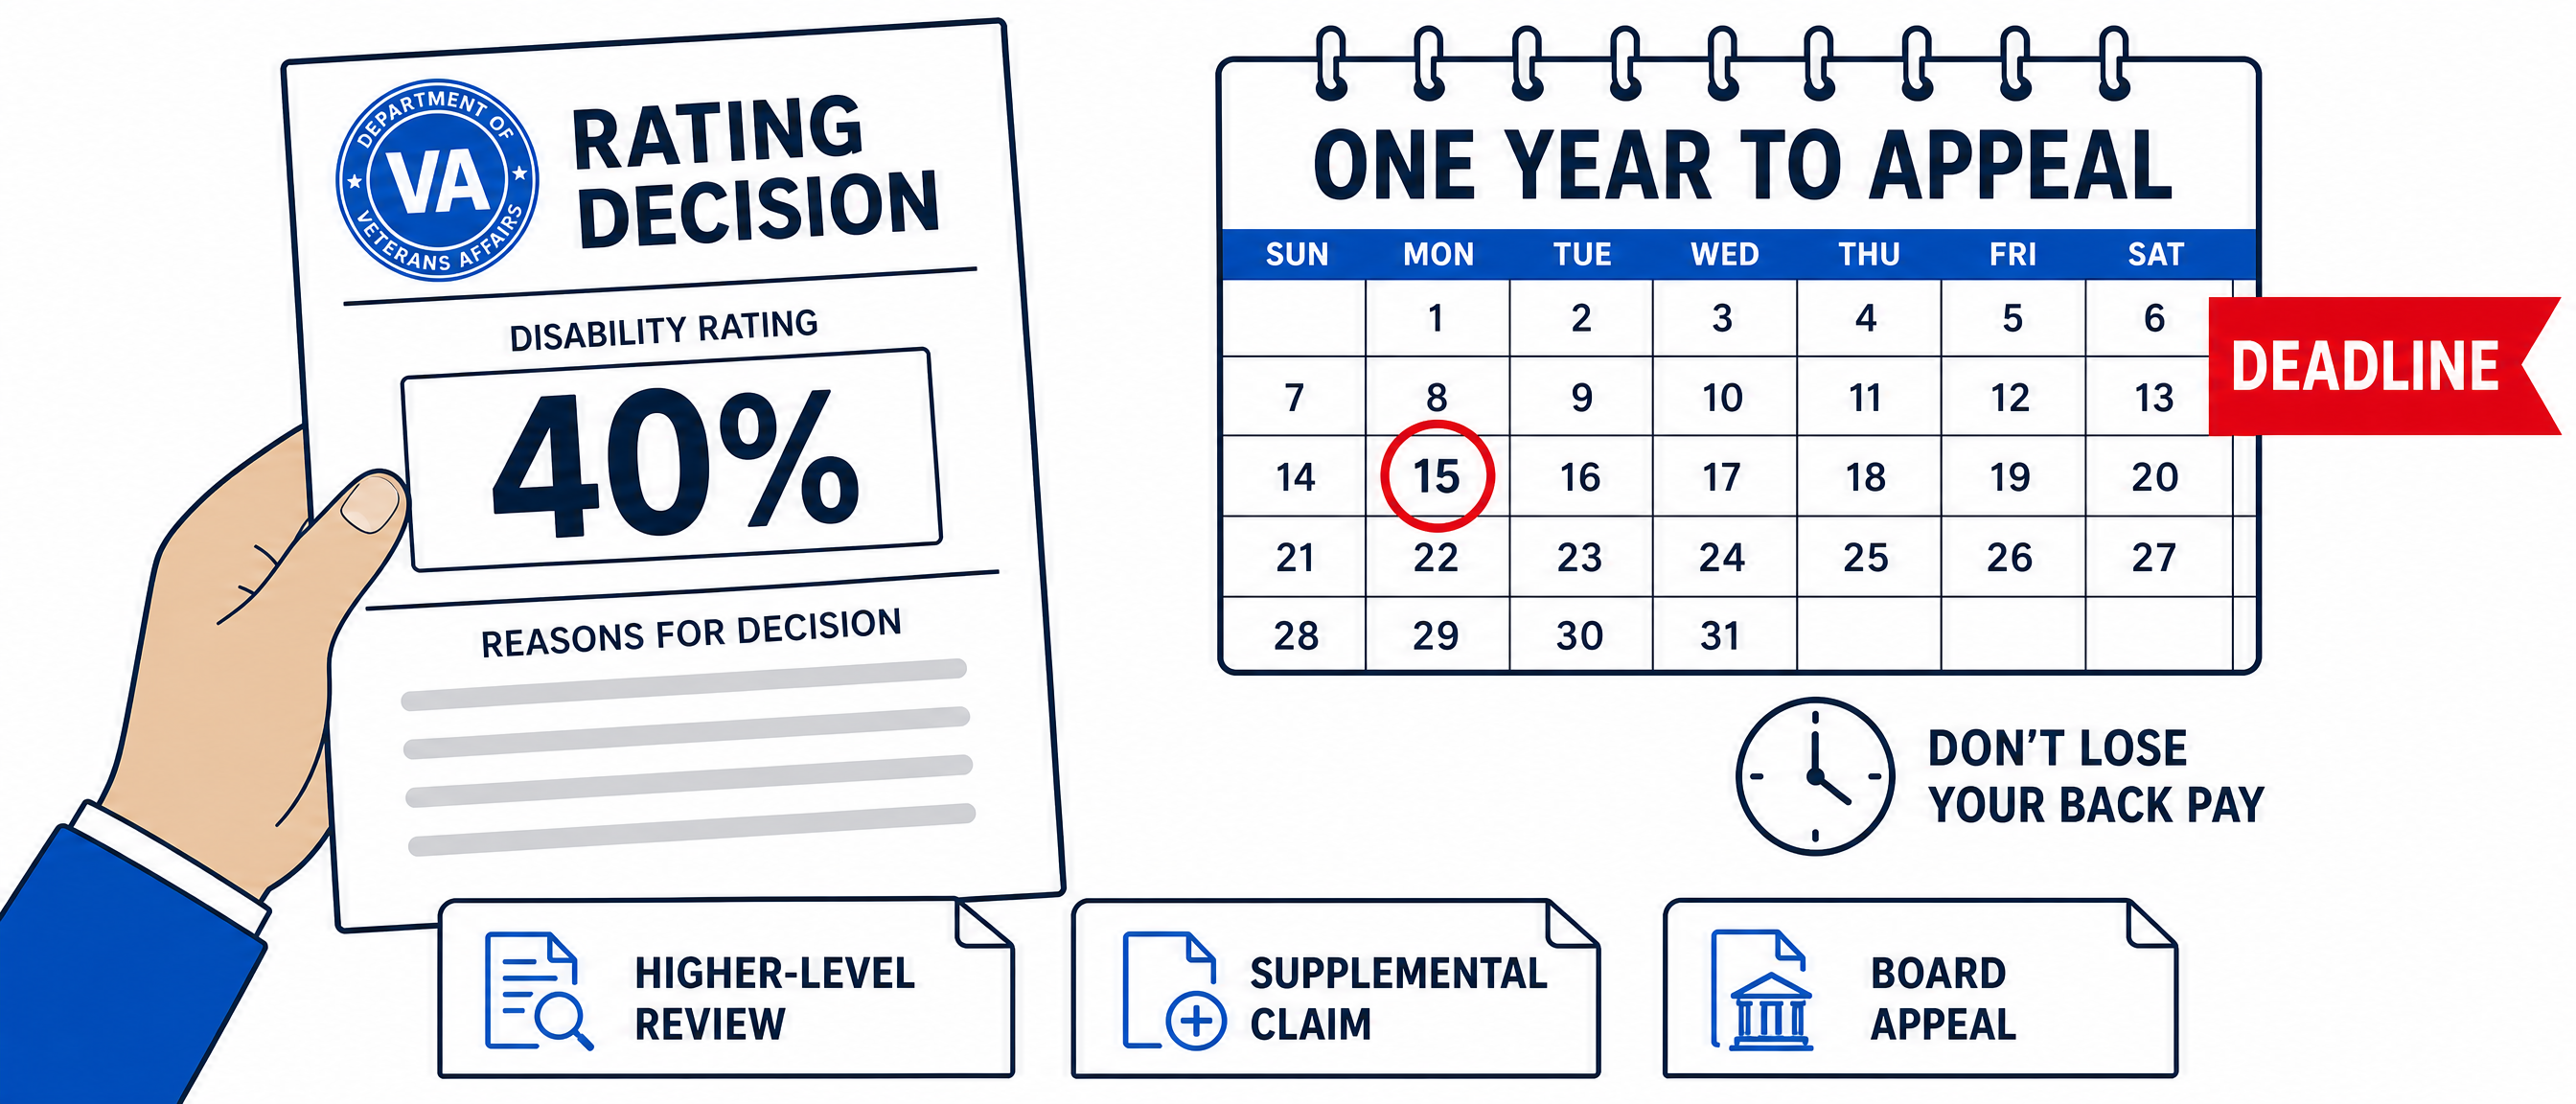
Your decision letter arrives, read it, then start the appeal clock
What to do the day it lands in your mailbox
The decision letter is the finish line of the claim and the starting line of the appeal, and the moment it arrives, a one-year clock starts running. Read it the same day. Find the combined rating, the percentage assigned to each condition, and the effective date, because the effective date controls how far back your back pay reaches. Then request a copy of your C&P exam report so you can see whether the rater used your real range-of-motion numbers or ignored the radiculopathy. If any part of the decision is wrong, a low rating, a denied condition, or a bad effective date, you have three appeal lanes, and you must choose one within one year of the date printed on the letter: a **Higher-Level Review (VA Form 20-0996)**, where a senior reviewer re-decides on the same evidence; a **Supplemental Claim (VA Form 20-0995)**, when you have new and relevant evidence such as a private DBQ or your own range-of-motion exam; or a **Board Appeal (VA Form 10182)** to a Veterans Law Judge. Miss that one-year deadline and the decision becomes final. You can still file again later, but you lose the original effective date, and that lost time is lost back pay you never get back. Bring the letter to this office before the year runs out and we will read it with you, line by line, at no cost.
07Remedy
How to report a bad exam
Where this exam goes wrong
The most common trap in the SMC exam is the examiner failing to use the regulation's specific language. A finding that the veteran has "severe" limitation is not the same as a finding that remaining function is "no more useful than an amputation stump with a suitable prosthetic appliance." If the examiner does not state the prosthetic-comparison finding in those terms, the VA rater may not infer the SMC entitlement. Ask the examiner directly: "Would I be equally well served by an amputation and prosthesis?" Force the finding.

Write it down the moment you get to your car
Date, start time, end time, the examiner’s name and credentials, the vendor, every test that was performed, and every test that was not. A contemporaneous note written the same day is evidence. A memory reconstructed four months later is not.

Get the exam report and the questionnaire
Request a copy through VA.gov, through a written request to the Regional Office, or by calling 800-827-1000. You cannot challenge what you have not read. Compare it line by line against what actually happened in the room.

Name the defect specifically, with the citation
Never write "the exam was unfair." Write "no goniometer was used, contrary to 38 CFR §4.46" or "flare-ups were reported and not addressed, contrary to Sharp v. Shulkin" or "repetitive use testing was not performed, contrary to 38 CFR §4.40 and DeLuca." A specific, citable defect is what forces action.

Submit a statement asking for a new examination
VA Form 21-4138, Statement in Support of Claim, filed through VA.gov or mailed to the Evidence Intake Center. State the defect, cite the authority, and request a new or supplemental examination. Do this BEFORE the decision if the claim is still open, it is far easier than undoing a decision afterward.
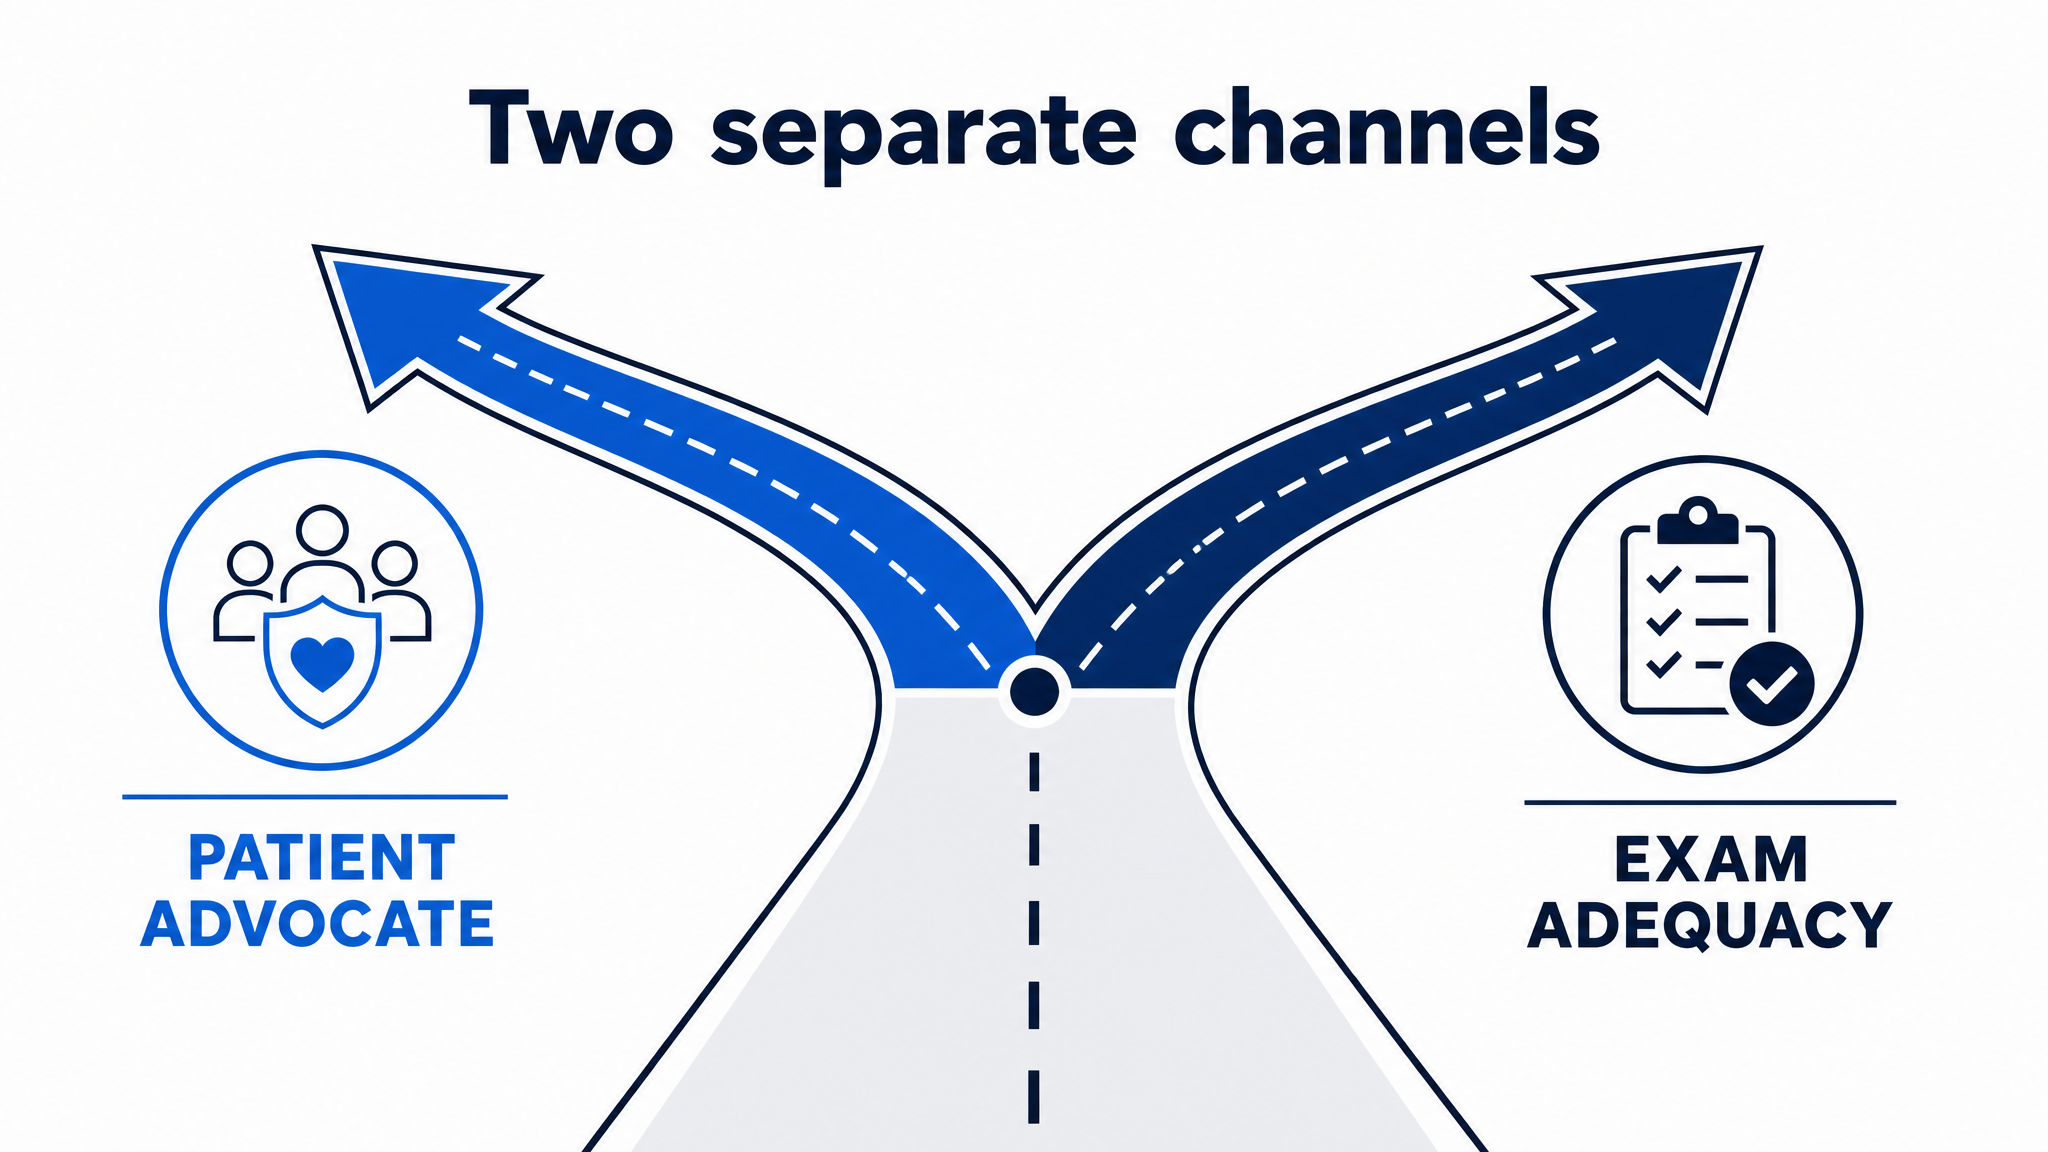
Report examiner conduct separately
If the problem is behavior rather than methodology, you were rushed out, dismissed, never touched, or treated with hostility, file a complaint with the VA facility’s Patient Advocate, or with the vendor directly for a contract exam, and copy the Regional Office. Conduct complaints and adequacy challenges are two different tracks and you can run both.
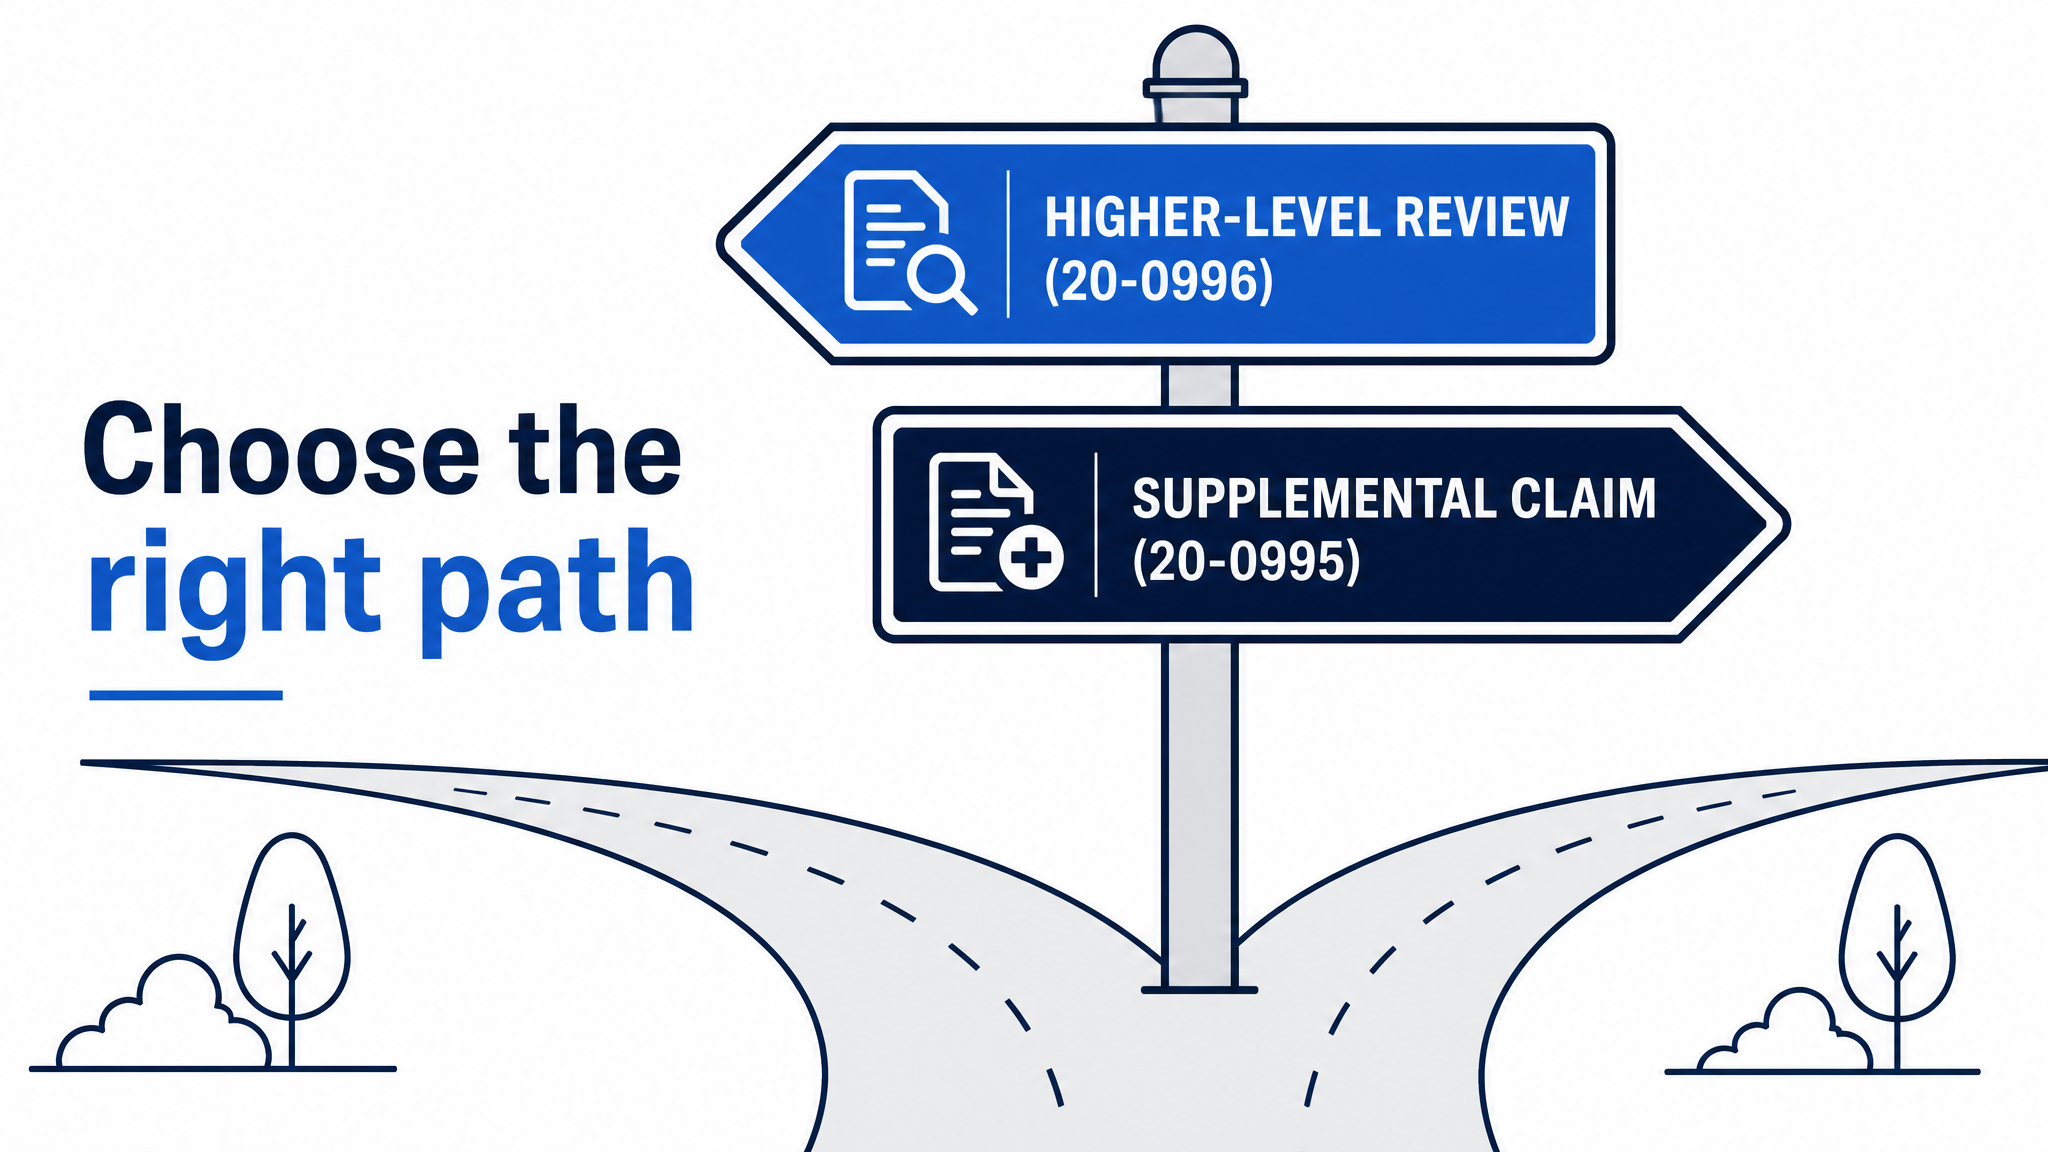
If a decision has already issued, pick the right lane
A Higher-Level Review (VA Form 20-0996) argues the VA erred on the evidence it had, the right vehicle when the exam was inadequate on its face. A Supplemental Claim (VA Form 20-0995) is the vehicle when you are adding new and relevant evidence, such as your own private range-of-motion examination or a completed DBQ from your treating provider.
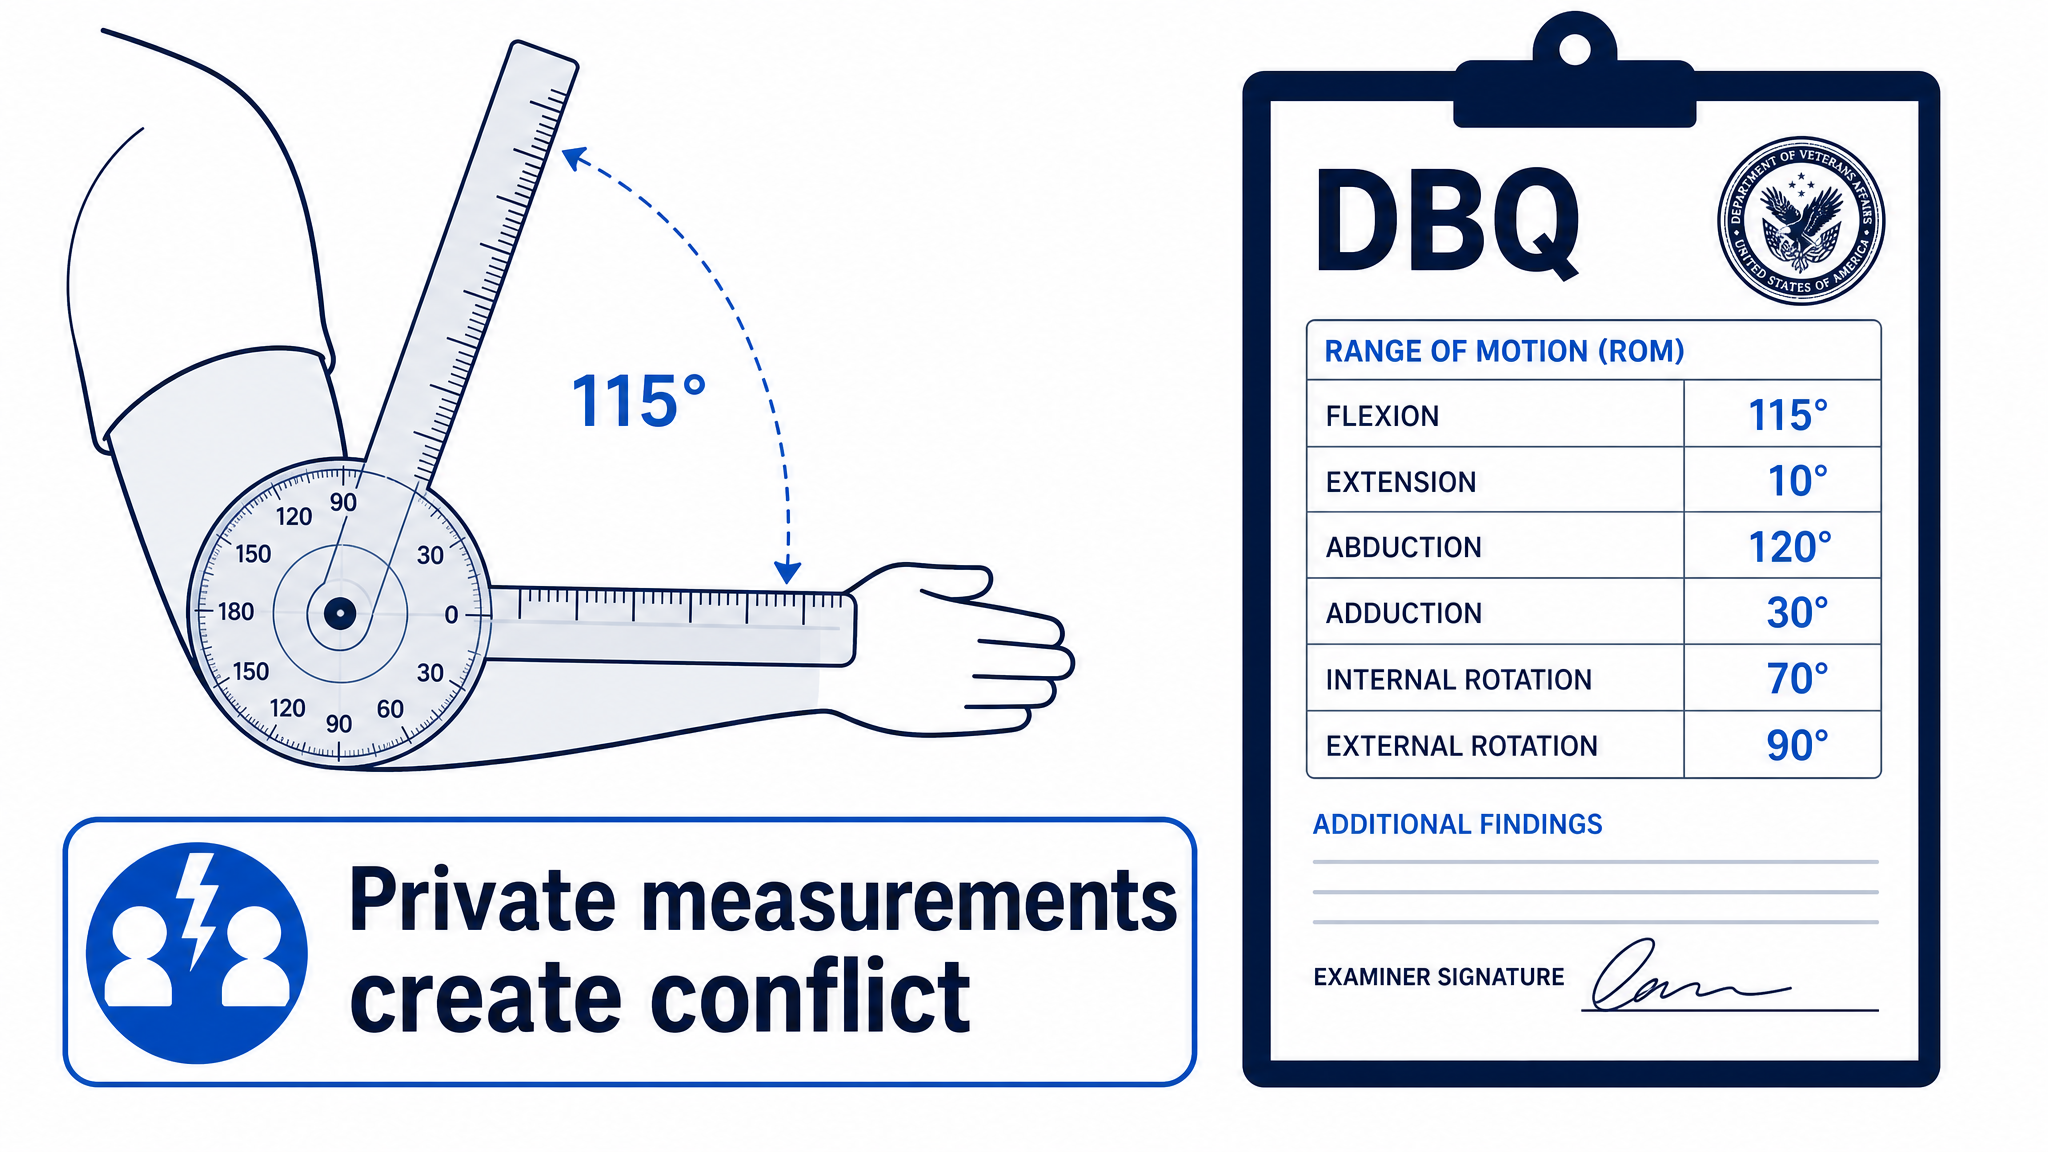
Put your own measurements on the table
A private examination with full goniometric measurements, or a DBQ completed by your own provider, creates a conflict in the evidence that the VA has to resolve, and under 38 CFR §3.102 reasonable doubt is resolved in your favor.
End of clinical section
Special Monthly Compensation (SMC), §1114 / §3.350
The Questions Veterans Actually Ask
Special Monthly Compensation (SMC) Claims, Frequently Asked Questions
Straight answers to the questions that decide special monthly compensation (smc) claims, the ratings, the separate evaluations, and the exam mistakes that cost veterans money. Read every answer with your own file open. If an answer depends on a record you do not have yet, that is the next thing to request, from your doctor, your unit or the VA itself.
Special Monthly Compensation (SMC) is not a percentage on the rating schedule, it is a separate, higher level of compensation paid under 38 U.S.C. §1114 and 38 CFR §3.350 for specific severe losses that exceed what the percentage schedule can capture. It can be paid on top of a 100% rating or even on top of TDIU. SMC comes in lettered levels (K through R) for losses such as anatomical loss or loss of use of a hand, foot, or creative organ, blindness, deafness, being housebound, or needing the regular aid and attendance of another person. The amounts are fixed by statute and are significantly higher than the 100% schedular rate at the upper levels.
Every condition in Special Monthly Compensation (SMC)



